




Global Trends and Projections in the Disease Burden of Bipolar Disorder among Adolescents and Young Adults
-
摘要:
目的 基于全球疾病负担研究(Global burden of disease study,GBD)2021数据,分析1990—2021年全球15~39岁人群双相障碍疾病负担的长期变化趋势,并对2030年前的短期变化进行预测。 方法 基于1990—2021年GBD数据,系统分析全球204个国家、21个区域及不同社会人口指数(sociodemographic index,SDI)地区15~39岁人群双相障碍的发病数、伤残调整寿命年(disability-adjusted life years,DALYs)、年龄标准化发病率(age-standardized incidence rate,ASIR)和年龄标准化DALY率(age-standardized DALY rate,ASDR),采用估计年百分比变化(estimated annual percentage change,EAPC)评价1990—2021年变化趋势,并运用自回归积分滑动平均(autoregressive integrated moving average,ARIMA)模型预测2022—2030年疾病负担。 结果 1990—2021年全球双相障碍发病数和DALYs分别增加38.12%和41.51%,ASIR和ASDR总体呈上升趋势。2021年女性ASIR和ASDR分别为45.83/10万和143.16/10万,高于男性的42.79/10万和134.40/10万;但男性ASIR增长更明显[EAPC=0.24(95%CI:0.22~0.27)vs. 0.11(95%CI:0.09~0.14)]。15~19岁组ASIR较高(15.55/10万),地区及SDI水平间存在差异。预测结果显示,至2030年全球ASIR和ASDR总体仍维持较高水平,不同性别、年龄组、SDI水平和国家的预测趋势存在差异。 结论 全球15~39岁人群双相障碍疾病负担总体增加,并存在明显的人群和地区差异,应加强重点人群的早期识别与分层干预。 Abstract:Objective To analyze the long-term trends in the disease burden of bipolar disorder among the global population aged 15~39 years from 1990 to 2021 based on the Global Burden of Disease Study 2021 (GBD 2021), and to predict short-term changes up to 2030. Methods Using data from the Global Burden of Disease Study 2021(GBD 2021), we analyzed the number of incident cases, disability-adjusted life years(DALYs), age-standardized incidence rate(ASIR), and age-standardized DALY rate(ASDR)for bipolar disorder among individuals aged 15~39 years across 204 countries and territories, 21 regions, and areas stratified by sociodemographic index(SDI). Estimated annual percentage changes(EAPCs)were used to assess trends from 1990 to 2021, and an autoregressive integrated moving average(ARIMA)model was applied to project disease burden from 2022 to 2030. Results From 1990 to 2021, the global incident and DALYs of bipolar disorder increased by 38.12% and 41.51%, respectively, with overall upward trends in ASIR and ASDR. In 2021, the ASIR and ASDR among females were 45.83 per 100, 000 and 143.16 per 100, 000, respectively, higher than those among males ( 42.79 per 100, 000 and 134.40 per 100, 000) . However, ASIR increased more rapidly in males than in females [EAPC = 0.24 (95%CI: 0.22~0.27) vs. 0.11 (95%CI: 0.09~0.14)]. The ASIR was relatively high in the 15~19-year age group (15.55 per 100, 000), and differences were observed across regions and SDI levels. Projections suggested that global ASIR and ASDR would remain at relatively high levels through 2030, with heterogeneous trends by sex, age group, SDI level, and country. Conclusion The disease burden of bipolar disorder among individuals aged 15~39 years has increased globally, with marked population and regional differences, highlighting the need for early identification and stratified interventions in priority groups. -
Key words:
- Global burden of disease /
- Bipolar disorder /
- Adolescents /
- Young adults /
- Disease burden
-
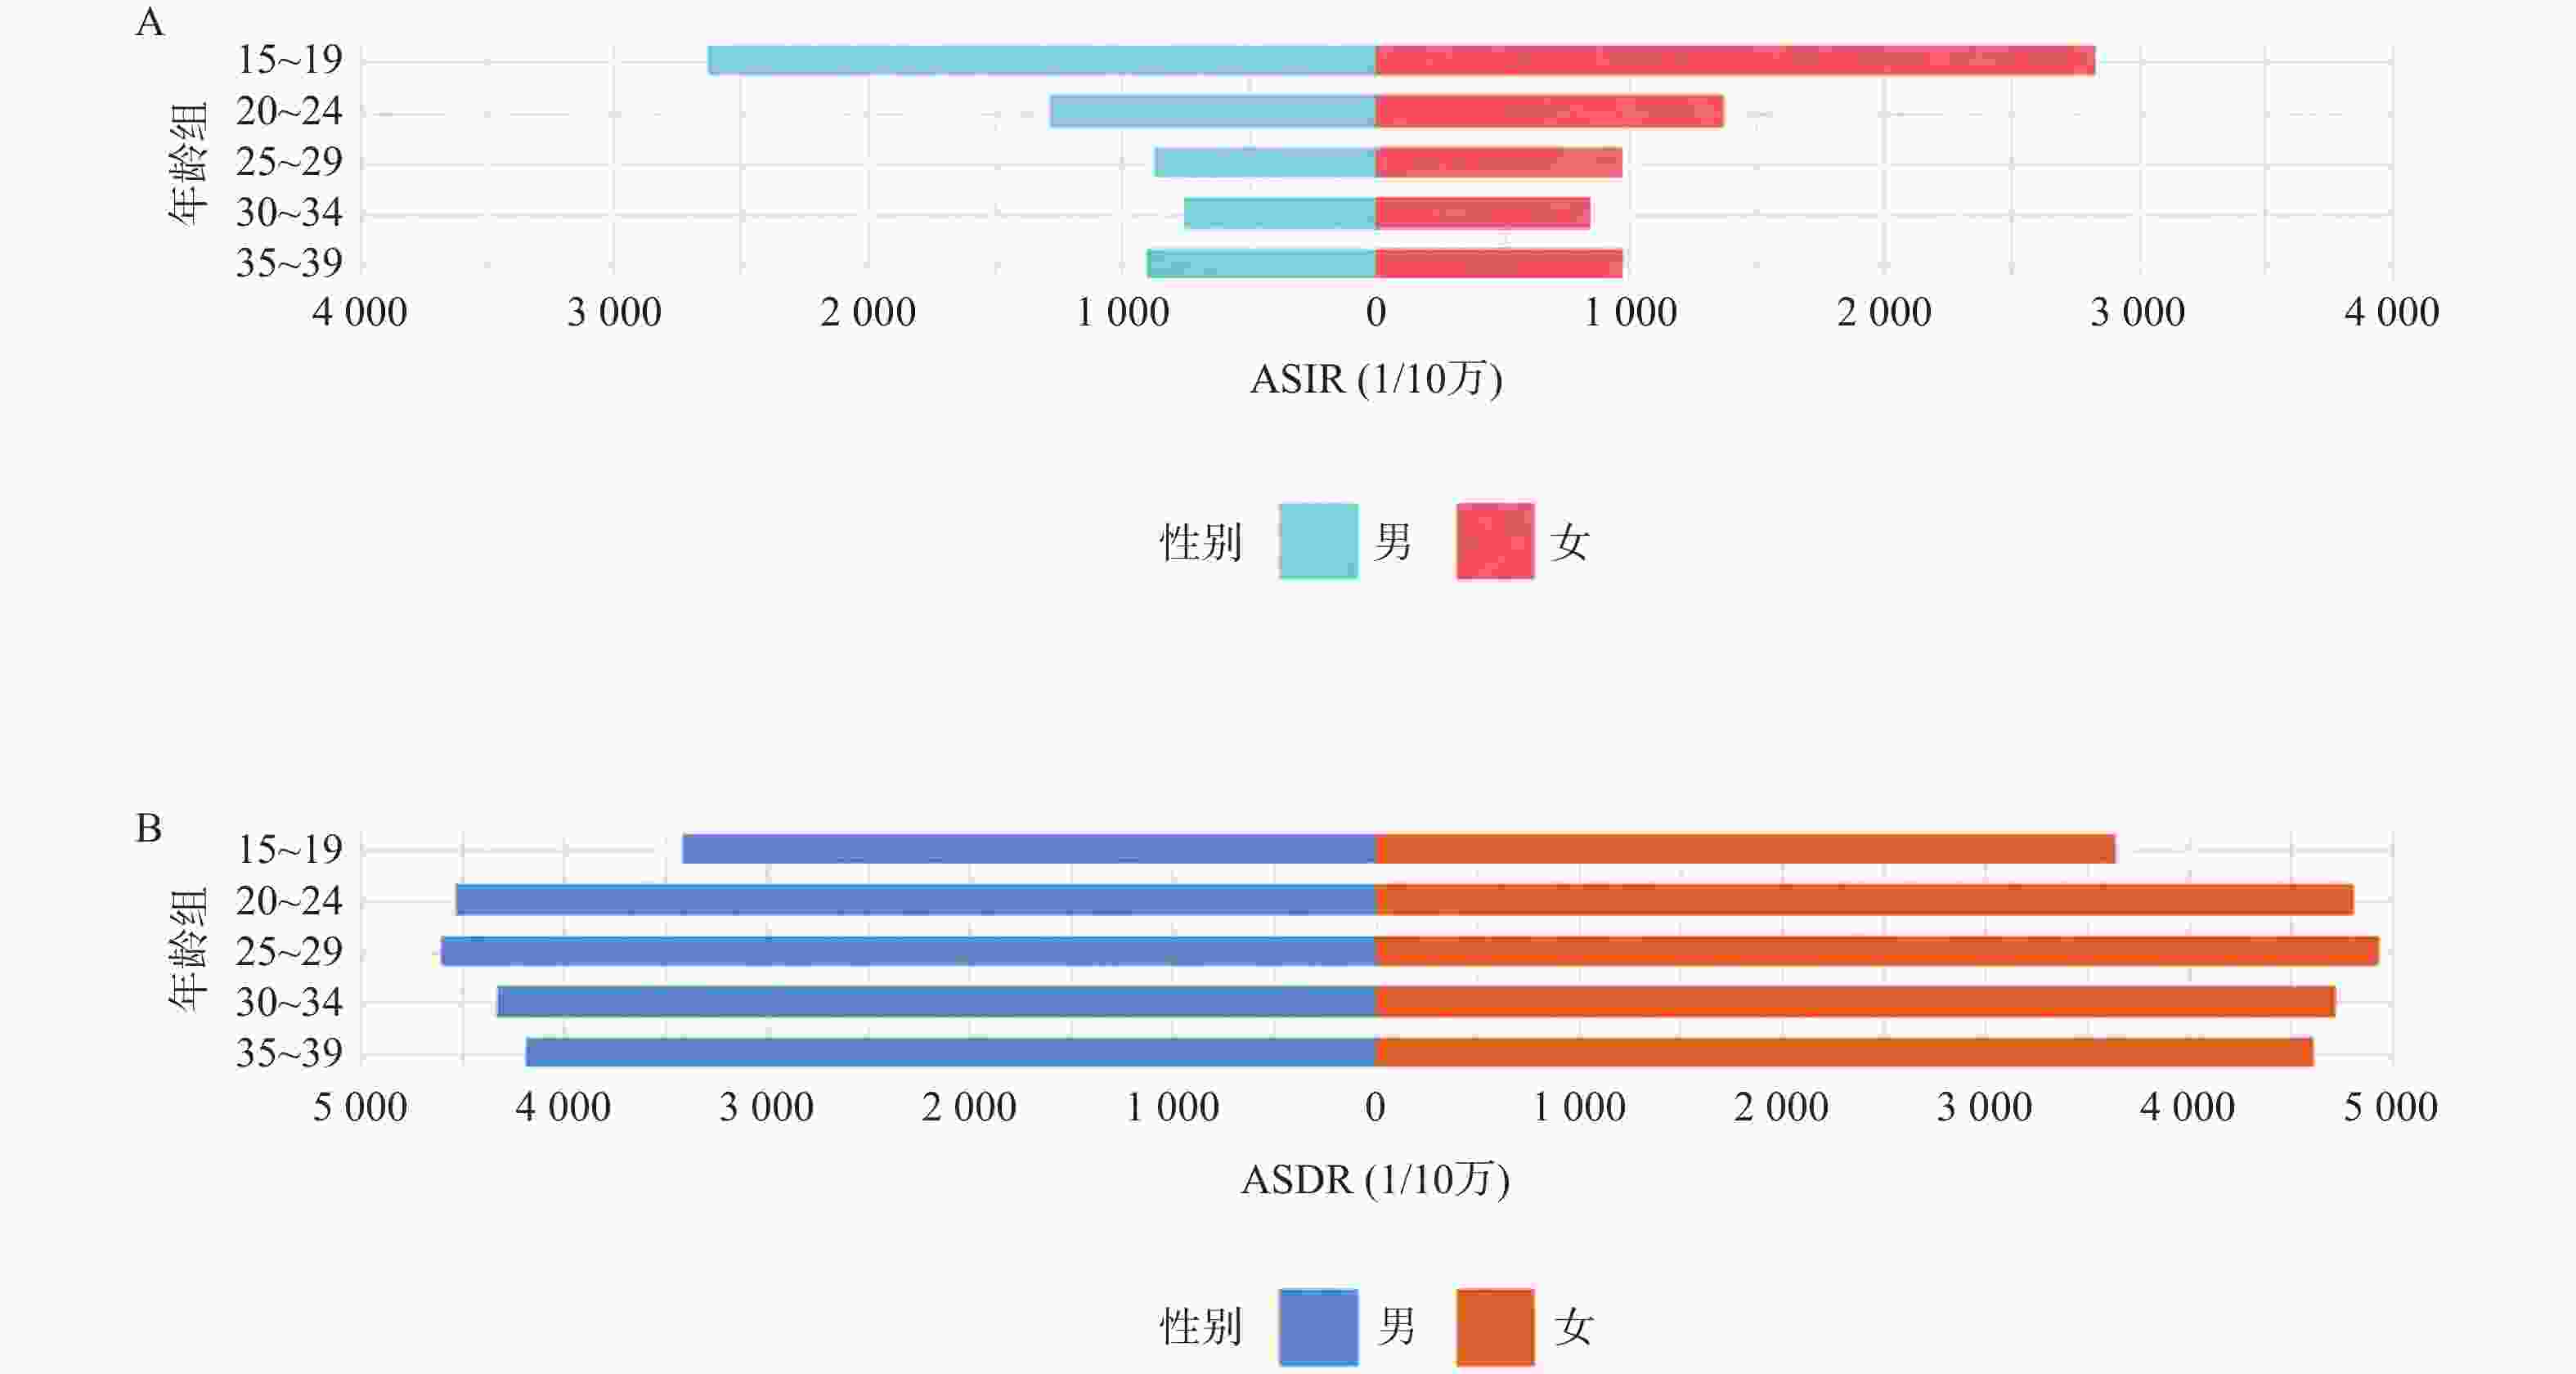
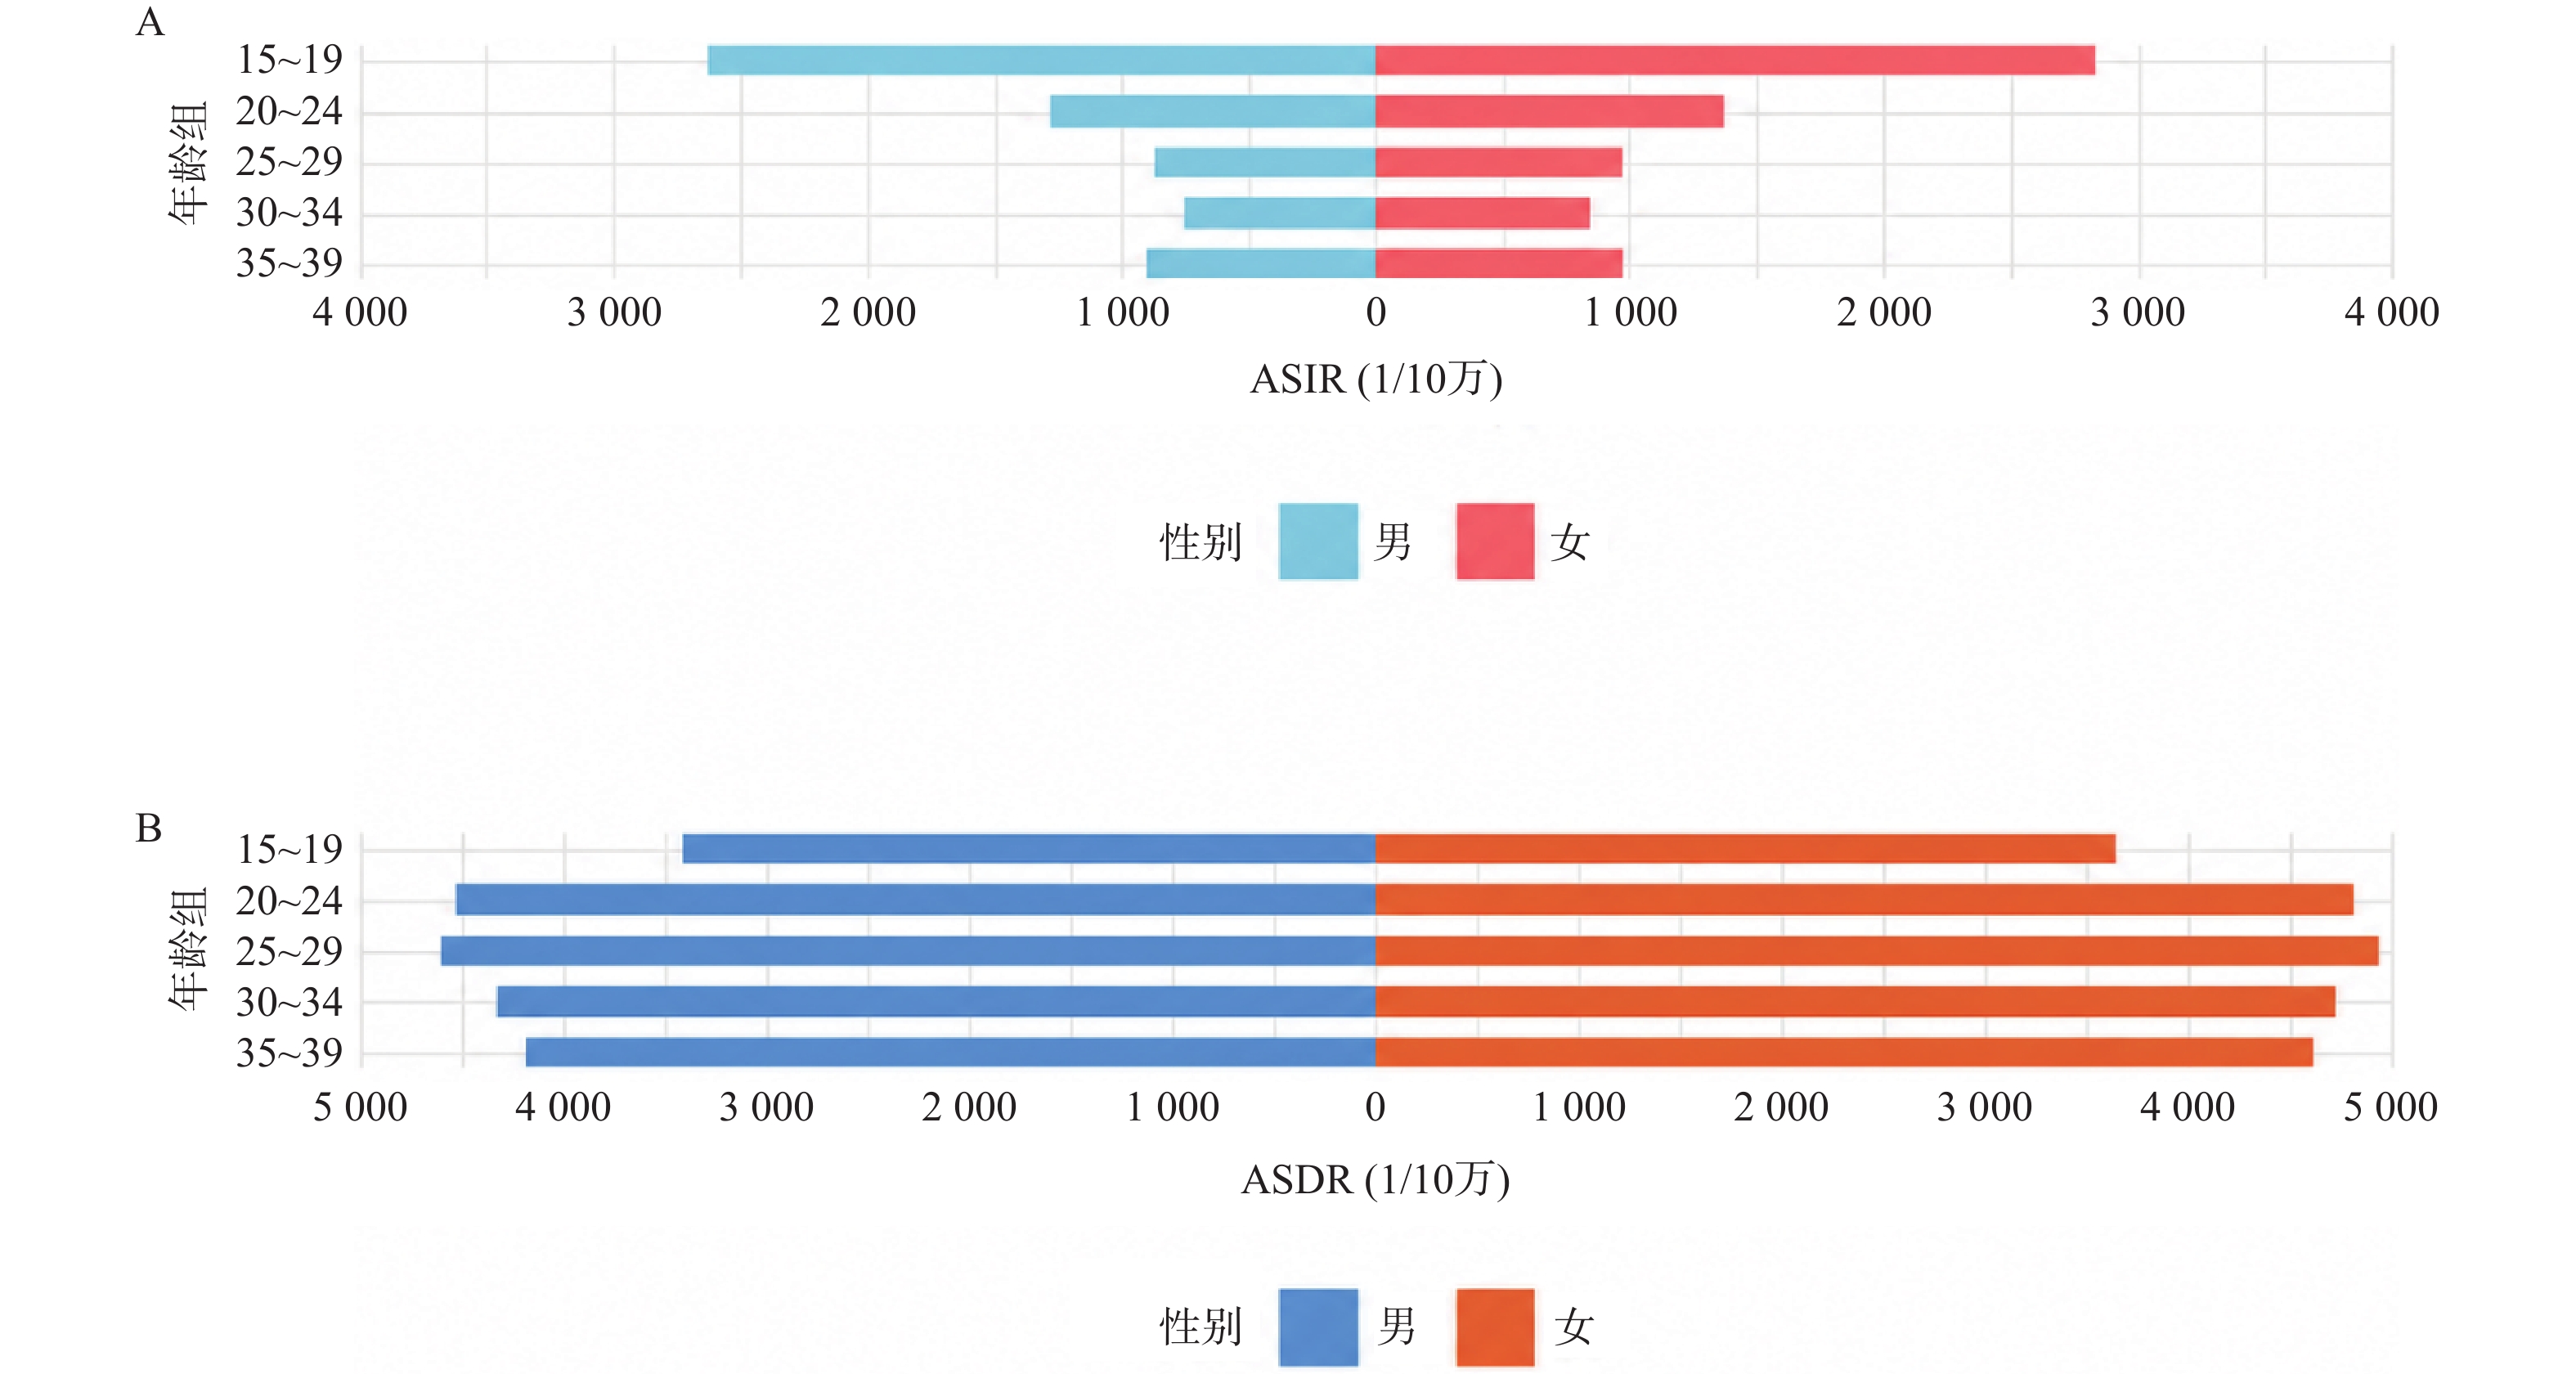
图 1 1990—2021 年不同性别和年龄组 ASIR 与 ASDR 分布情况
A:年龄标准化发病率(ASIR);B:年龄标准化伤残调整寿命年率(ASDR)。
Figure 1. Distribution of ASIR and ASDR by sex and age group,1990–2021
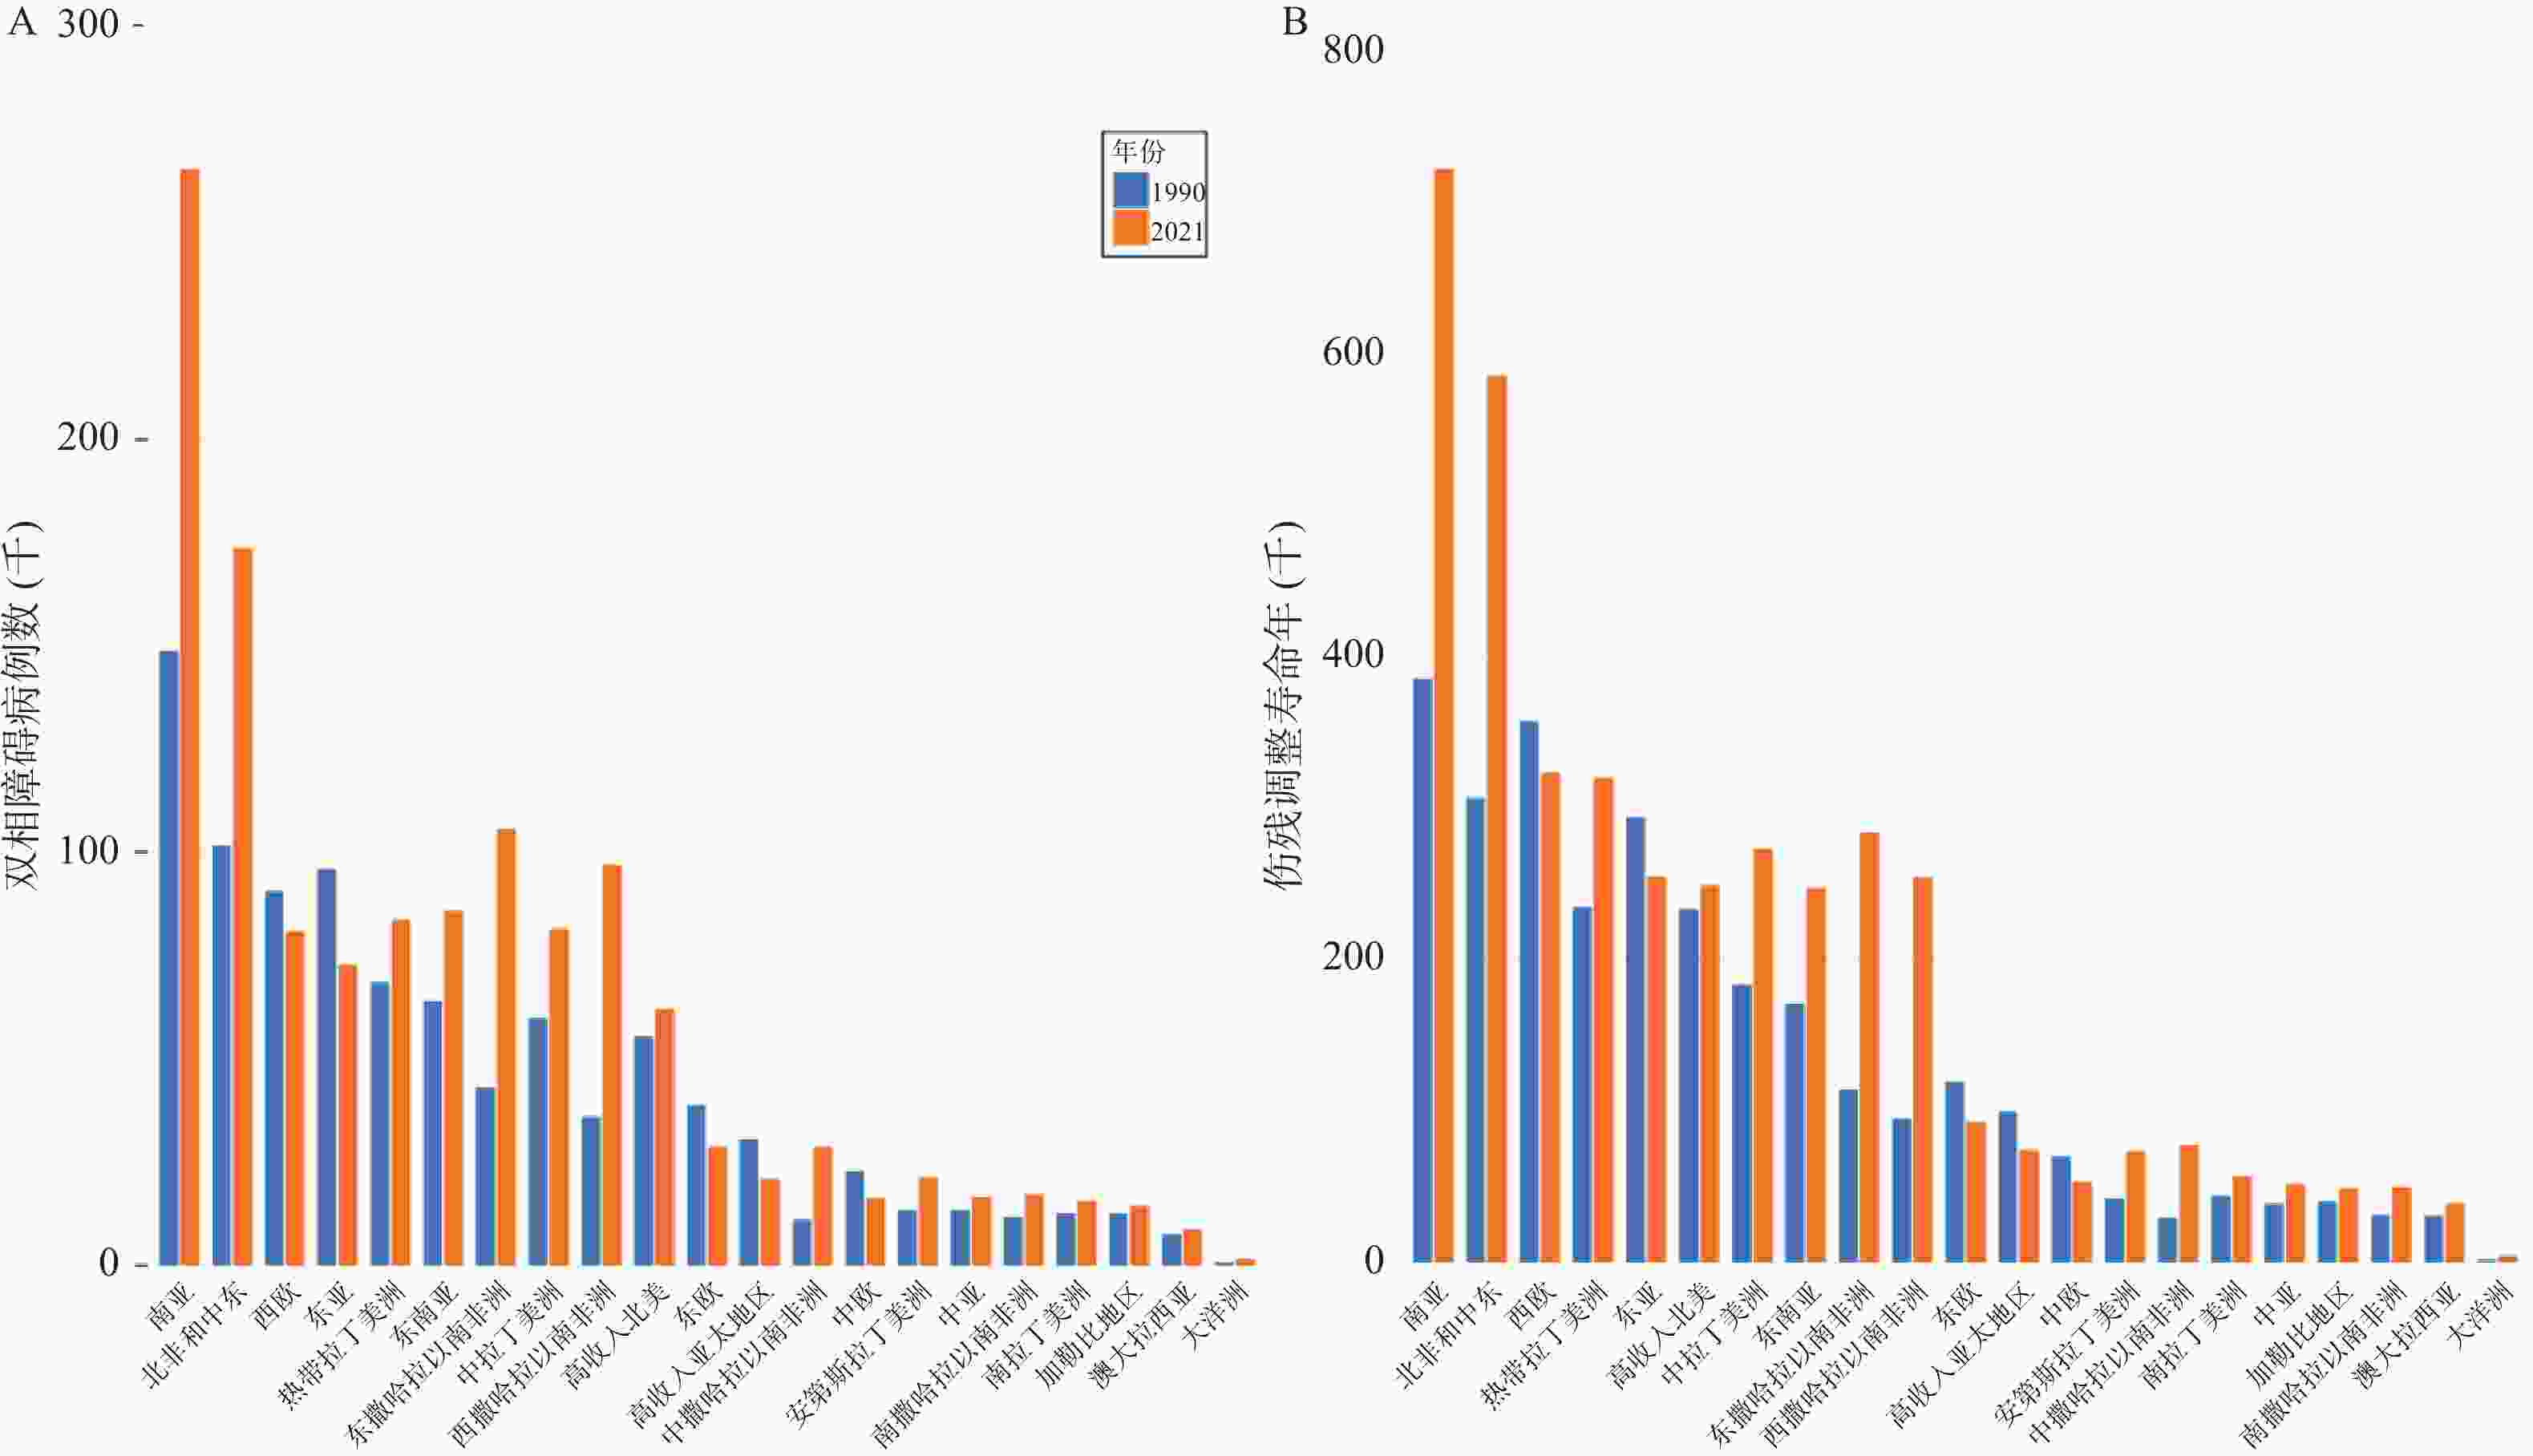
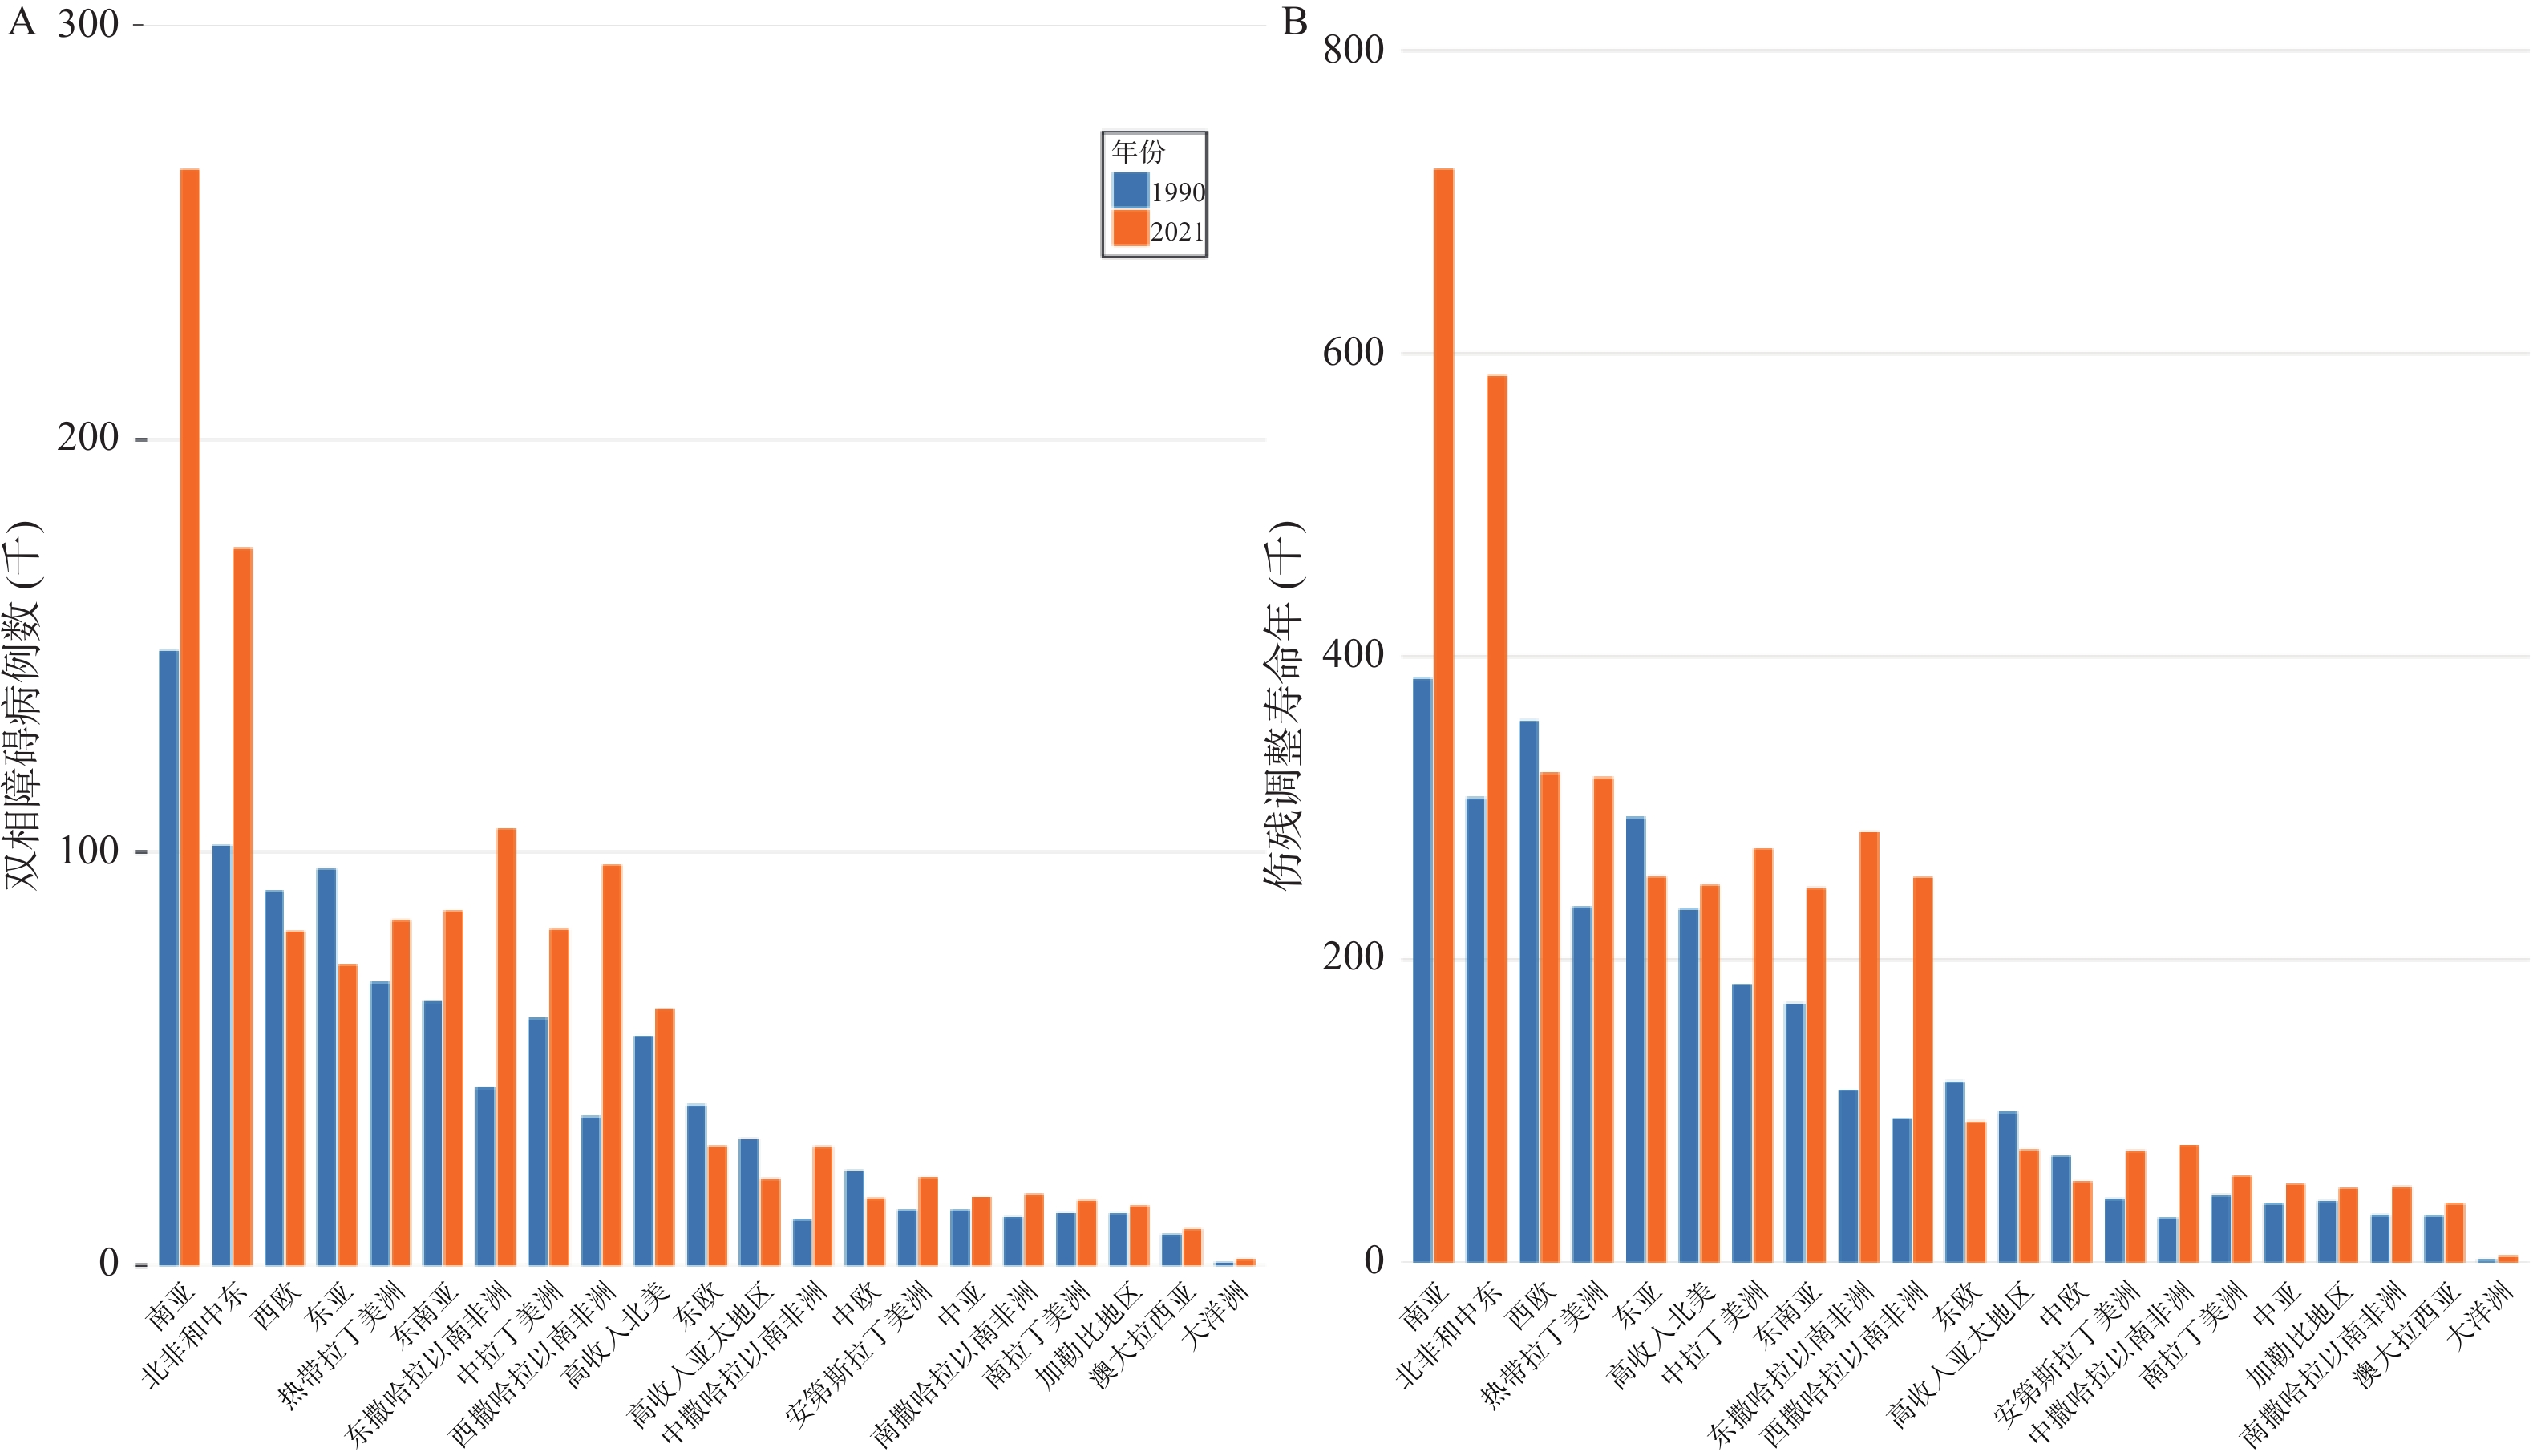
图 2 地区层面双相障碍发病例数和伤残调整寿命年数情况
A:发病例数;B:伤残调整寿命年数。
Figure 2. Number of incident cases and DALYs of bipolar disorder at the regional level
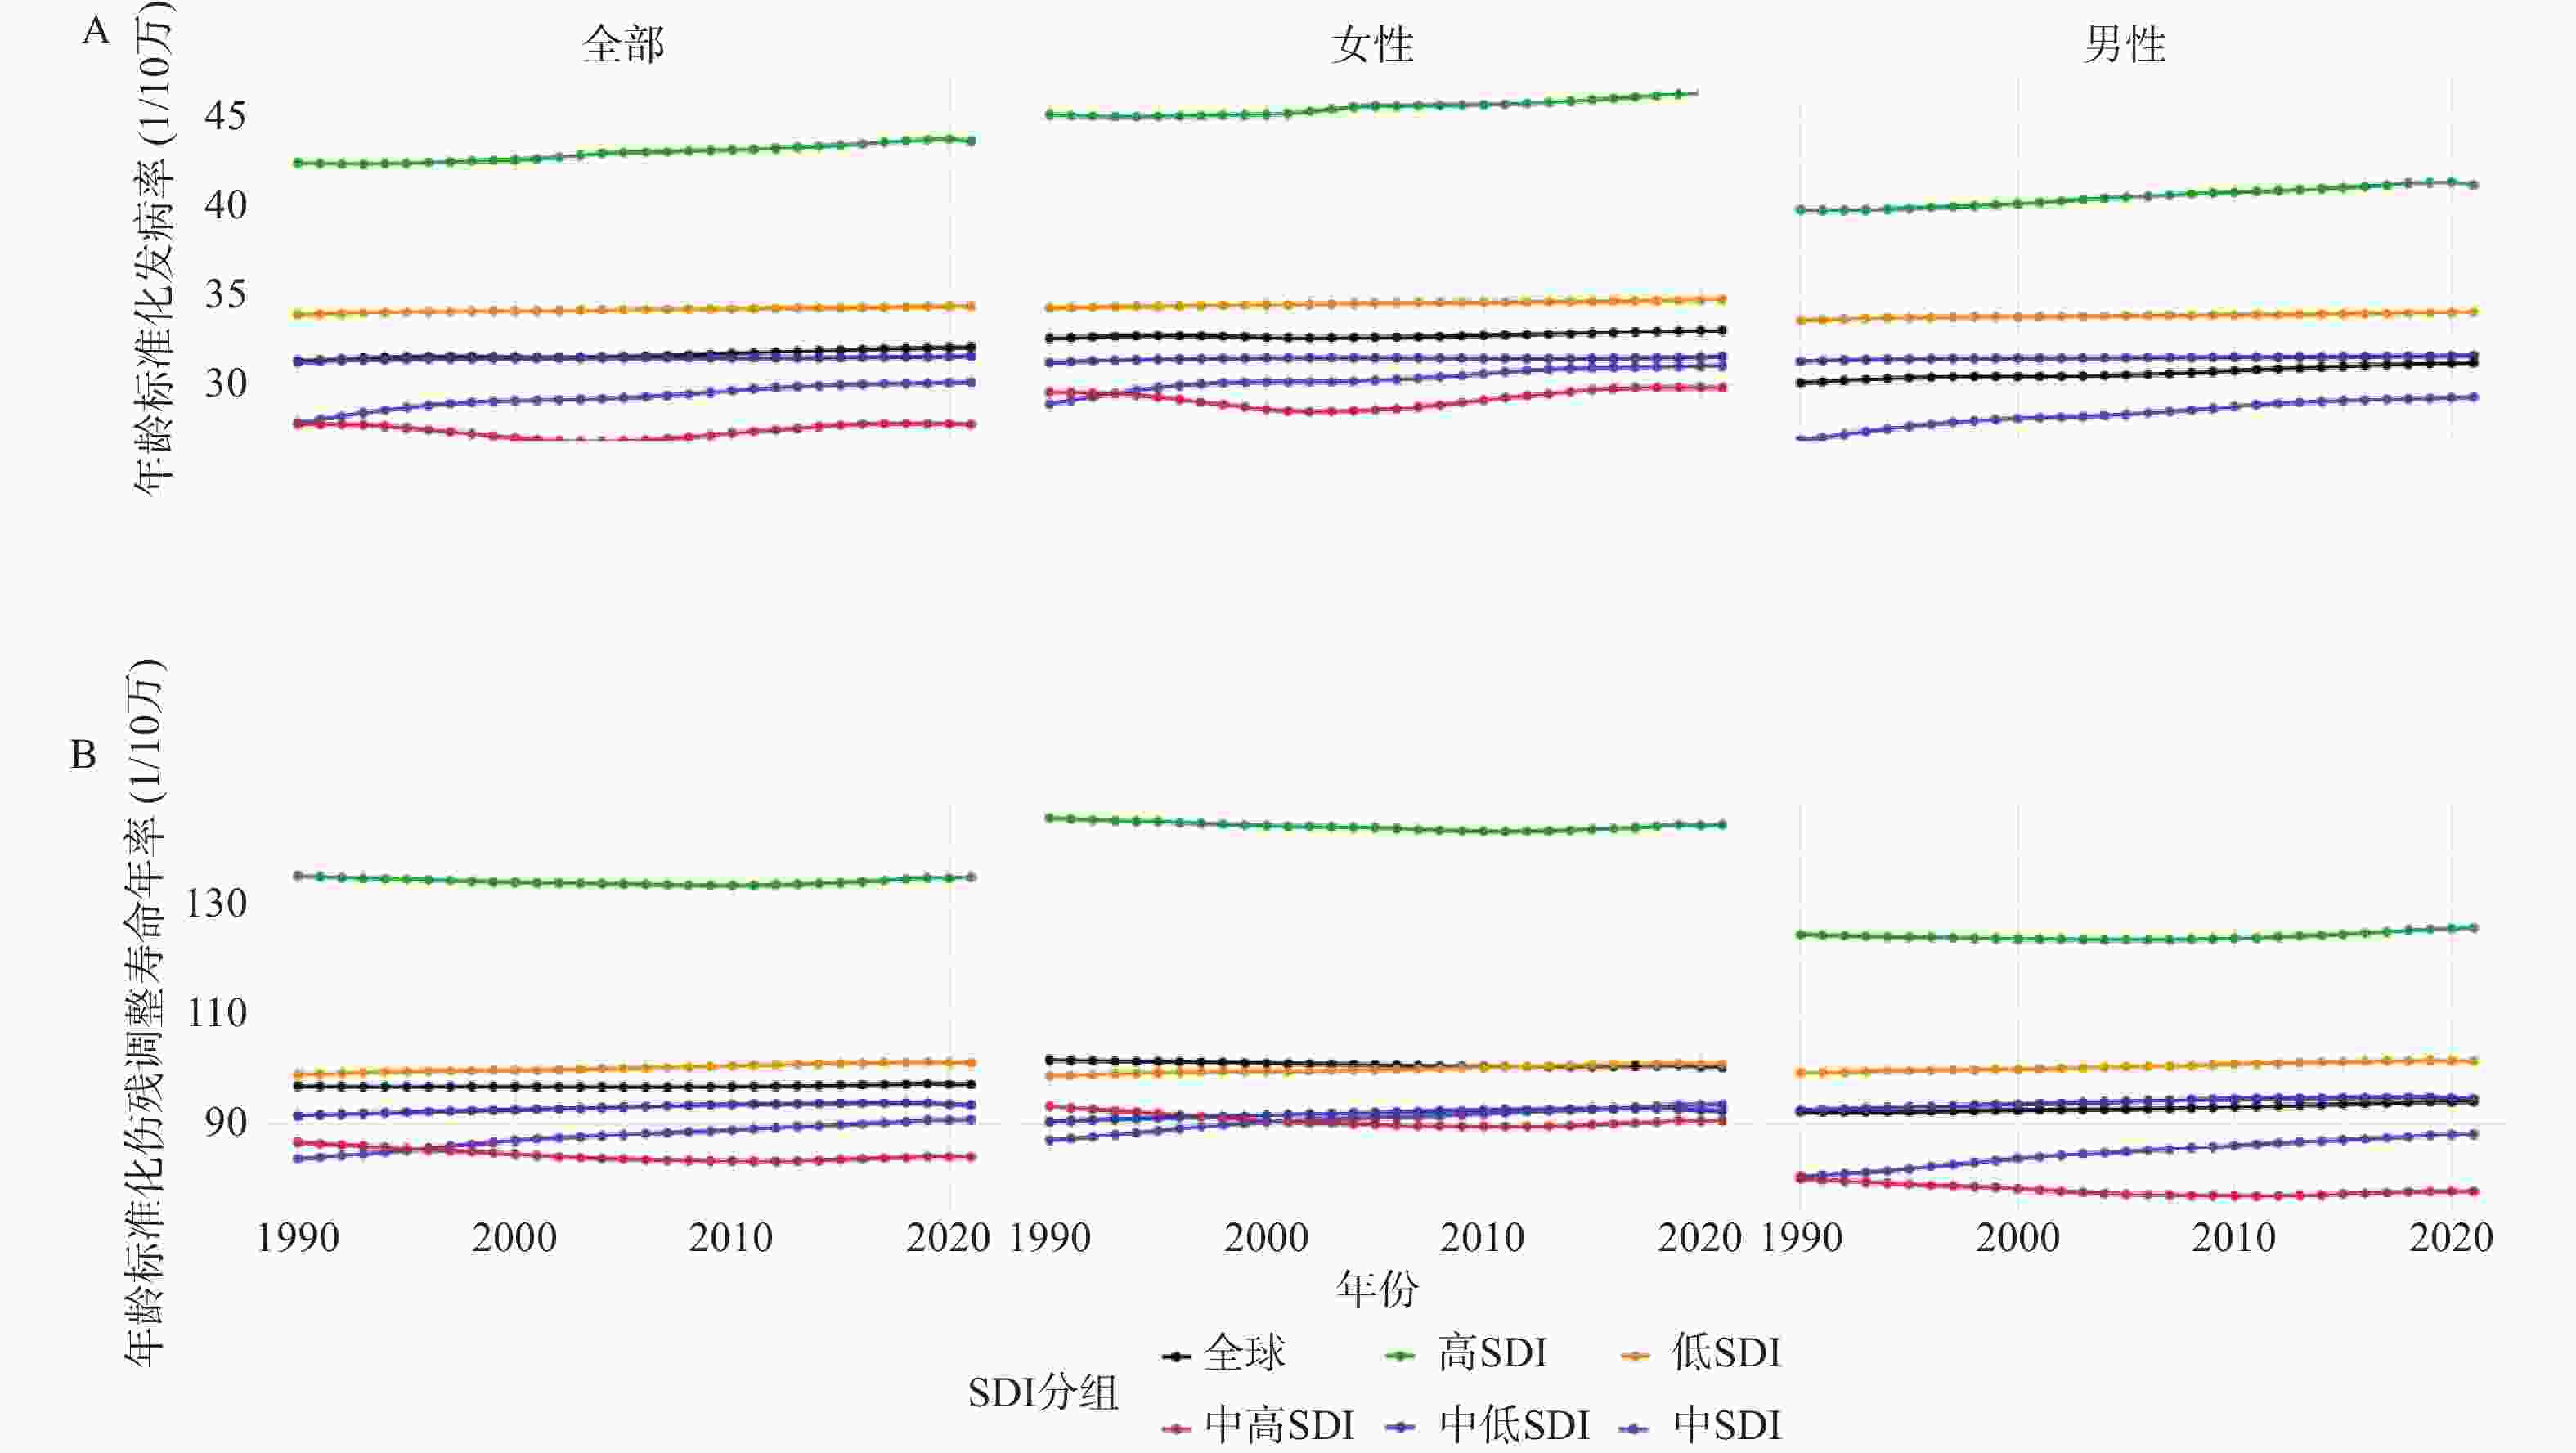
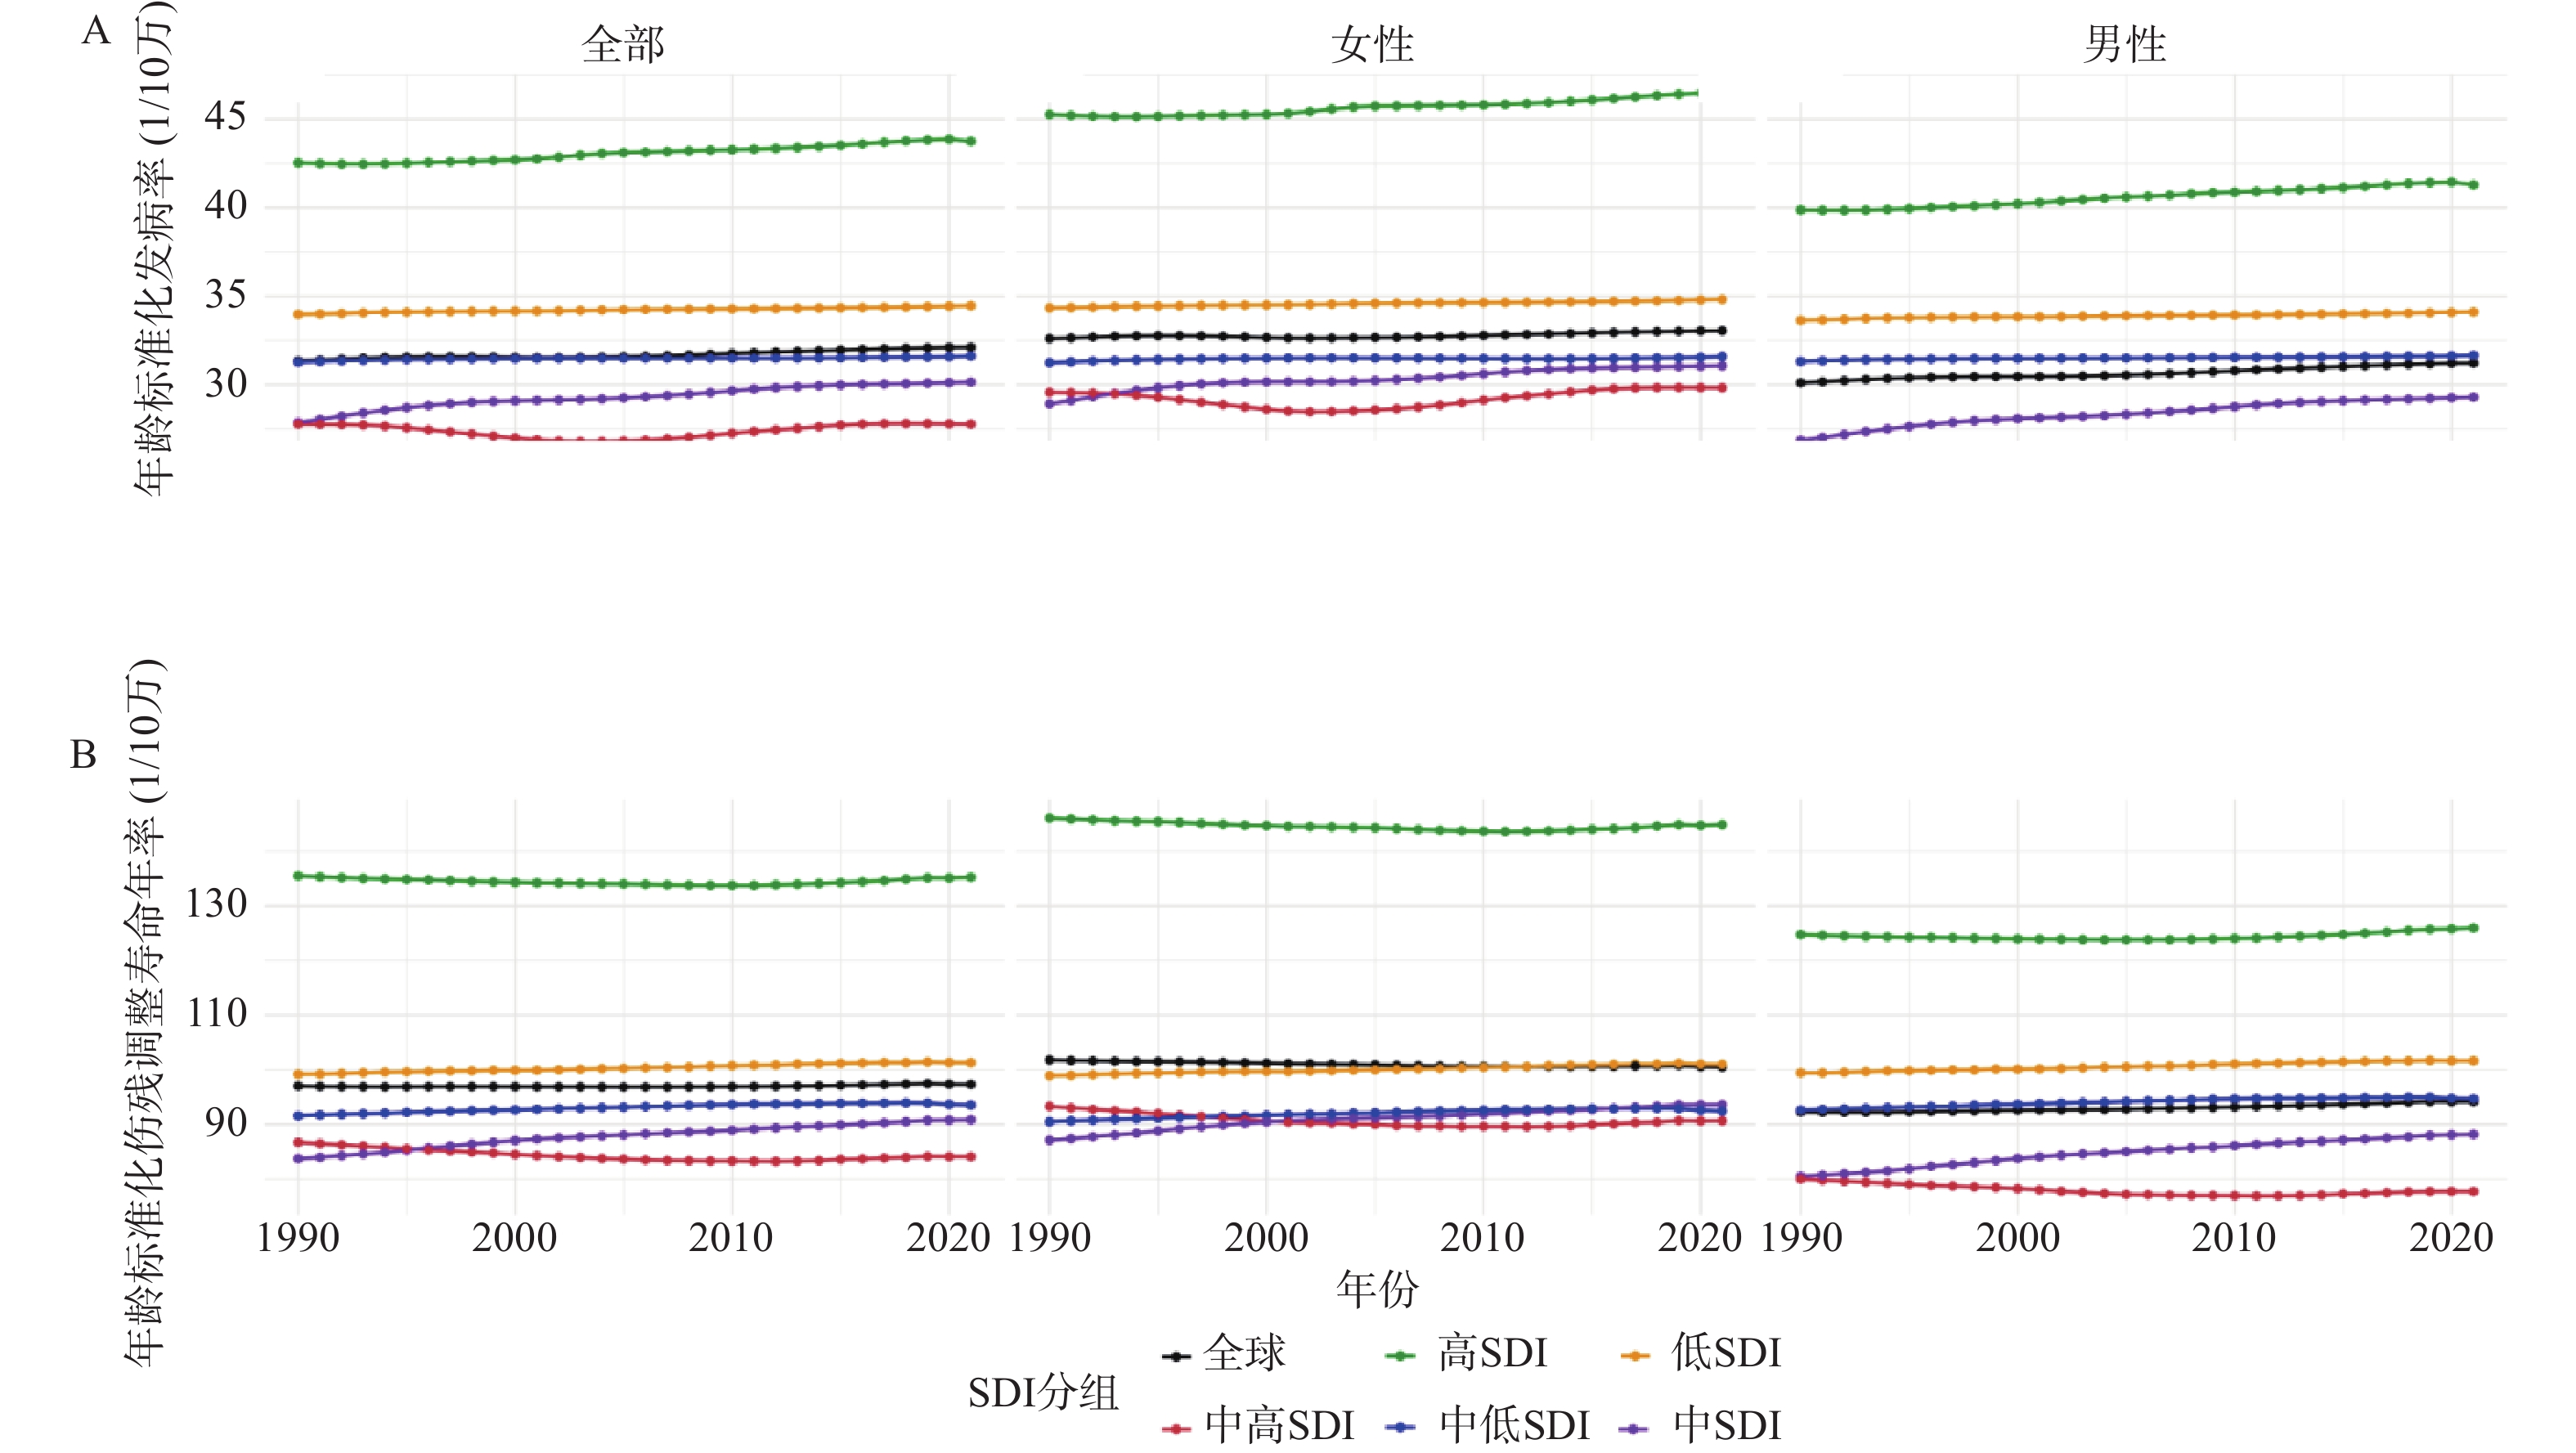
图 3 1990—2021年不同SDI水平年龄标准化率变化趋势
A:年龄标准化发病率;B:年龄标准化伤残调整寿命年率(ASDR)。
Figure 3. Trends in age-standardized rates of bipolar disorder across different SDI levels,1990—2021
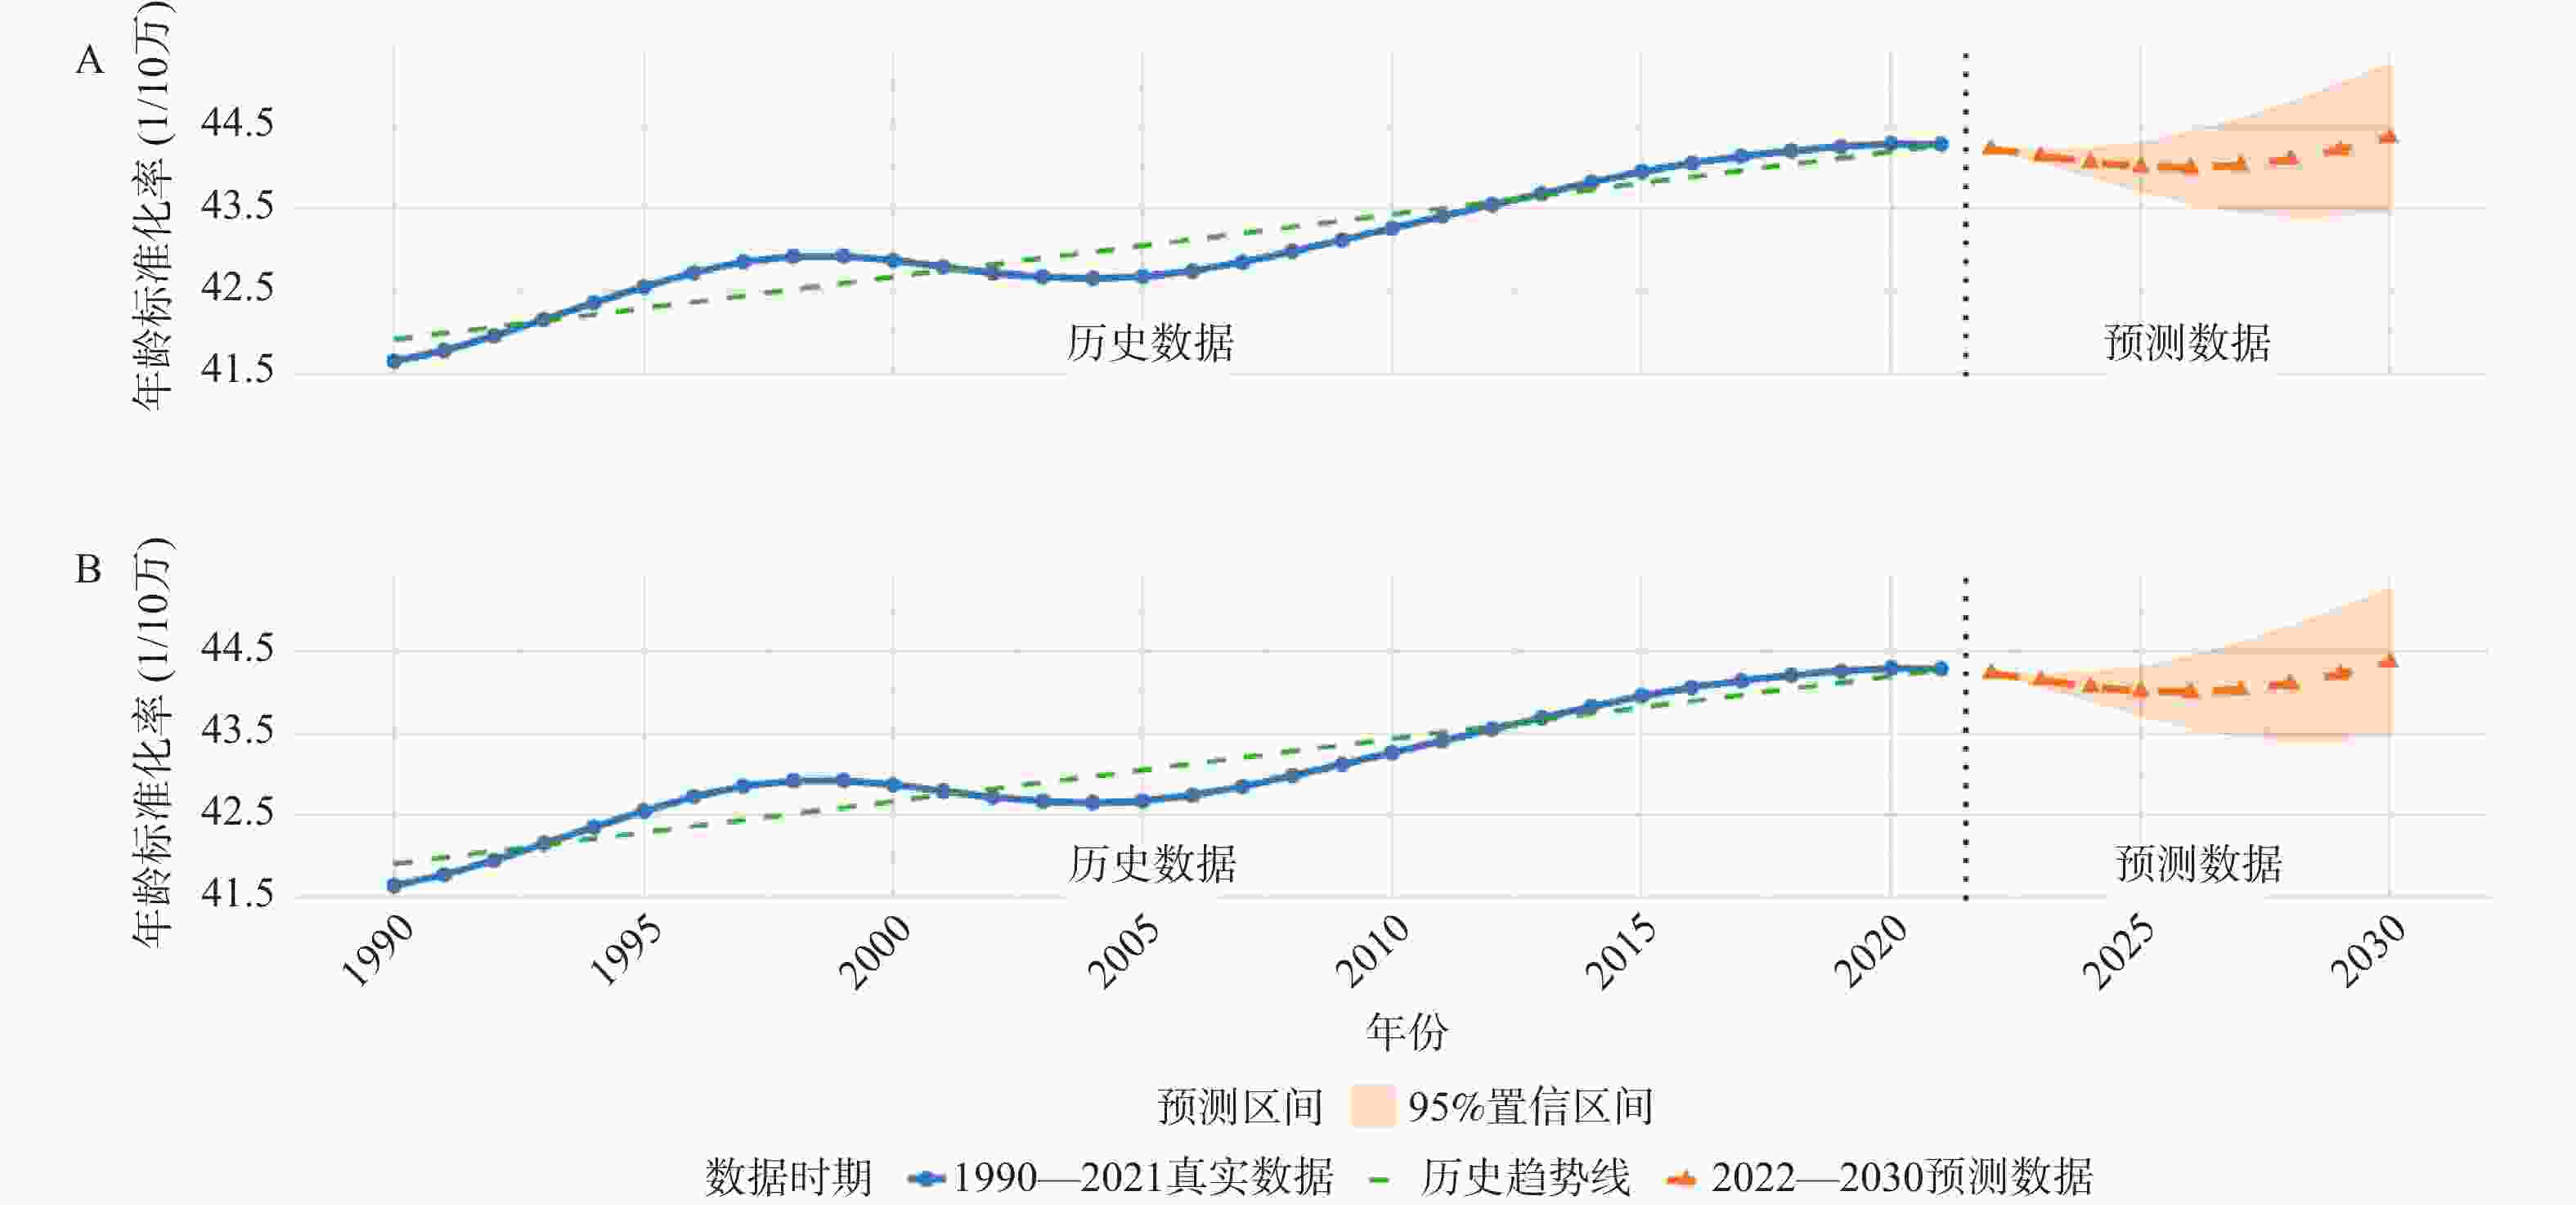
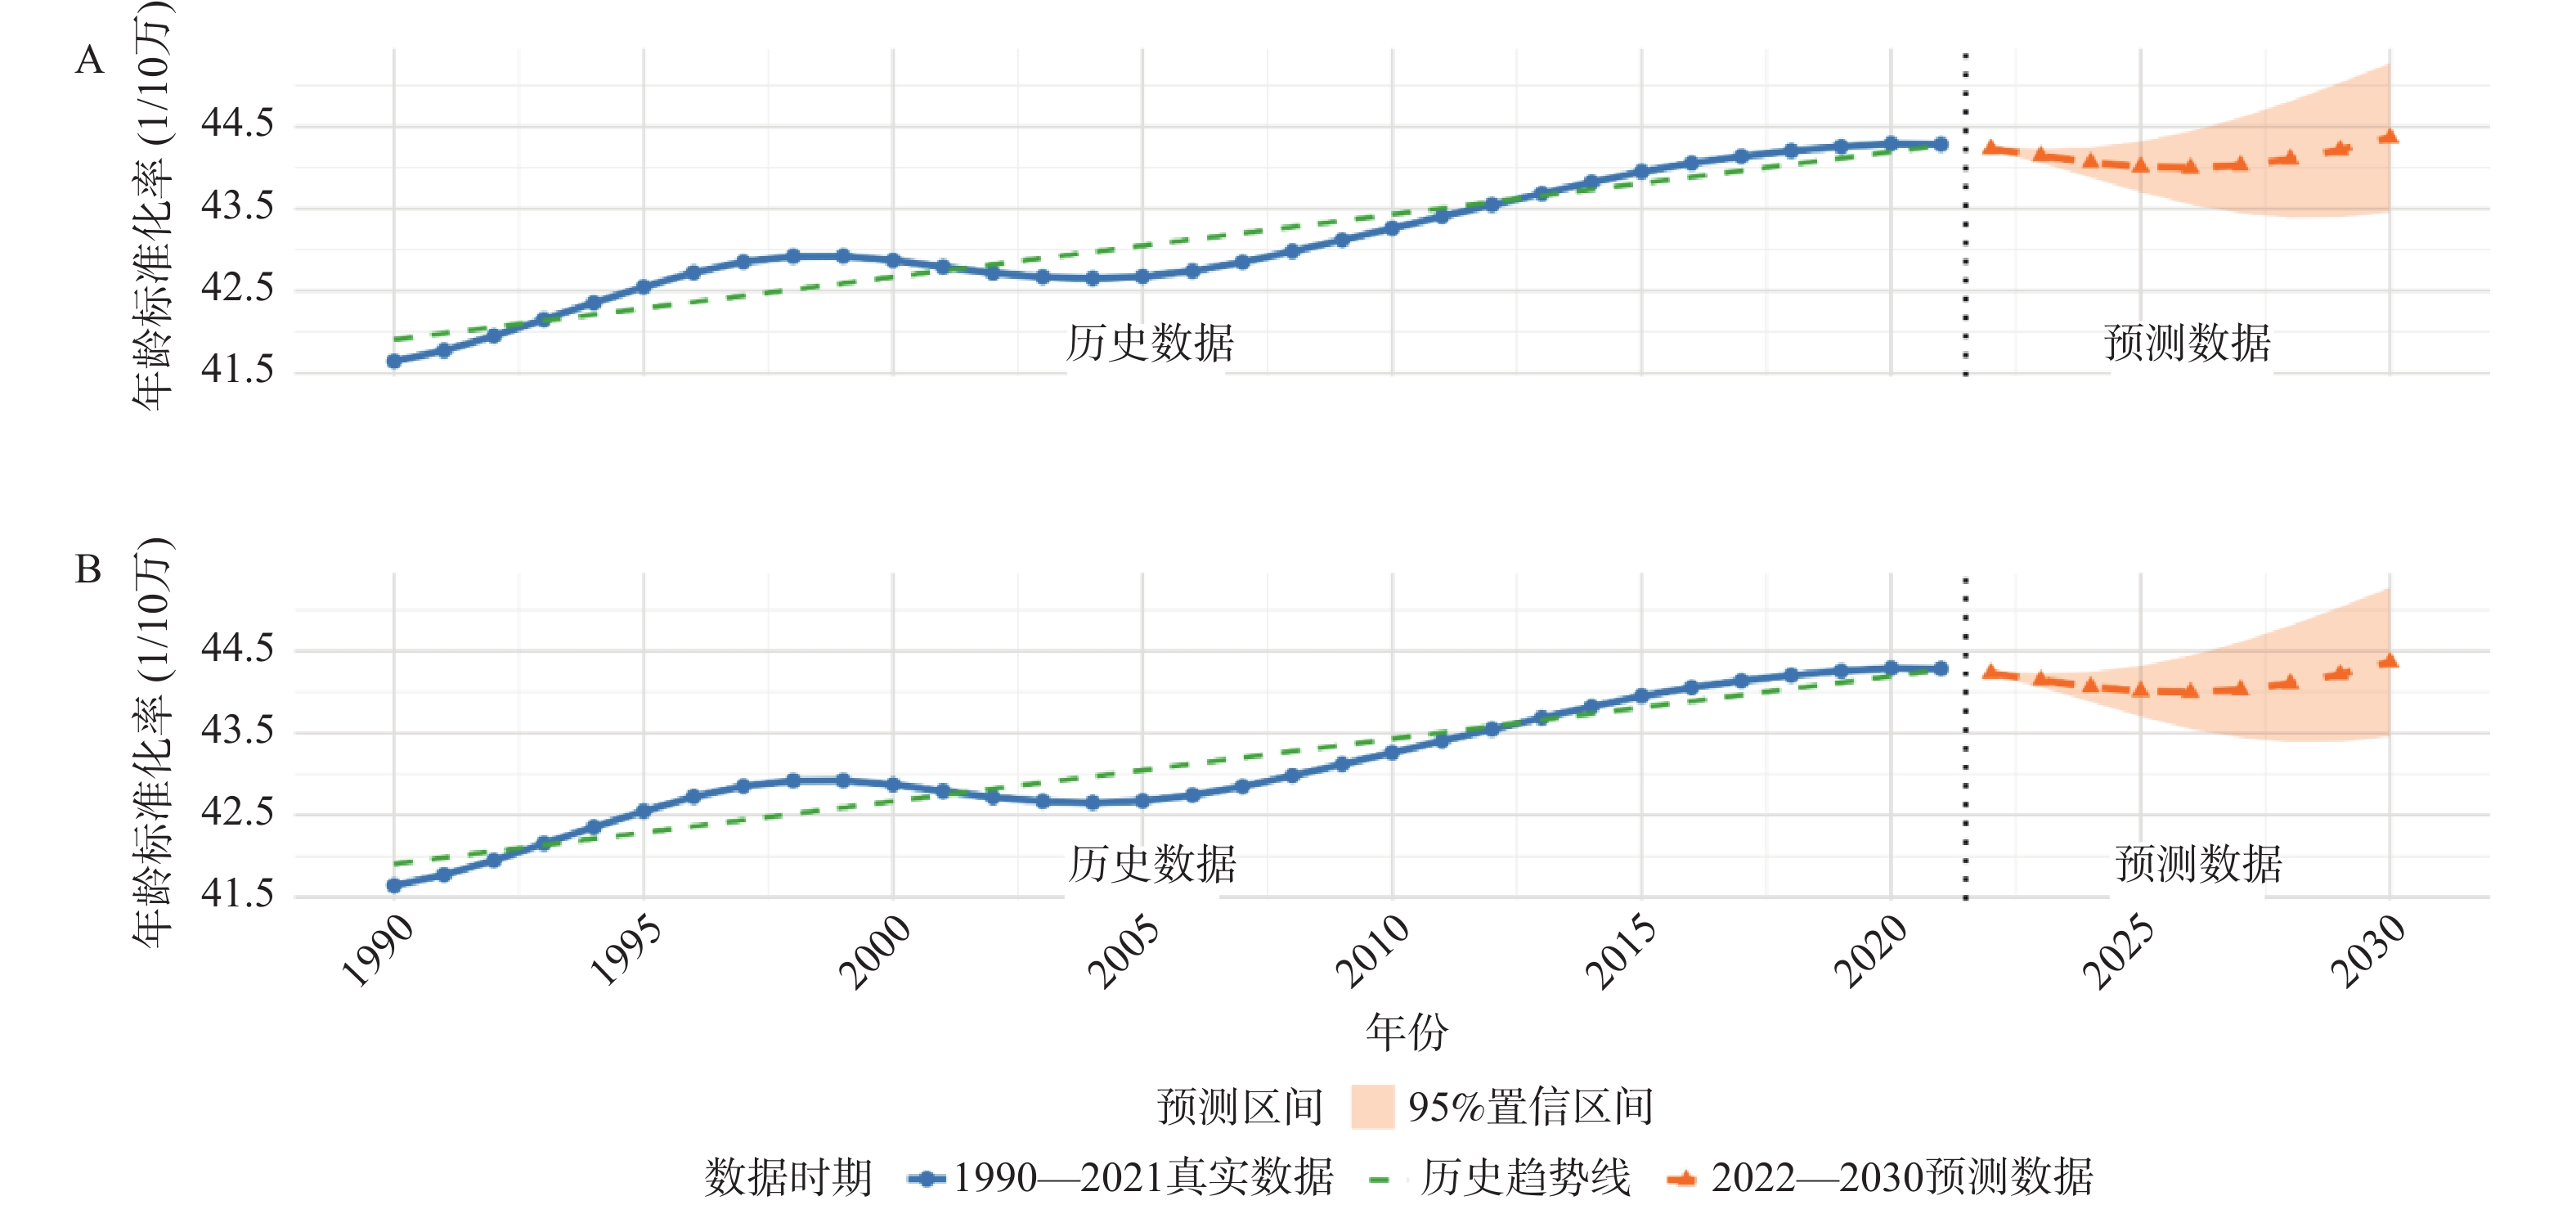
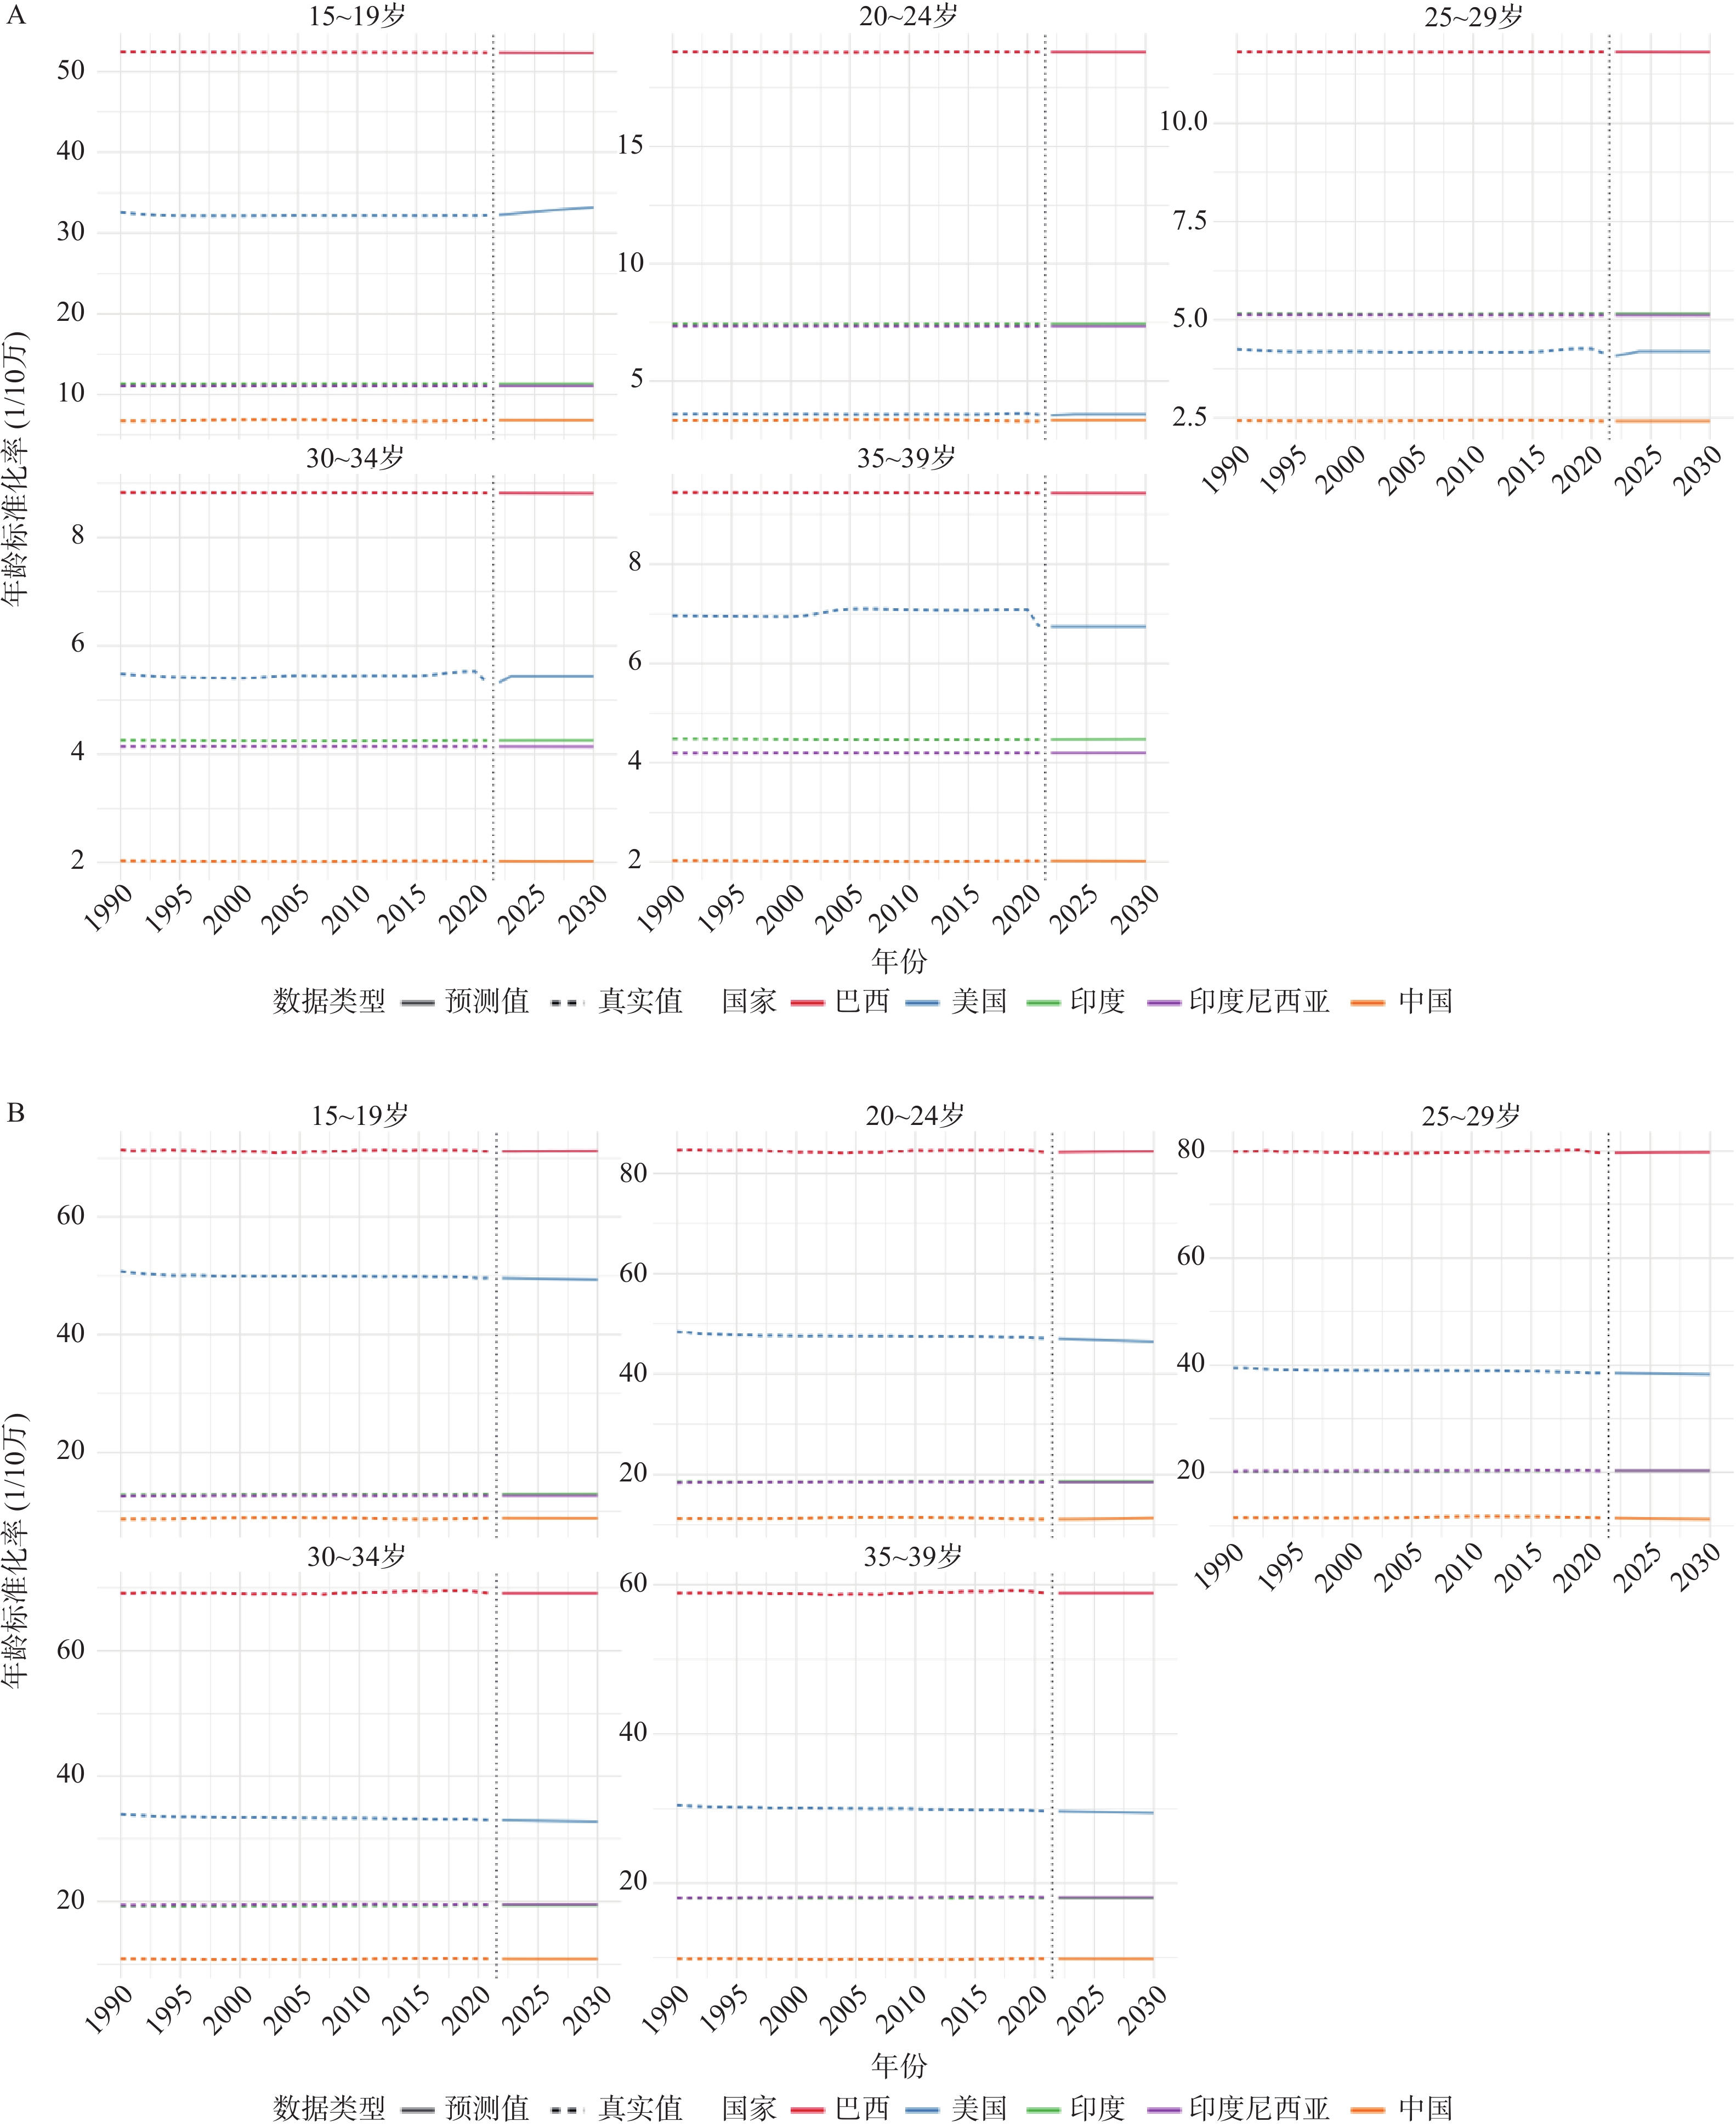
图 4 全球标准化率趋势与预测情况
A:年龄标准化发病率(ASIR);B:年龄标准化伤残调整寿命年率(ASDR)。
Figure 4. Global trends and projections of age-standardized rates of bipolar disorder
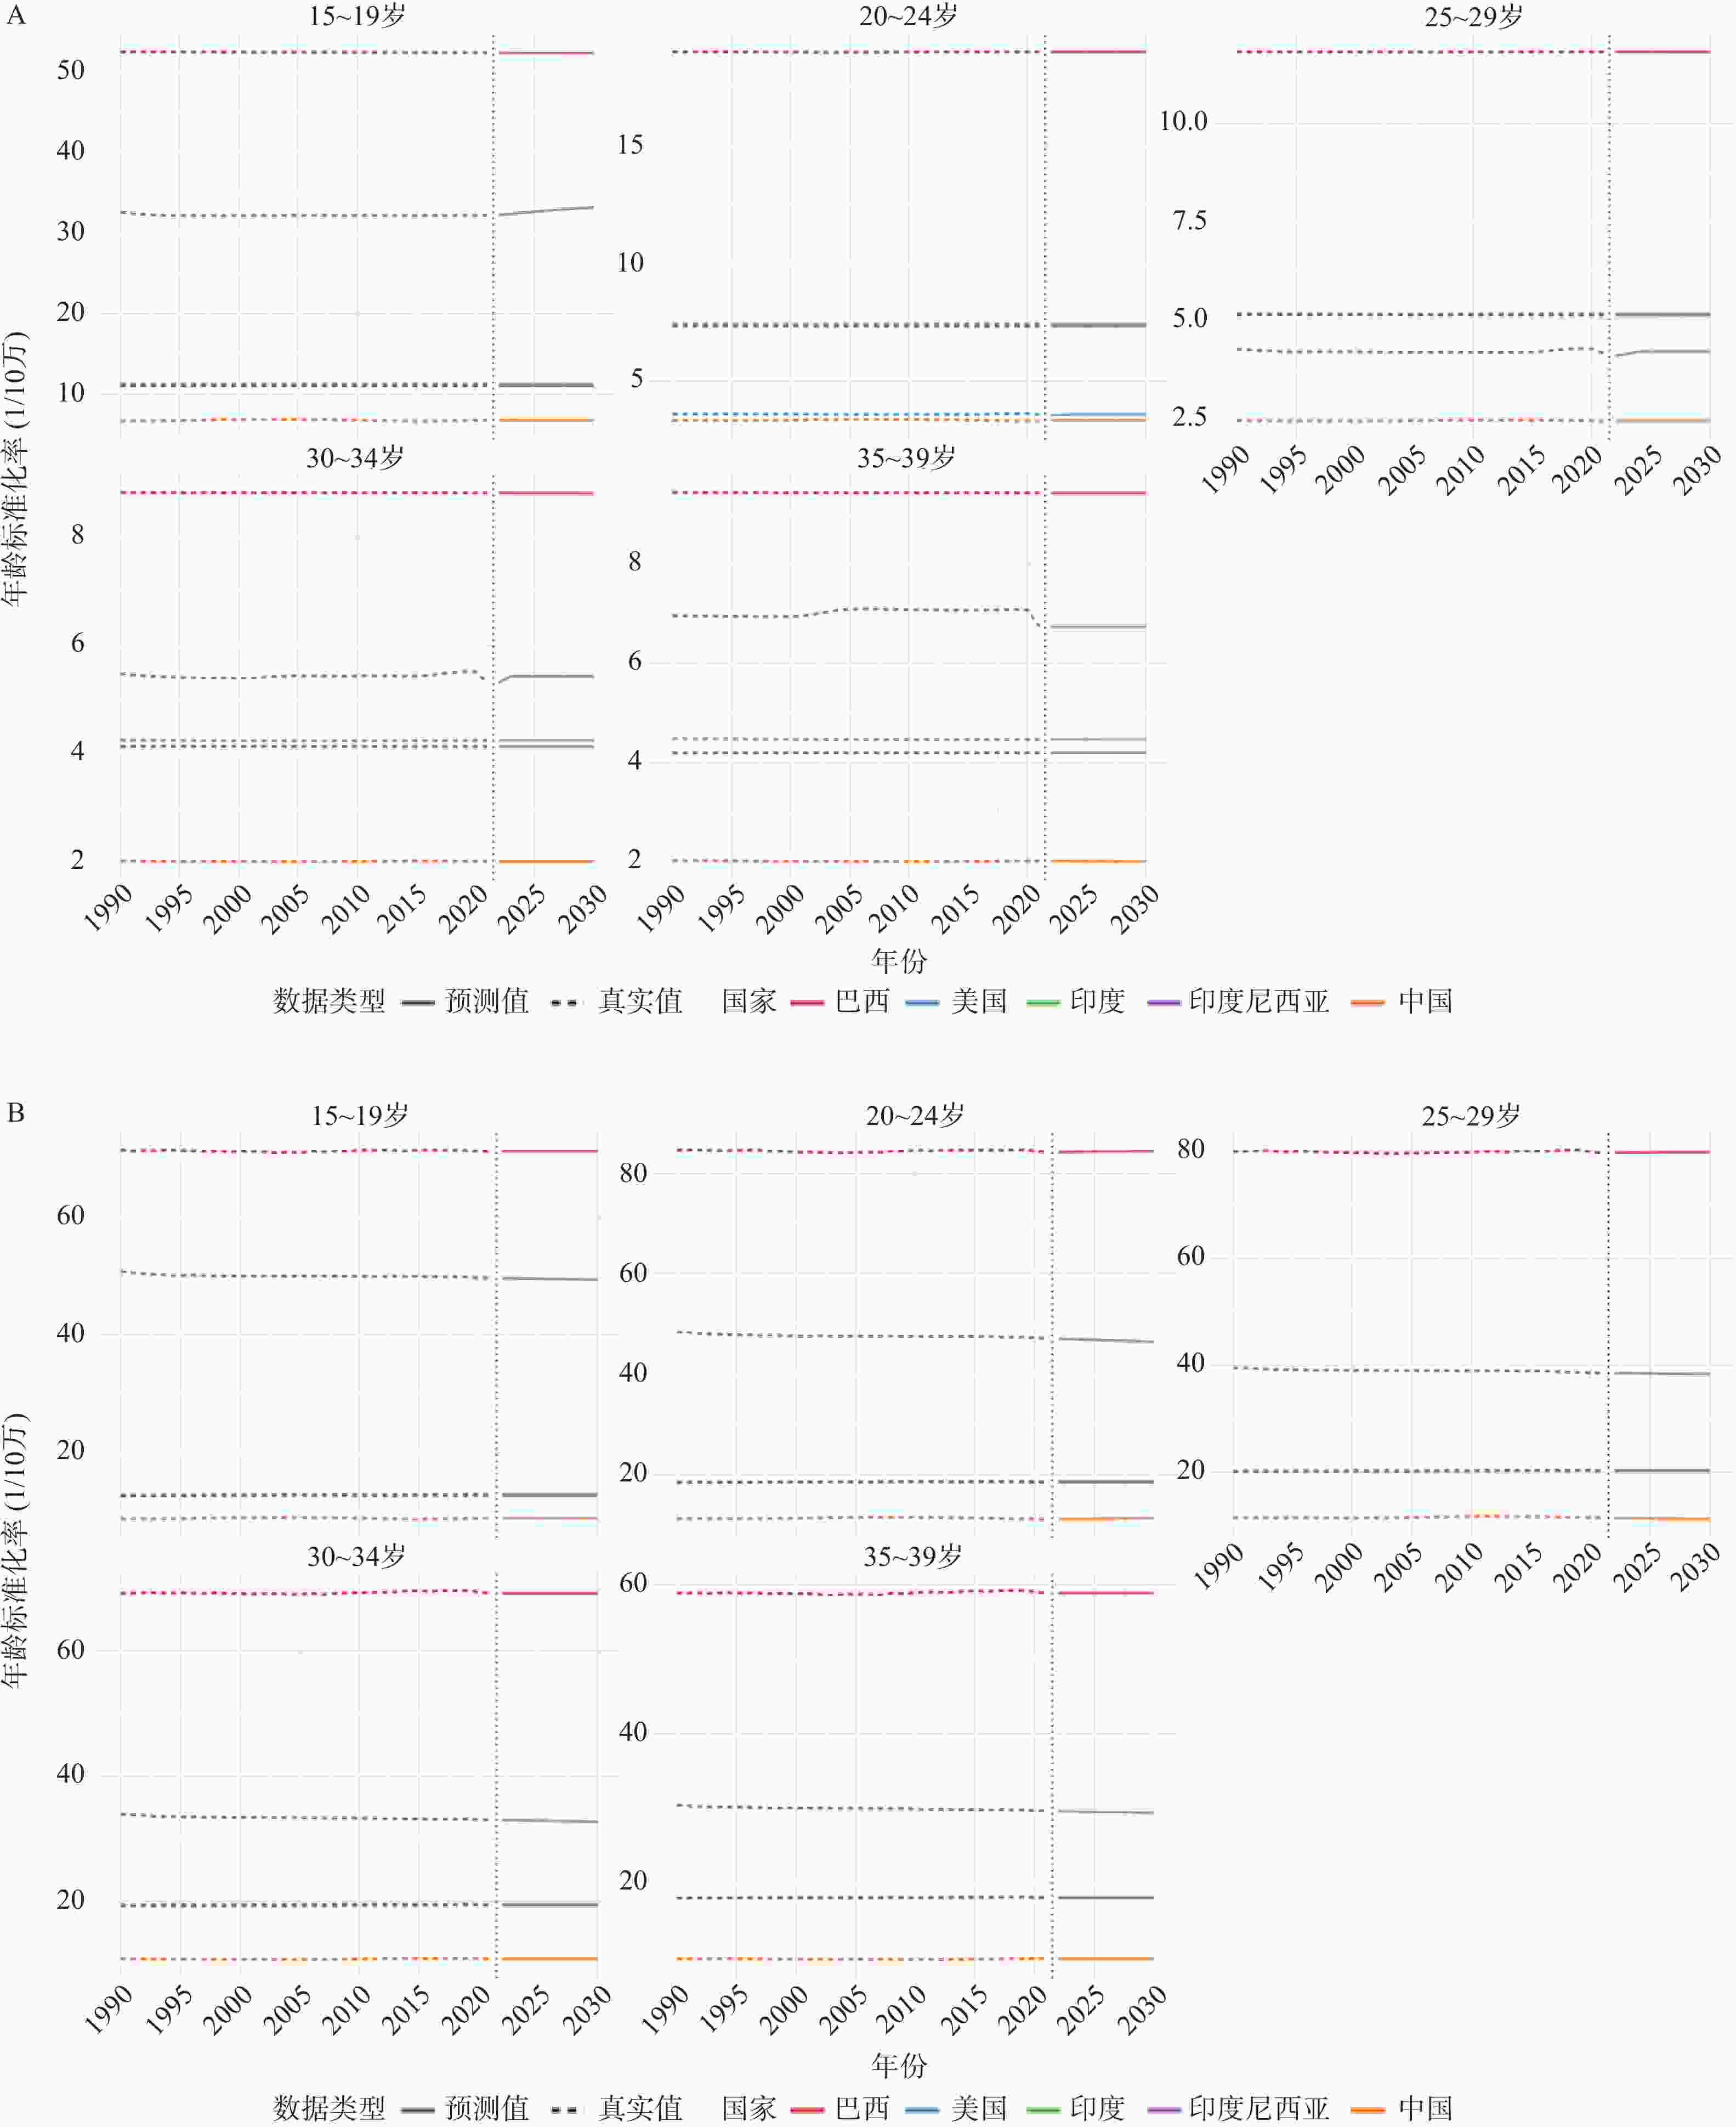
图 8 5个主要人口大国标准化率预测情况
A:年龄标准化发病率(ASIR);B:年龄标准化伤残调整寿命年率(ASDR)。
Figure 8. Predicted trends in age-standardized rates of bipolar disorder for the five most populous countries
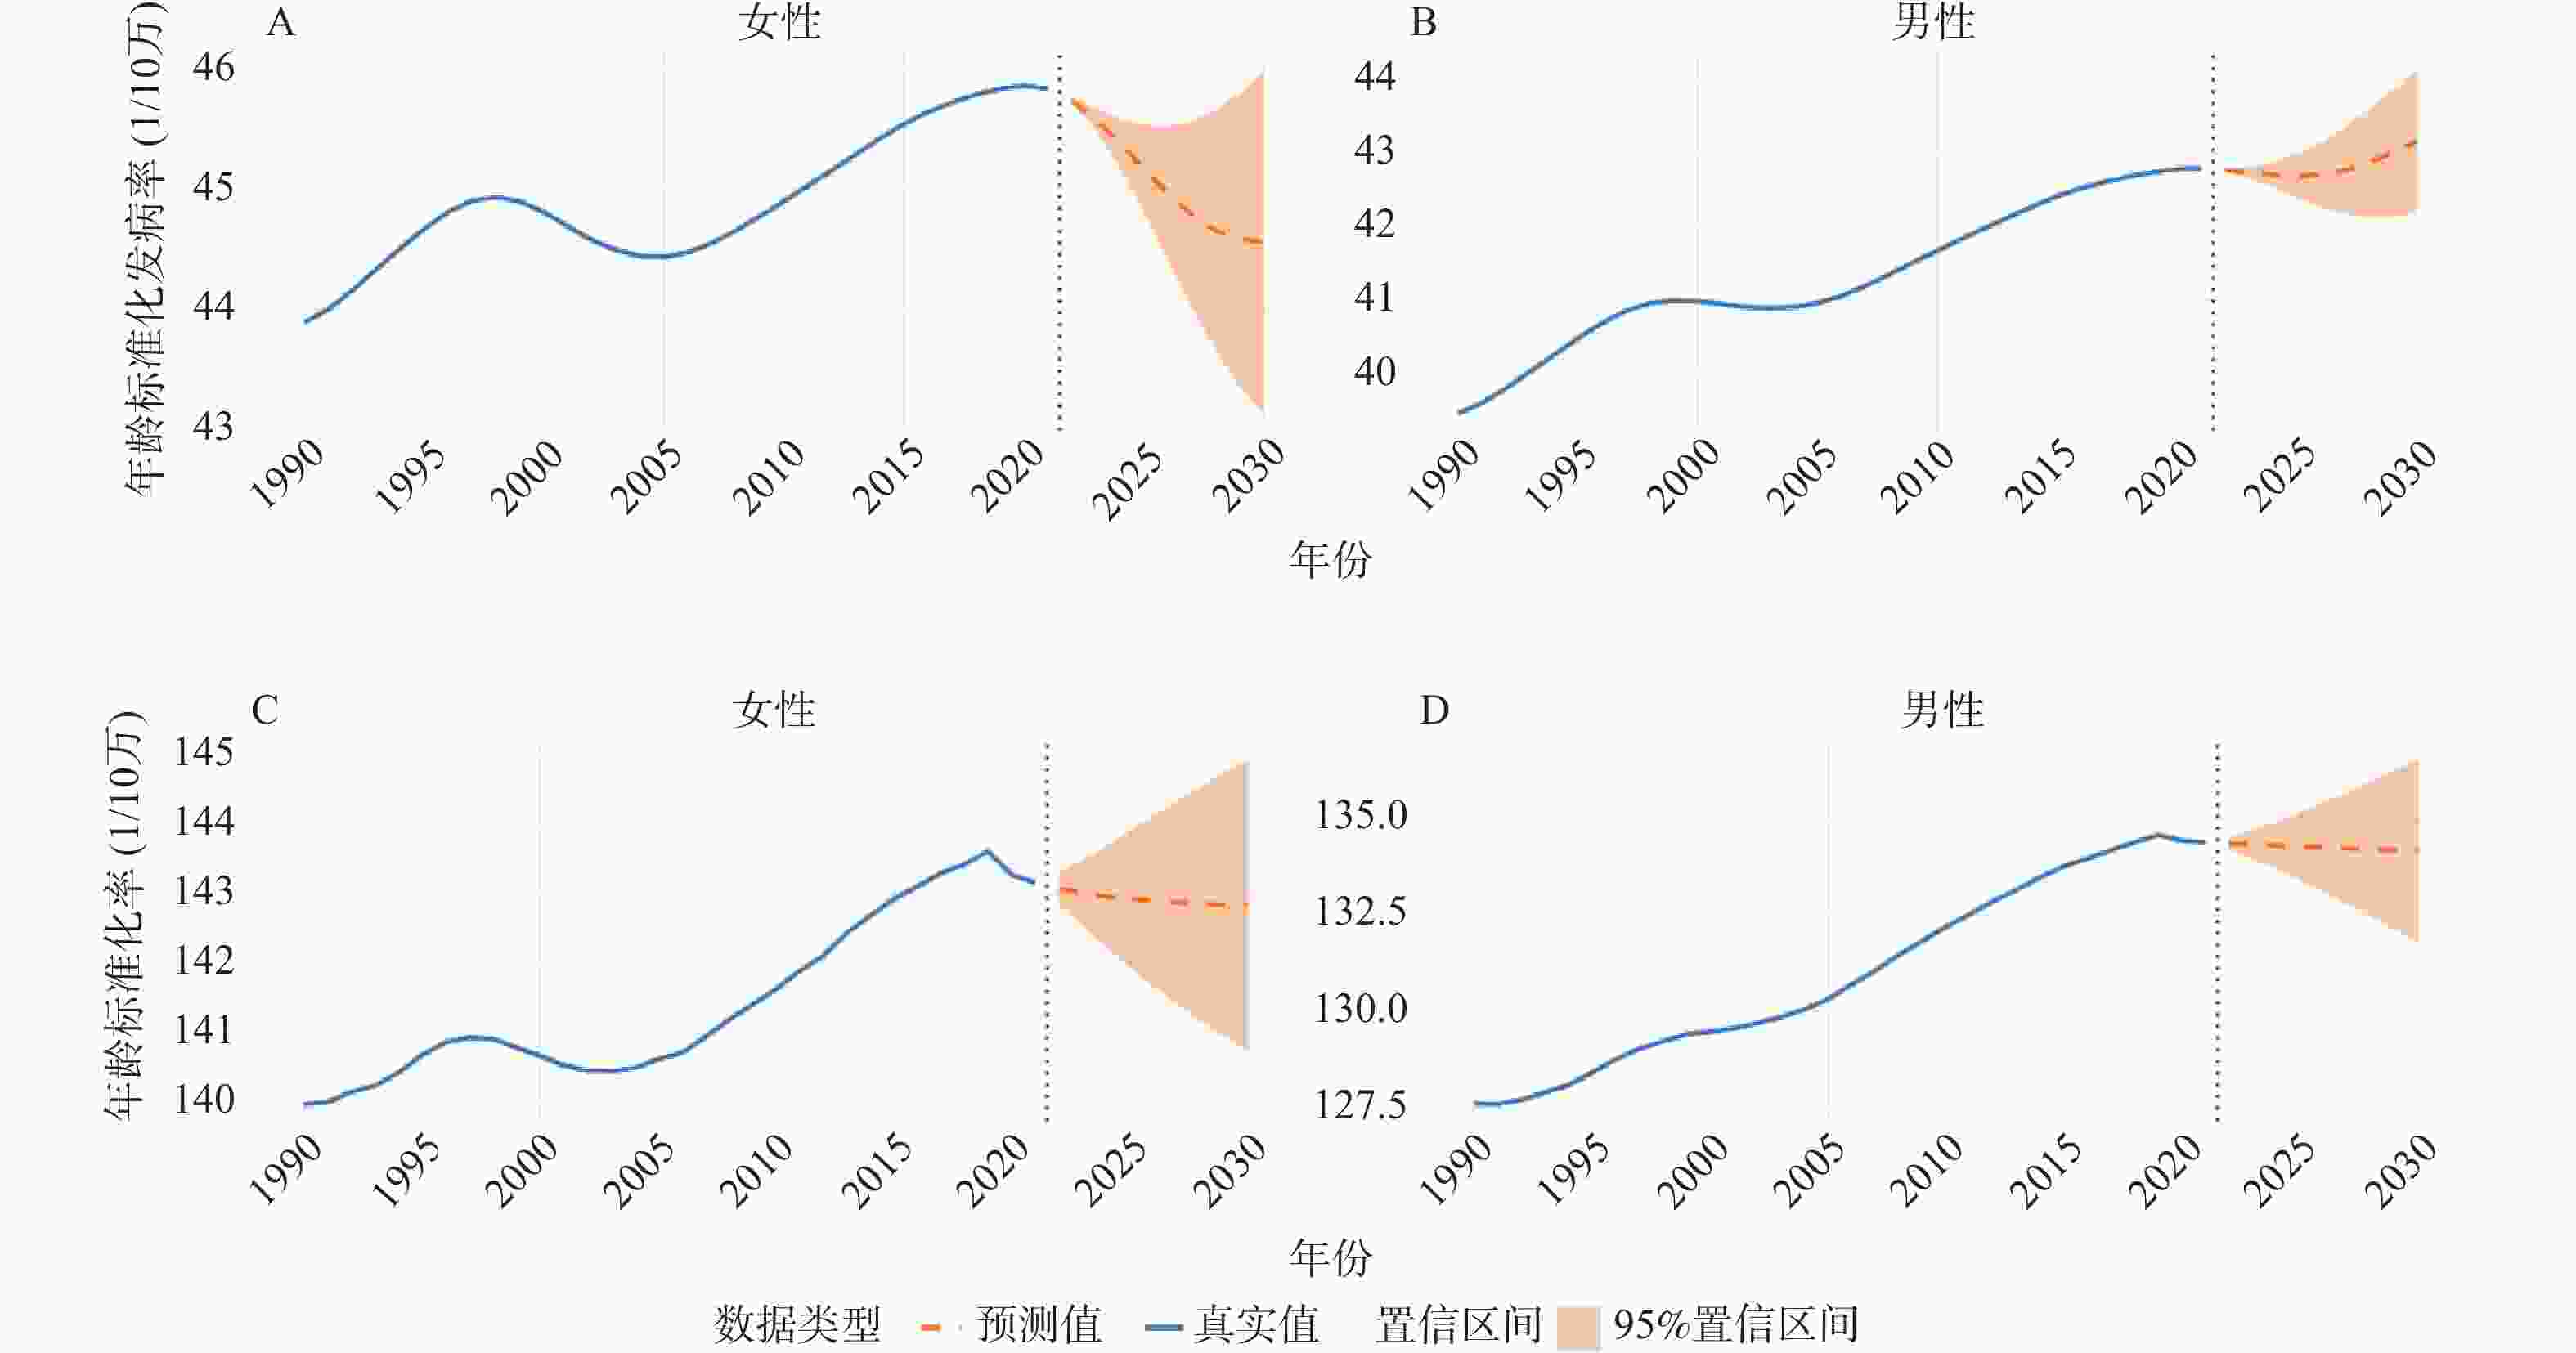
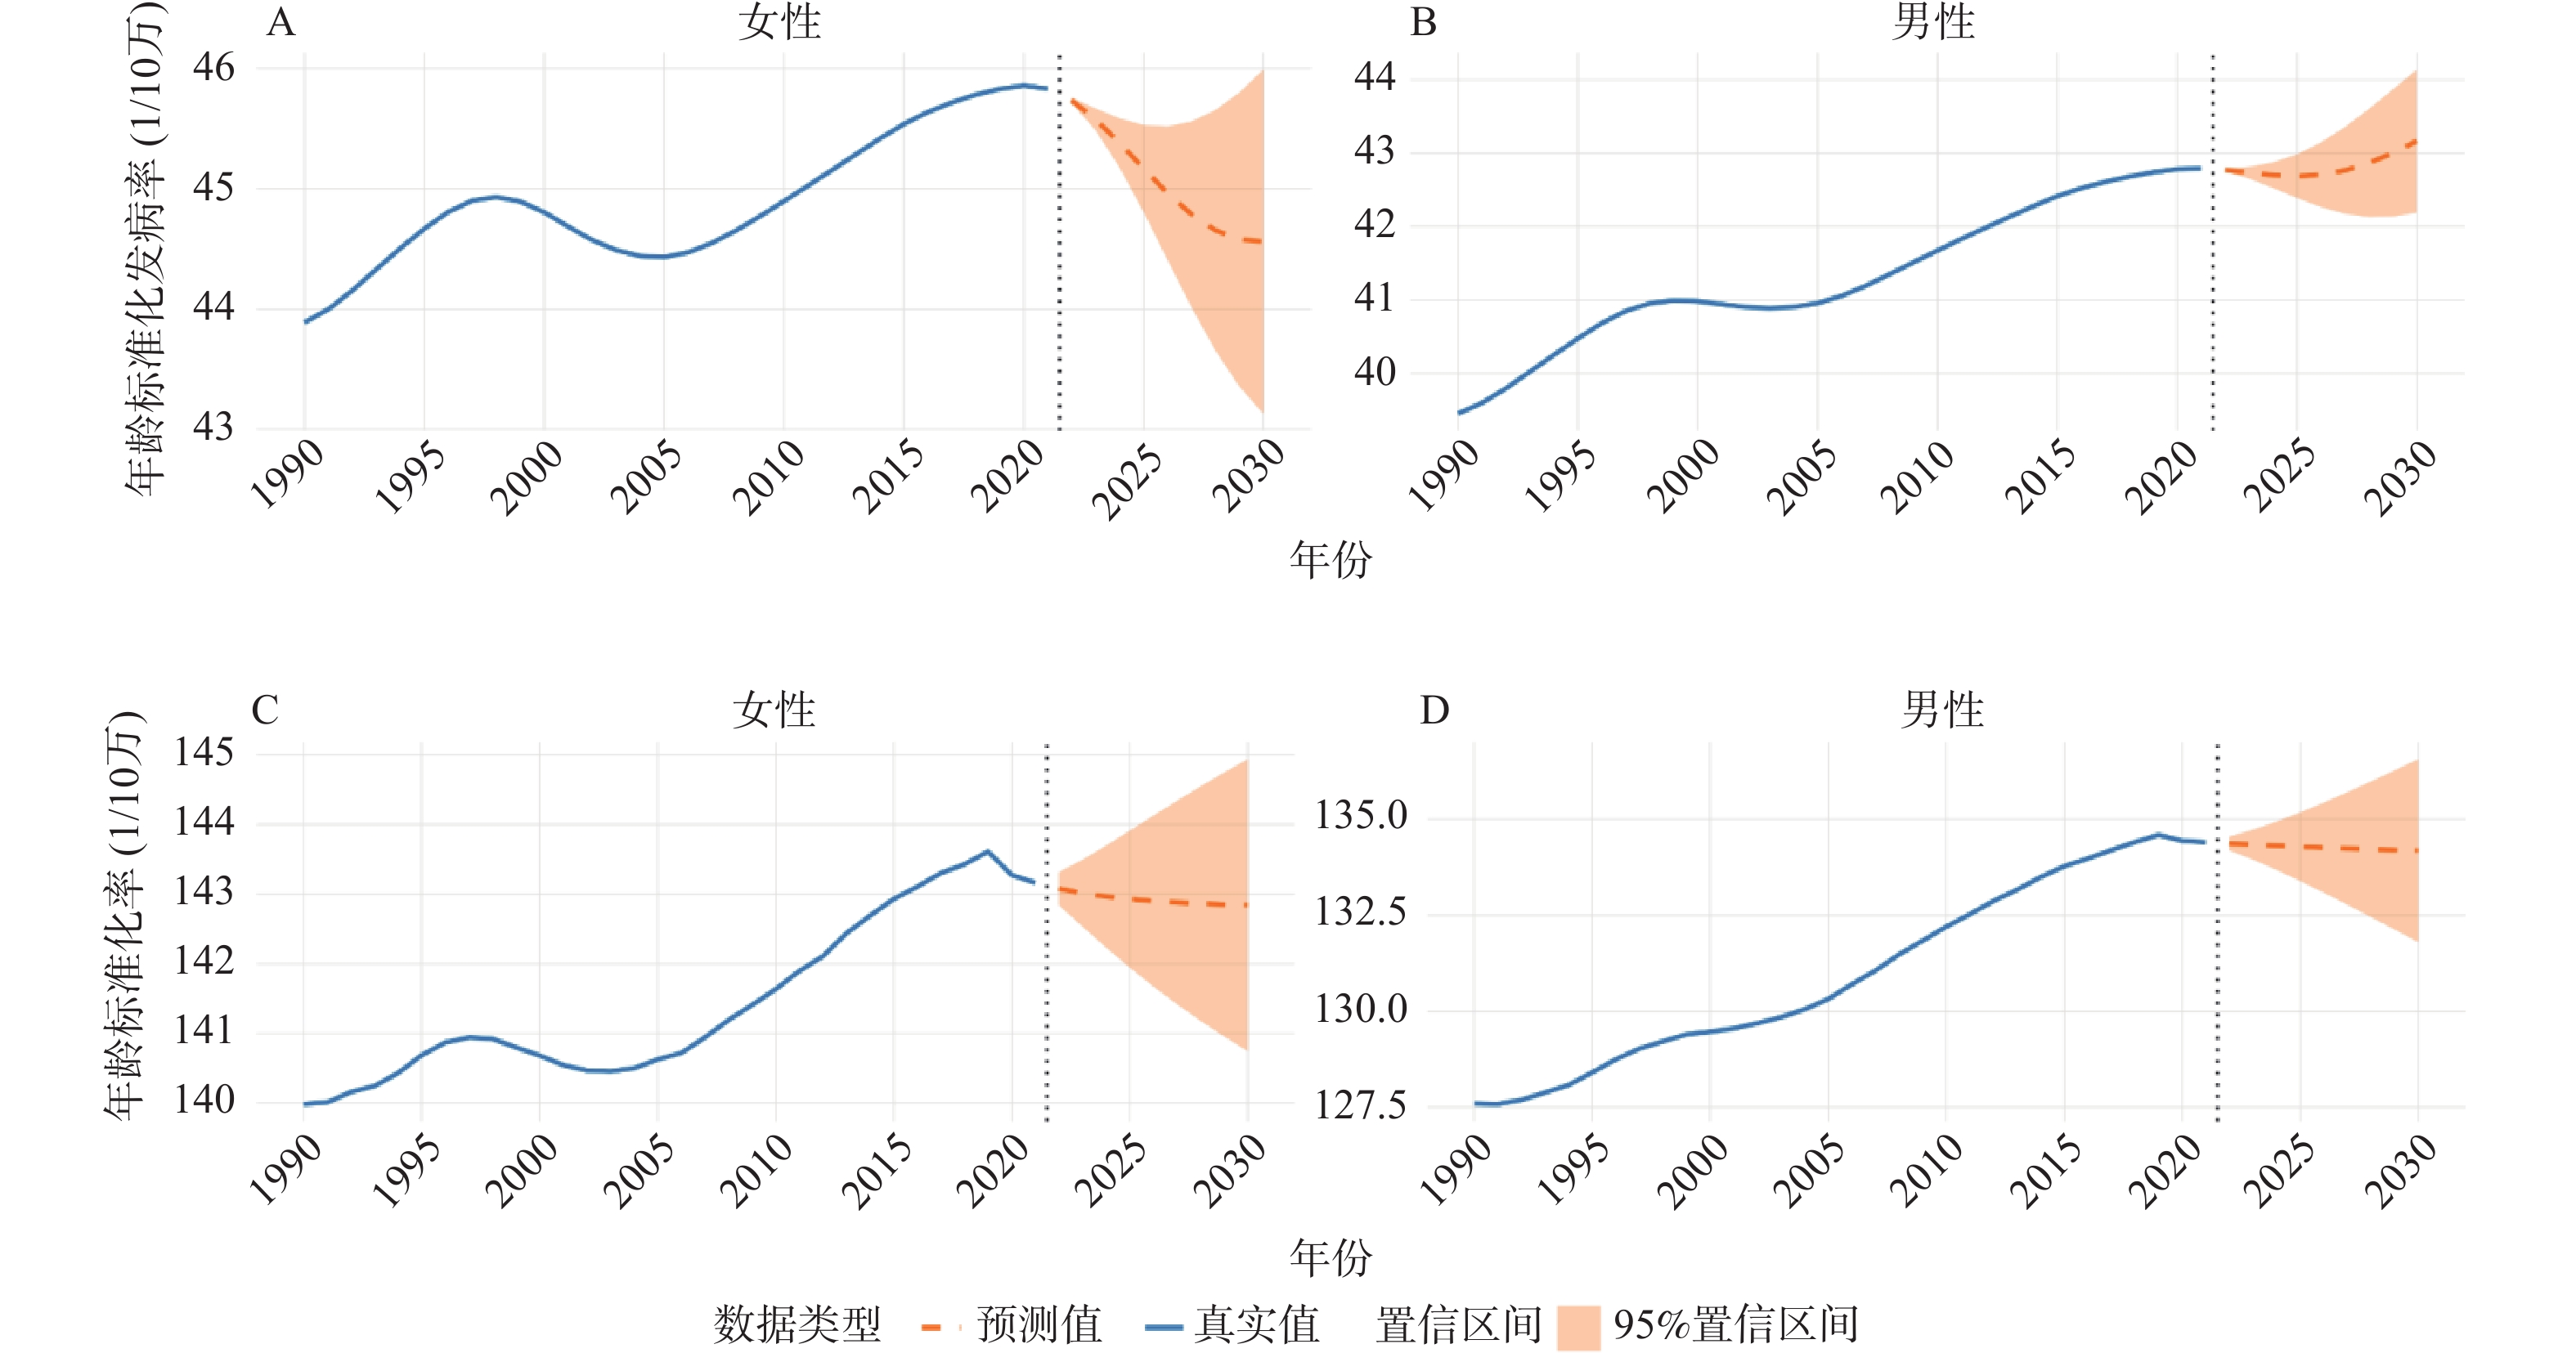
图 5 不同性别年龄标准化率预测情况
A:女性ASIR;B:男性ASIR;C:女性ASDR;D:男性ASDR。
Figure 5. Predicted trends in age-standardized rates of bipolar disorder by sex
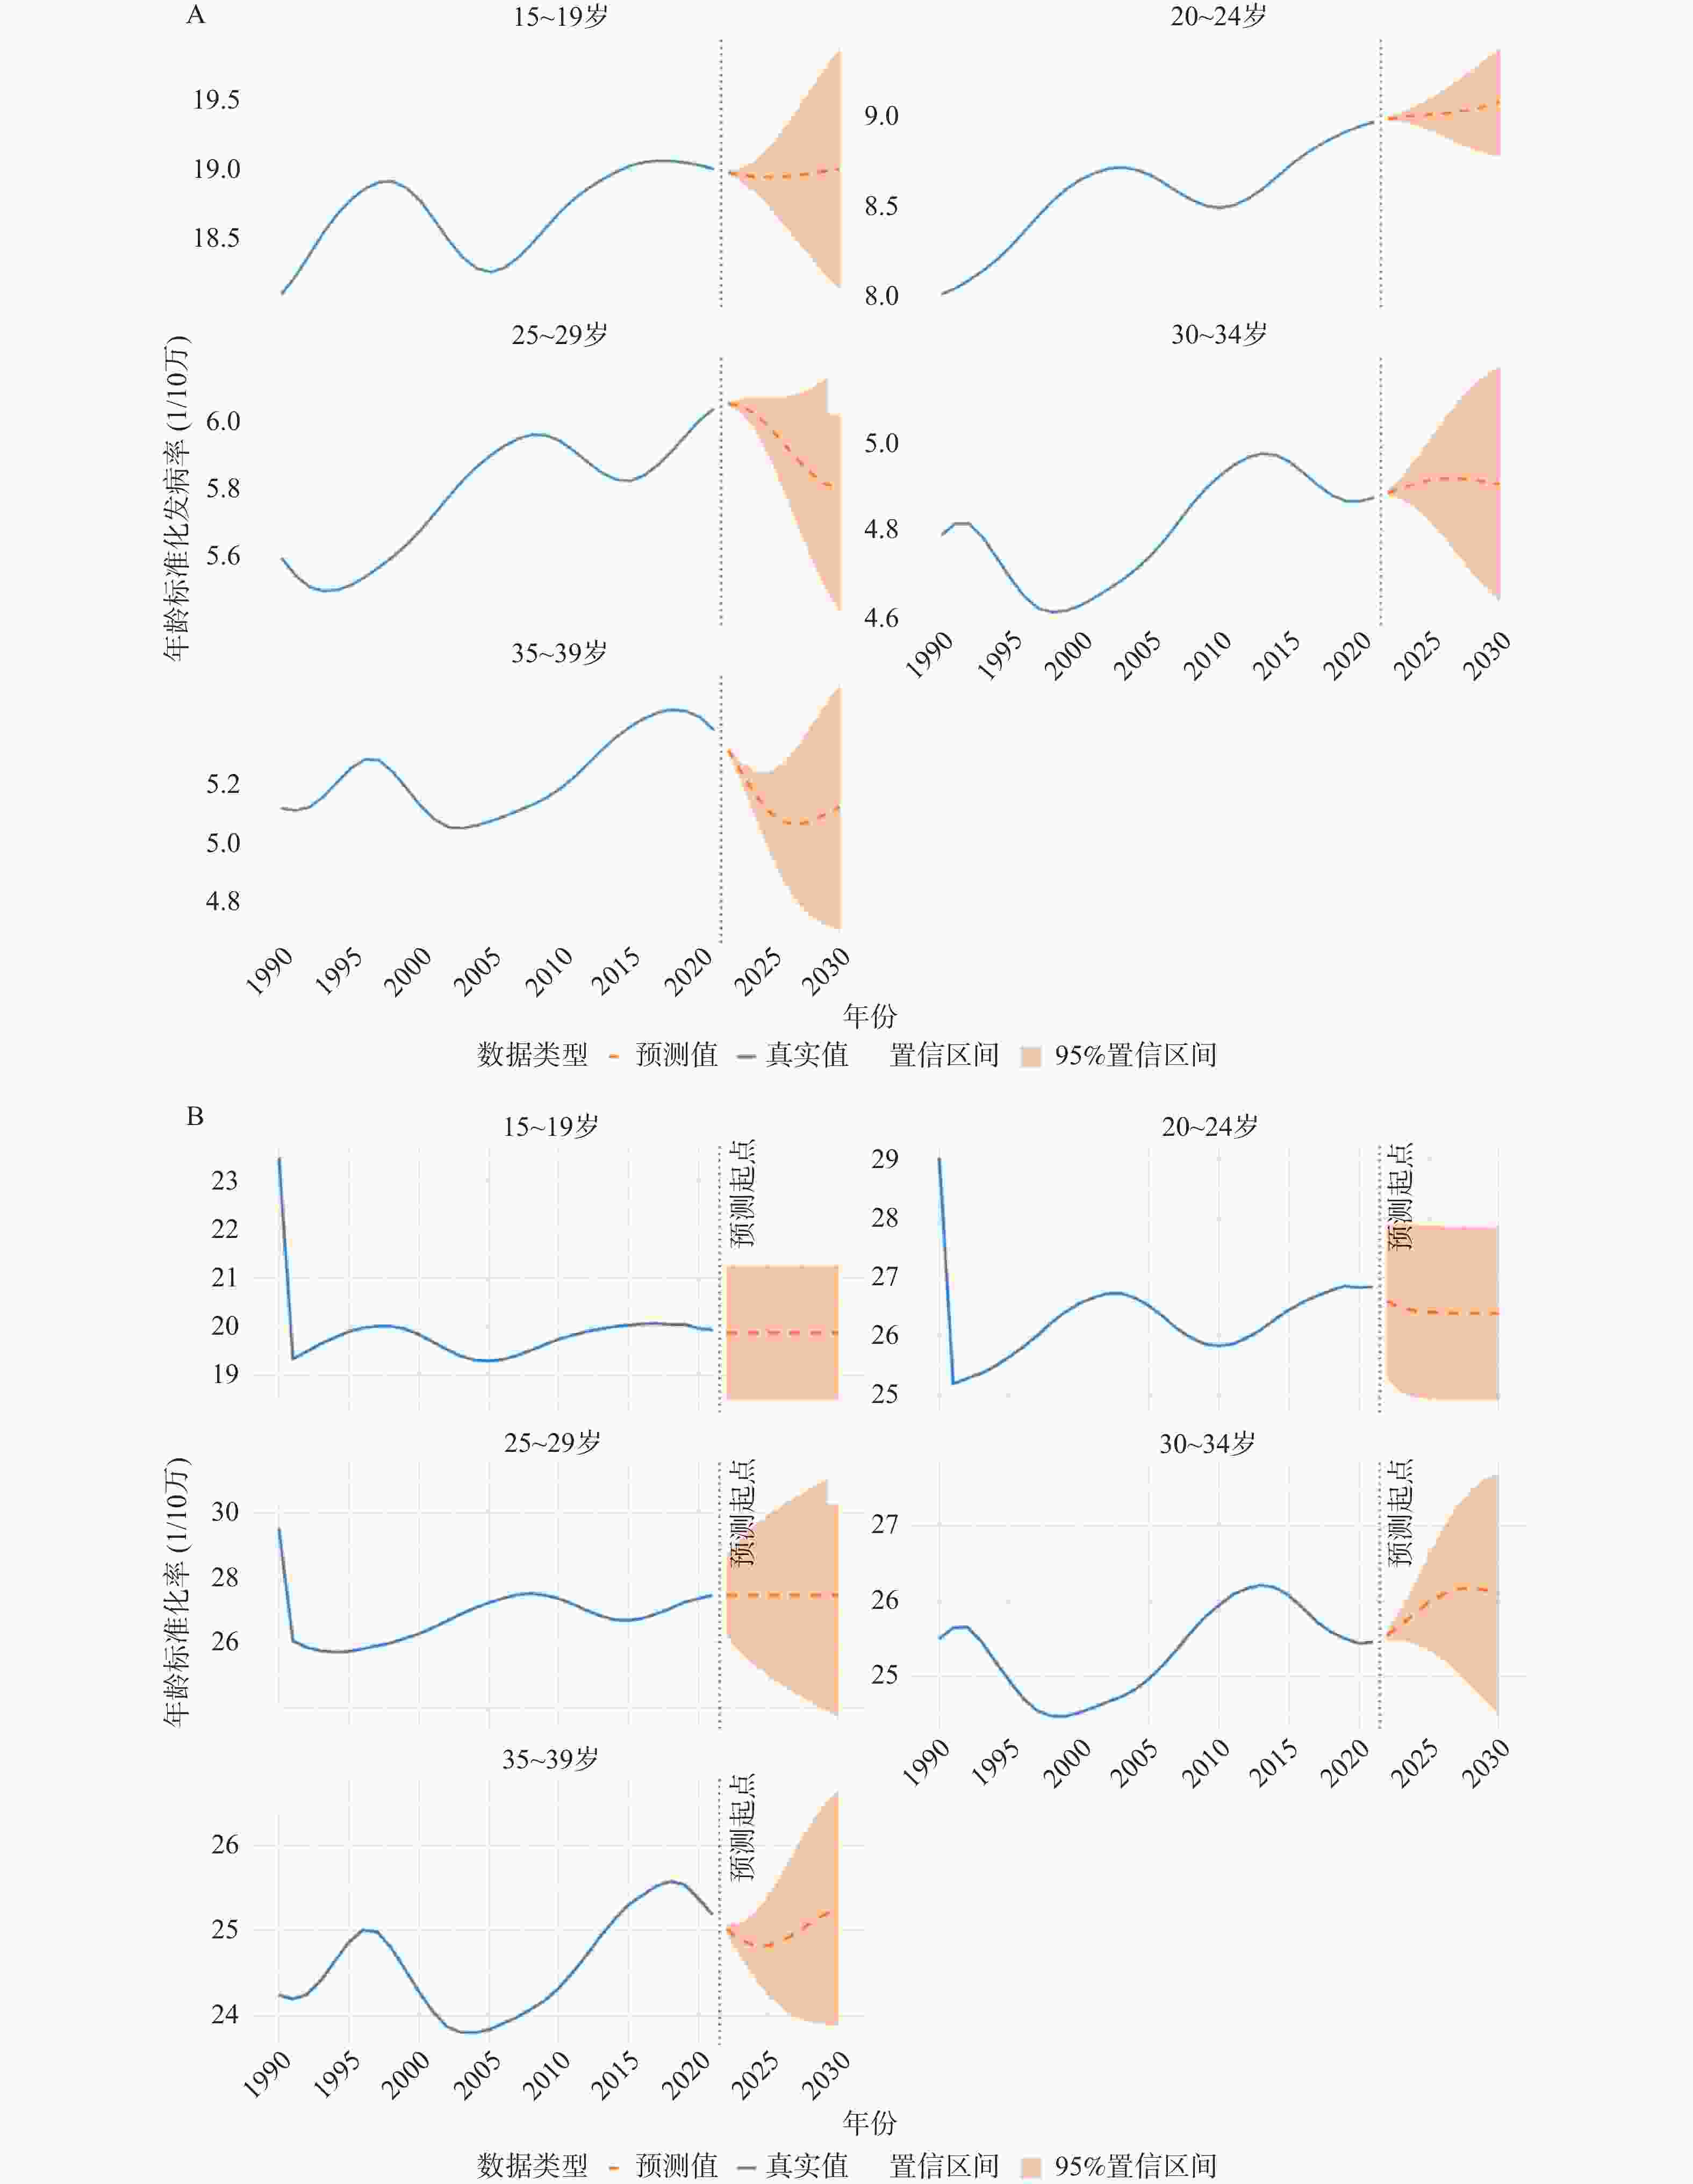
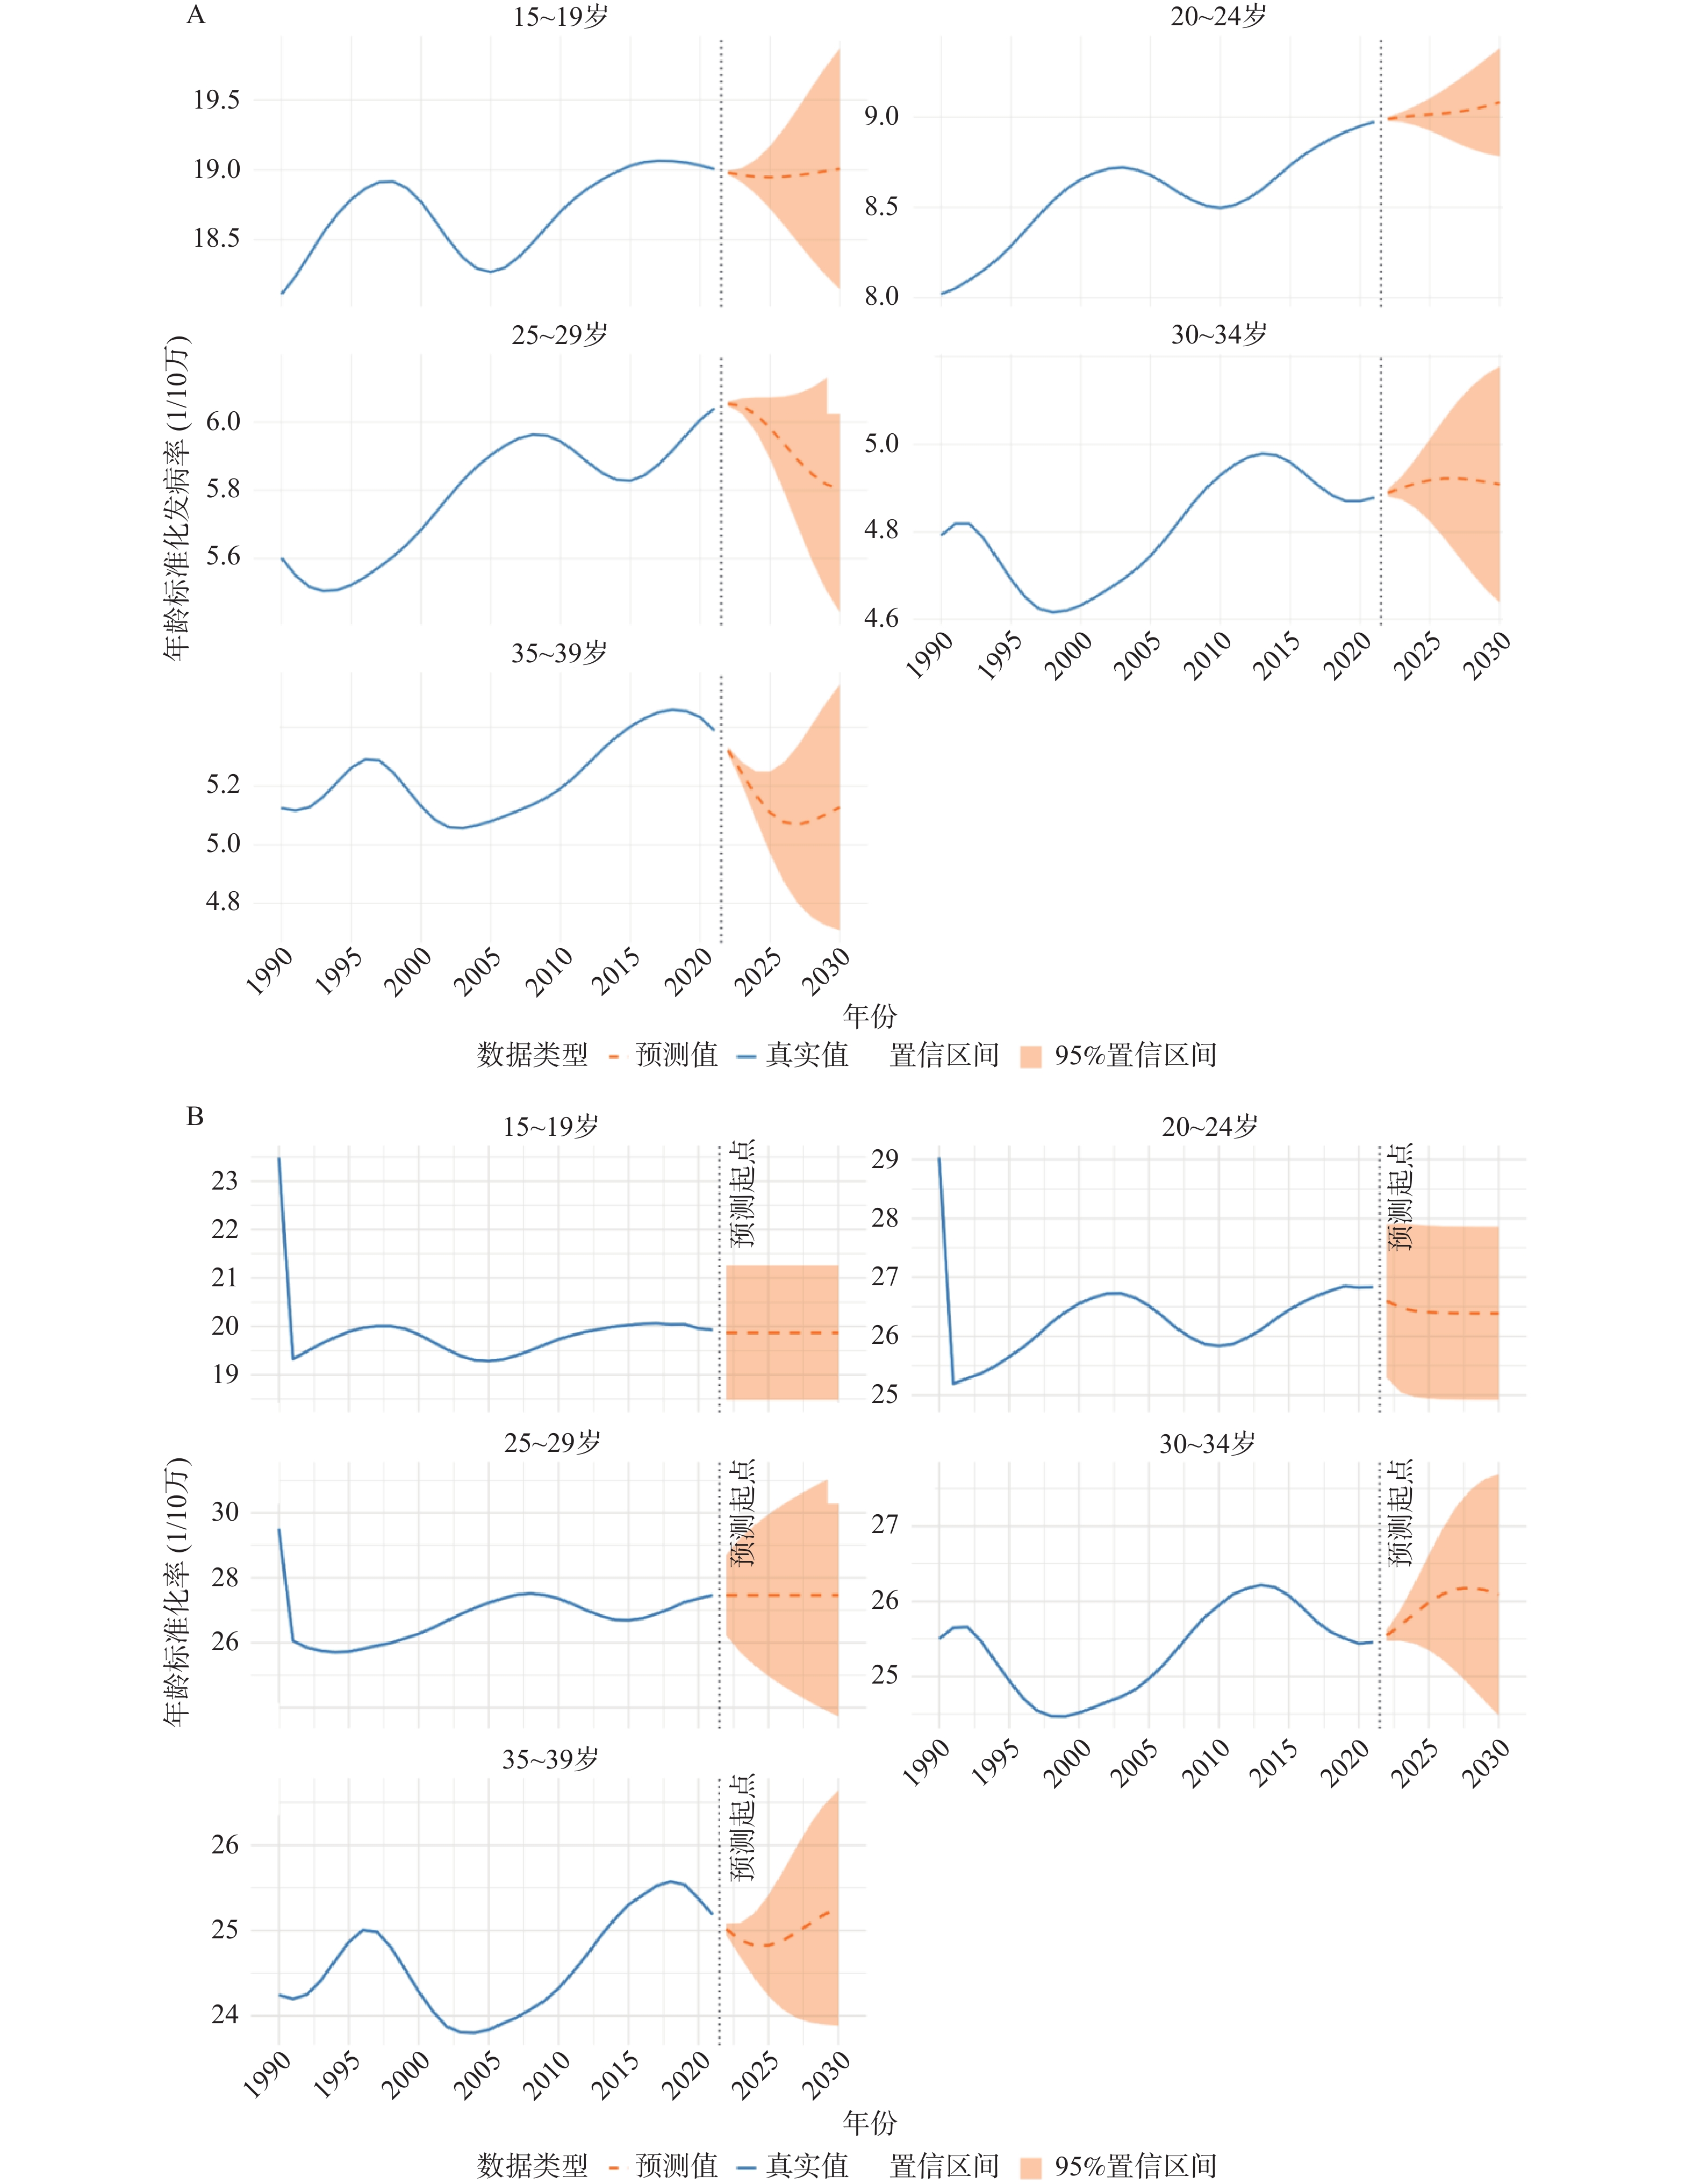
图 6 各年龄组标准化率预测情况
A:年龄标准化发病率(ASIR);B:年龄标准化伤残调整寿命年率(ASDR)。
Figure 6. Predicted trends in age-standardized rates of bipolar disorder by age
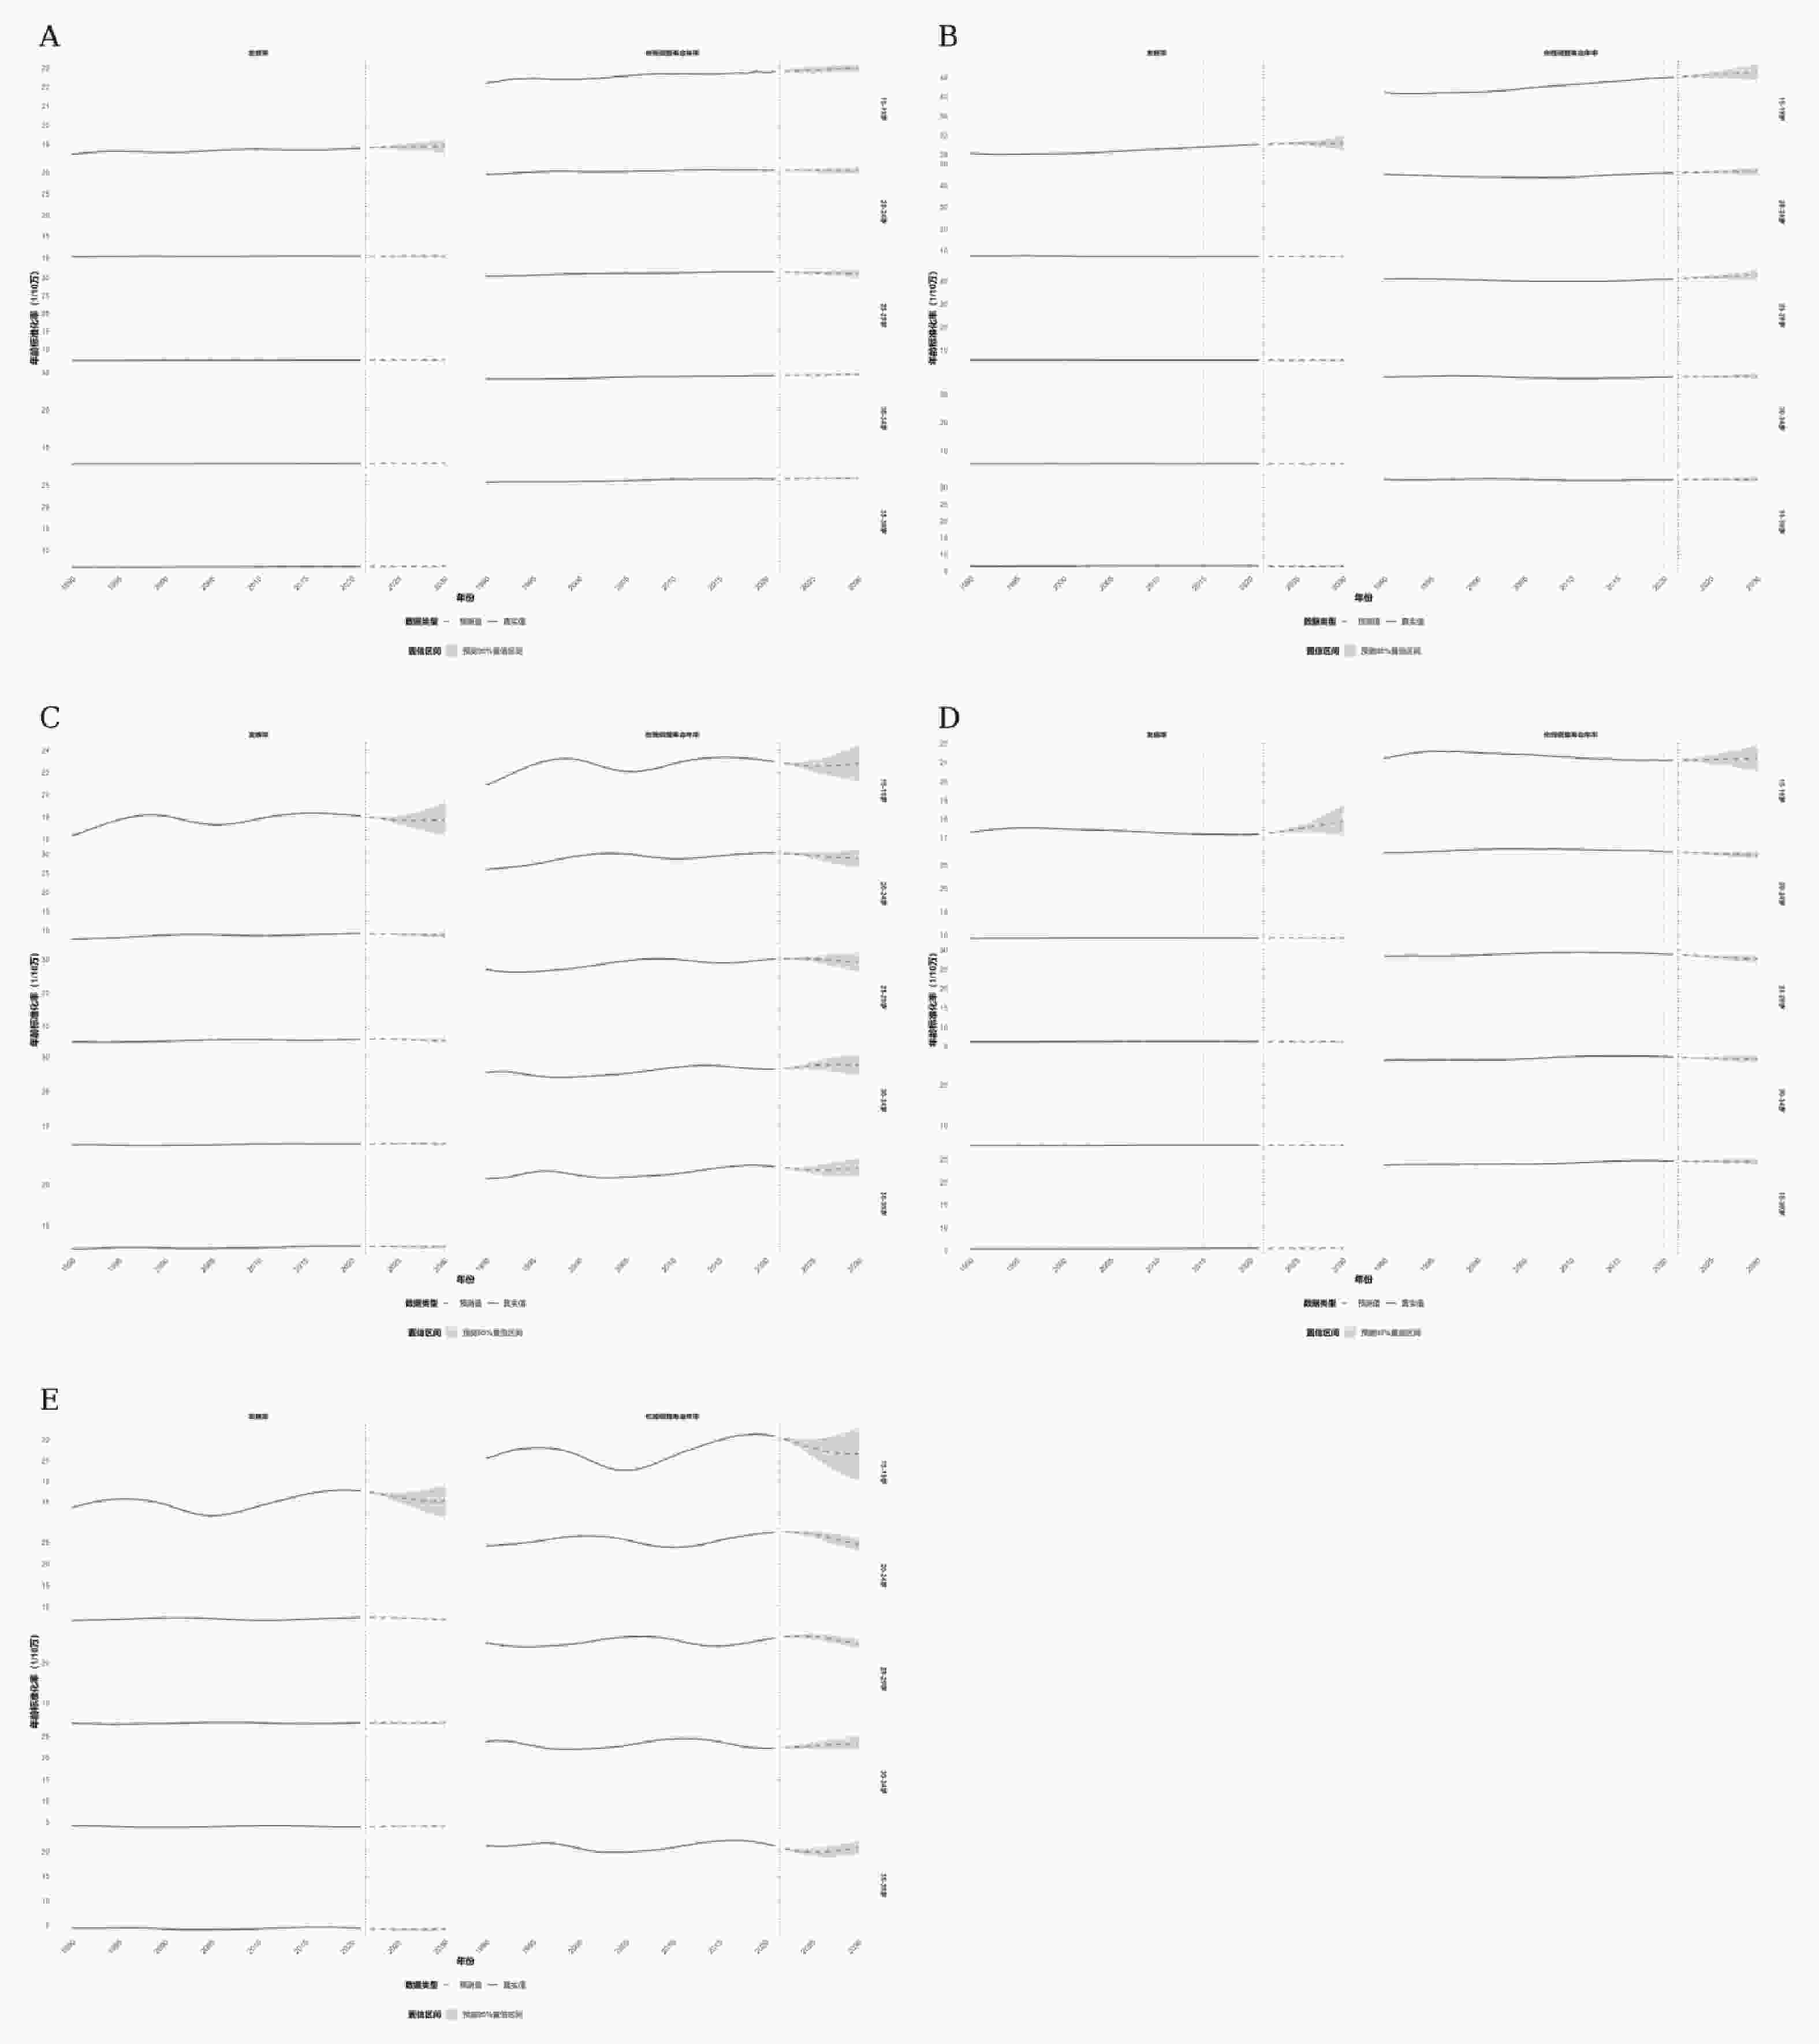
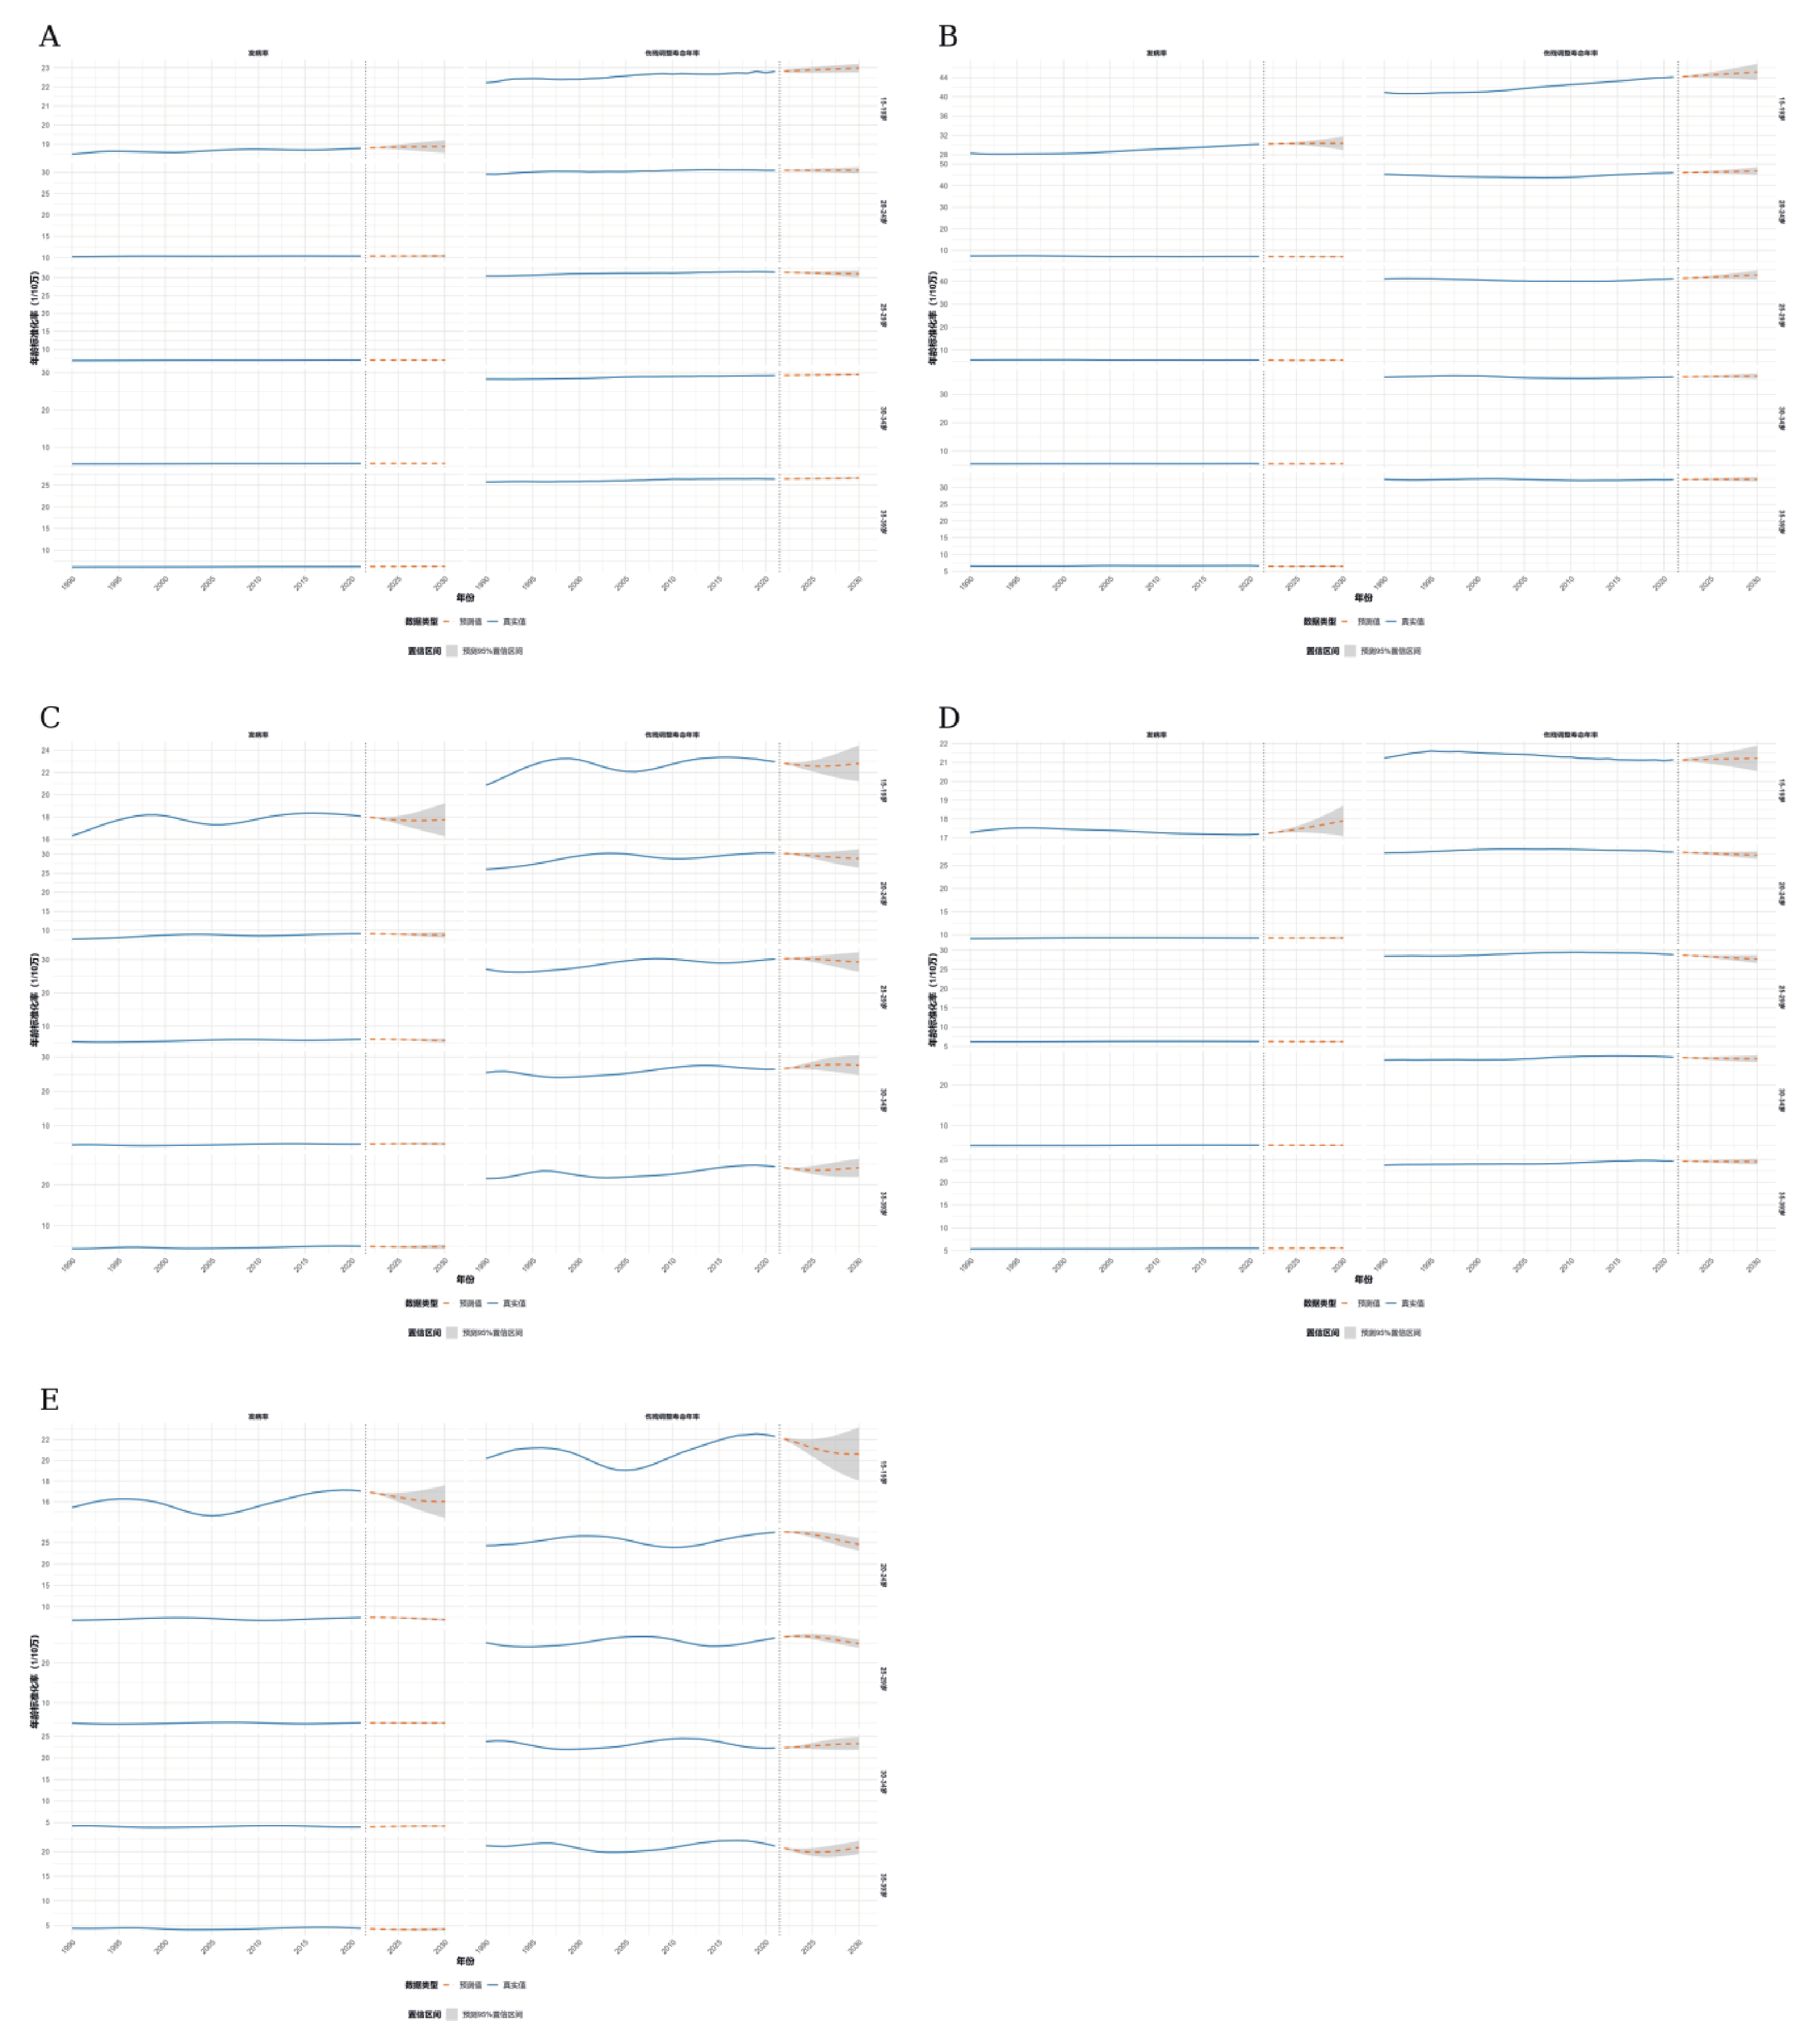
图 7 不同SDI水平预测情况
A:高SDI;B:中高SDI;C:中SDI;D:中低SDI;E:低SDI。
Figure 7. Predicted trends across different SDI level
表 1 1990年与2021年全球双相障碍发病率与伤残调整寿命年及其变化趋势
Table 1. Global trends in incidence and disability-adjusted life years of bipolar disorder,1990—2021
地区/SDI水平 发病情况 DALYs 1990年
病例数(数量×105)1990年
标准化率(1/10万)2021年
病例数(数量×105)2021年
标准化率(1/10万)年估计
变化百分比(EAPC,95%CI)1990年
病例数(数量×105)1990年
标准化率(1/10万)2021年
病例数(数量×105)2021年
标准化率(1/10万)年估计
变化百分比(EAPC,95%CI)全球 9.39(7.18~12.04) 41.64(32.71~50.57) 12.97(9.86~16.70) 44.28(35.74~55.93) 0.18(0.15~0.2) 29.2(19.04~43.7) 133.72(107.12~160.33) 41.32(26.6~61.83) 138.72(110.97~166.46) 0.13(0.12~0.15) 社会人口指数(SDI) 高 SDI 1.75(1.42~2.15) 53.56(43.92~63.2) 1.77(1.44~2.16) 55.18(45.72~64.63) 0.11(0.09~0.12) 6.78(4.45~9.96) 195.65(159.01~232.28) 6.99(4.58~10.13) 199.53(161.93~237.14) 0.05(0.02~0.08) 中高 SDI 1.61(1.22~2.08) 35.85(27.76~43.93) 1.51(1.12~1.96) 37.91(29.09~46.73) 0.14(0.06~0.22) 5.19(3.36~7.81) 114.51(90.98~138.03) 5.26(3.37~7.81) 119.38(94.33~144.44) 0.13(0.09~0.17) 中 SDI 3.01(2.29~3.85) 38.14(29.89~46.39) 3.83(2.94~4.9) 42.85(33.48~52.22) 0.33(0.29~0.37) 9.03(5.92~13.57) 120.86(96.66~145.07) 12.5(8.19~18.79) 134.24(107.25~161.23) 0.35(0.33~0.37) 中低 SDI 2.07(1.54~2.71) 43.04(33.33~52.75) 3.54(2.64~4.63) 43.42(33.61~53.24) 0.02(0.01~0.03) 5.7(3.64~8.58) 127.35(101.25~153.45) 10.35(6.62~15.62) 129.42(102.49~156.35) 0.08(0.06~0.09) 低 SDI 0.93(0.68~1.25) 47.22(35.97~58.47) 2.31(1.69~3.1) 48.02(36.54~59.49) 0.05(0.04~0.05) 2.46(1.53~3.74) 136.23(106.75~165.71) 6.19(3.79~9.46) 140.51(110.27~170.76) 0.11(0.1~0.12) 注:病例数及DALYs数单位为×105,ASIR及ASDR单位为1/10万;UI为不确定性区间,CI为置信区间;EAPC括号内为95%CI,其余指标括号内为95%UI。  下载: 导出CSV
表 2 1990年与2021年不同性别、年龄全球双相障碍发病率与伤残调整寿命年及其变化趋势
Table 2. Global trends in incidence and disability-adjusted life years of bipolar disorder,1990—2021
性别/
年龄组发病情况 DALYs 1990年
病例数
(数量×105)1990年
标准化率(1/10万)2021年
病例数
(数量×105)2021年
标准化率(1/10万)年估计变化
百分比(EAPC,95%CI)1990年
病例数
(数量×105)1990年
标准化率
(1/10万)2021年
病例数
(数量×105)2021年
标准化率
(1/10万)年估计变化
百分比(EAPC,
95%CI)性别 男 4.51(3.45~5.78) 39.45(34.44~53.34) 6.38(4.86~8.22) 42.79(33.39~52.19) 0.24(0.22~0.27) 14.10(9.18~21.12) 127.61(102.26~152.95) 20.3(13.03~30.45) 134.40(107.40~161.40) 0.16(0.09~0.23) 女 4.88(3.73~6.26) 43.89(34.53~54.04) 6.59(5.01~8.48) 45.83(30.99~47.91) 0.11(0.09~0.14) 15.10(9.85~22.55) 139.99(112.15~167.82) 20.30(13.03~30.45) 143.16(114.49~171.84) 0.07(0~0.13) 年龄组 15~19岁 4.29(3.15~5.76) 14.82(10.31~19.32) 5.41(3.93~7.34) 15.55(10.65~20.45) 0.10(0.05~0.15) 5.56(3.37~8.73) 23.48(12.16~34.81) 6.93(4.17~10.9) 19.93(10.26~29.60) ~0.04(~0.17~0.09) 20~24岁 1.9(0.91~3.27) 6.94(2.64~11.24) 2.59(1.23~4.43) 7.77(2.96~12.58) 0.27(0.21~0.34) 6.89(4.33~10.55) 29.03(15.95~42.11) 8.93(5.61~13.58) 26.84(14.87~33.8) 0.06(~0.04~0.16) 25~29岁 1.23(0.65~1.98) 5(2.31~7.69) 1.77(0.94~2.85) 5.39(2.47~8.30) 0.28(0.22~0.34) 6.50(4.13~9.78) 29.51(16.68~42.35) 9.01(5.65~13.57) 27.46(15.39~39.54) 0.12(0.02~0.23) 30~34岁 0.96(0.51~1.62) 4.45(1.89~7.02) 1.53(0.81~2.61) 4.53(1.86~7.20) 0.18(0.11~0.25) 5.48(3.51~8.18) 25.50(14.63~36.38) 8.58(5.41~12.82) 25.45(14.46~36.45) 0.12(0.05~0.20) 35~39岁 1.01(0.49~1.61) 5.12(2.28~7.97) 1.68(0.82~2.73) 5.39(2.33~8.45) 0.18(0.10~0.26) 4.76(3.01~7.07) 24.25(13.90~34.59) 7.87(5.01~11.73) 25.19(14.43~35.94) 0.13(0.05~0.21) 注:病例数及DALYs数单位为×105,ASIR及ASDR单位为1/10万;UI为不确定性区间,CI为置信区间;EAPC括号内为95%CI,其余指标括号内为95%UI。
下载: 导出CSV
-
[1] GBD 2019 Mental Disorders Collaborators. Global, regional, and national burden of 12 mental disorders in 204 countries and territories, 1990-2019: A systematic analysis for the Global Burden of Disease Study 2019[J]. Lancet Psychiatry, 2022, 9(2): 137-150. doi: 10.1016/S2215-0366(21)00395-3 [2] Malhi G S, Jadidi M, Bell E. The diagnosis of bipolar disorder in children and adolescents: Past, present and future[J]. Bipolar Disord, 2023, 25(6): 469-477. doi: 10.1111/bdi.13367 [3] Wozniak J, O’Connor H, Iorini M, et al. Pediatric bipolar disorder: Challenges in diagnosis and treatment[J]. Pediatr Drugs, 2025, 27(2): 125-142. doi: 10.1007/s40272-024-00669-z [4] Singh B, Swartz H A, Cuellar-Barboza A B, et al. Bipolar disorder[J]. Lancet, 2025, 406(10506): 963-978. doi: 10.1016/S0140-6736(25)01140-7 [5] Zhong Y, Chen Y, Su X, et al. Global, regional and national burdens of bipolar disorders in adolescents and young adults: A trend analysis from 1990 to 2019[J]. Gen Psychiatr, 2024, 37(1): e101255. doi: 10.1136/gpsych-2023-101255 [6] Culpepper L, Martin A, Harrington A, et al. A retrospective cross-sectional analysis of the humanistic and economic burden of bipolar I disorder[J]. Clin Ther, 2024, 46(11): 855-864. doi: 10.1016/j.clinthera.2024.08.003 [7] Solmi M, Radua J, Olivola M, et al. Age at onset of mental disorders worldwide: Large-scale meta-analysis of 192 epidemiological studies[J]. Mol Psychiatry, 2022, 27(1): 281-295. doi: 10.1038/s41380-021-01161-7 [8] Jiang J, Chen Y, Lin Z, et al. Global, regional, and national burden of bipolar disorder, 1990–2021: Analysis of data from the global burden of disease study 2021[J]. J Affect Disord, 2025, 389: 119638. doi: 10.1016/j.jad.2025.119638 [9] Buckley V, Young A H, Smith P. Child and adolescent anxiety as a risk factor for bipolar disorder: A systematic review of longitudinal studies[J]. Bipolar Disord, 2023, 25(4): 278-288. doi: 10.1111/bdi.13322 [10] Scott J, Graham A, Yung A, et al. A systematic review and meta-analysis of delayed help-seeking, delayed diagnosis and duration of untreated illness in bipolar disorders[J]. Acta Psychiatr Scand, 2022, 146(5): 389-405. doi: 10.1111/acps.13490 [11] Desai Boström A E, Andersson P, Rask-Andersen M, et al. Regional clozapine, ECT and lithium usage inversely associated with excess suicide rates in male adolescents[J]. Nat Commun, 2023, 14(1): 1281. doi: 10.1038/s41467-023-36973-4 [12] Fahrendorff A M, Pagsberg A K, Kessing L V, et al. Psychiatric comorbidity in patients with pediatric bipolar disorder - A systematic review[J]. Acta Psychiatr Scand, 2023, 148(2): 110-132. doi: 10.1111/acps.13548 [13] Andersson P, Jokinen J, Jarbin H, et al. Association of bipolar disorder diagnosis with suicide mortality rates in adolescents in Sweden[J]. JAMA Psychiatry, 2023, 80(8): 796-802. doi: 10.1001/jamapsychiatry.2023.1390 [14] GBD 2021 Diseases and Injuries Collaborators. Global incidence, prevalence, years lived with disability (YLDs), disability-adjusted life-years (DALYs), and healthy life expectancy (HALE) for 371 diseases and injuries in 204 countries and territories and 811 subnational locations, 1990–2021: A systematic analysis for the Global Burden of Disease Study 2021[J]. Lancet, 2024, 403(10440): 2133-2161. doi: 10.1016/S0140-6736(24)00757-8 [15] Anderson T L, Valiauga R, Tallo C, et al. Contributing factors to the rise in adolescent anxiety and associated mental health disorders: A narrative review of current literature[J]. Child Adoles Psych Nursing, 2025, 38: e70009. doi: 10.1111/jcap.70009 [16] Xiang A H, Martinez M P, Chow T, et al. Depression and anxiety among US children and young adults[J]. JAMA Netw Open, 2024, 7(10): e2436906. doi: 10.1001/jamanetworkopen.2024.36906 [17] Tang A, Chen Y, Ding J, et al. Gut microbiota remodeling and sensory-emotional functional disruption in adolescents with bipolar depression[J]. J Transl Med, 2025, 23(1): 1083. doi: 10.1186/s12967-025-07152-4 [18] Andreu-Pascual M, Merranko J, Gill M K, et al. Risk factors preceding new onset abuse among youth with bipolar disorder: A longitudinal prospective analysis[J]. J Affect Disord, 2022, 300: 296-304. doi: 10.1016/j.jad.2022.01.003 [19] Diler R S, Merranko J A, Hafeman D, et al. Higher socioeconomic status and less parental psychopathology improve prognosis in youths with bipolar disorder[J]. J Affect Disord, 2022, 302: 185-193. doi: 10.1016/j.jad.2022.01.058 [20] Stepan M E, Franzen P L, Teresi G I, et al. Sleep quality predicts future mood symptoms in adolescents with bipolar disorder[J]. J Affect Disord, 2024, 361: 664-673. doi: 10.1016/j.jad.2024.06.069 [21] Nierenberg A A, Agustini B, Köhler-Forsberg O, et al. Diagnosis and treatment of bipolar disorder: A review[J]. JAMA, 2023, 330(14): 1370-1380. doi: 10.1001/jama.2023.18588 [22] Freeman M. The World Mental Health Report: Transforming mental health for all[J]. World Psychiatry, 2022, 21(3): 391-392. doi: 10.1002/wps.21018 [23] Fonseca L, Sena B F, Crossley N, et al. Diversity matters: Opportunities in the study of the genetics of psychotic disorders in low- and middle-income countries in Latin America[J]. Braz J Psychiatry, 2021, 43(6): 631-637. doi: 10.1590/1516-4446-2020-1240 -

 点击查看大图
计量
- 文章访问数: 122
- HTML全文浏览量: 83
- PDF下载量: 1
- 被引次数: 0
