




Dynamic Changes and Prognostic Significance of Serum Soluble TIM-3 and IFN-γ/IL-10 after Radiofrequency Ablation of Solitary Liver Metastases in Colorectal Cancer
-
摘要:
目的 探讨结直肠癌孤立性肝转移灶射频消融术后血清可溶性T细胞免疫球蛋白和黏蛋白结构域蛋白3(soluble T cell immunoglobulin and mucin domain containing 3,sTIM-3)及干扰素γ/白细胞介素10比值(interferon-γ/interleukin-10,IFN-γ/IL-10)的动态变化特征及其预后意义。 方法 前瞻性纳入2021年12月至2023年12月接受根治性意图射频消融的孤立性结直肠癌肝转移患者137例,设置术前24 h、术后24 h、7 d、1个月、3个月、6个月、12个月及24个月多时间点检测sTIM-3、IFN-γ、IL-10并计算IFN-γ/IL-10比值,随访截止至2025年12月31日。以复发为主要结局,采用线性混合效应模型评估动态变化,Logistic回归与Cox比例风险模型评估复发与无复发生存(recurrence-free survival,RFS)的相关因素。 结果 随访中位时间22.40个月,复发46例(33.58%),死亡12例(8.76%),2年RFS为66.90%。基线复发组较未复发组肝转移灶最大径更大(31.37±9.08 mm vs 25.55±7.79 mm,t = 3.720,P < 0.001),消融边界<5 mm比例更高(43.48% vs 20.88%,χ2 = 7.640,P = 0.006),CEA升高比例更高(45.65% vs 21.98%,χ2 = 8.190,P = 0.004),sTIM-3更高(478.42±132.69 pg/mL vs 378.88±110.57 pg/mL,t = 4.610,P < 0.001),IFN-γ/IL-10比值更低(1.81±0.92 vs 2.71±1.04,t = 5.210,P < 0.001)。动态分析显示,sTIM-3在术后早期波动后于术后1个月起复发组持续升高而未复发组逐渐下降,时间与复发结局交互作用显著(F = 5.240,P = 0.002);术后1个月复发组IFN-γ/IL-10比值明显低于未复发组(1.70±0.80 vs 2.80±1.00,t = 6.020,P < 0.001)。多因素Logistic回归显示,肝转移灶最大径增加(OR = 1.06,95%CI:1.02~1.11,P = 0.003)、消融边界<5 mm(OR = 2.21,95%CI:1.06~4.60,P = 0.036)、CEA升高(OR = 1.98,95%CI:1.00~3.92,P = 0.048)、sTIM-3升高(OR = 1.04,95%CI:1.01~1.08,P = 0.009)及IFN-γ/IL-10比值降低(OR = 0.54,95%CI:0.34~0.85,P = 0.008)为复发的独立相关因素。多因素Cox分析显示,sTIM-3升高(HR = 1.04,95%CI:1.01~1.07,P = 0.003)和IFN-γ/IL-10比值升高(HR = 0.55,95%CI:0.36~0.84,P = 0.007)仍与RFS独立相关。术后1个月动态指标分析进一步显示,sTIM-3升高及IFN-γ/IL-10比值降低与较差RFS相关。 结论 射频消融术后sTIM-3持续升高与IFN-γ/IL-10比值降低提示免疫抑制或耗竭优势状态,与结直肠癌孤立性肝转移术后复发风险升高及RFS不良独立相关;联合肿瘤负荷与消融边界等临床因素的多时间点免疫监测可用于术后风险分层与随访管理。 -
关键词:
- 结直肠癌肝转移 /
- 射频消融 /
- 可溶性TIM-3 /
- IFN-γ/IL-10比值 /
- 无复发生存
Abstract:Objective To investigate the dynamic changes and prognostic significance of serum soluble T cell immunoglobulin and mucin domain containing 3 (sTIM-3) and the interferon-γ/interleukin-10 ratio (IFN-γ/IL-10) after radiofrequency ablation (RFA) of solitary liver metastases from colorectal cancer. Methods A total of 137 patients with solitary colorectal cancer liver metastases who underwent RFA with curative intent between December 2021 and December 2023 were prospectively enrolled. sTIM-3, IFN-γ, and IL-10 were measured at multiple time points—24 hours before ablation and 24 hours, 7 days, 1 month, 3 months, 6 months, 12 months, and 24 months after ablation—and the IFN-γ/IL-10 ratio was calculated. Follow-up continued until December 31, 2025. With recurrence as the primary outcome, linear mixed-effects models were used to assess dynamic changes, while logistic regression and Cox proportional hazards models were used to identify factors associated with recurrence and recurrence-free survival (RFS). Results With a median follow-up of 22.40 months, recurrence occurred in 46 patients (33.58%) and death in 12 (8.76%); the 2-year RFS rate was 66.90%. At baseline, the recurrence group had a larger maximum diameter of liver metastases than the non-recurrence group (31.37±9.08 mm vs 25.55±7.79 mm, t = 3.720, P < 0.001), a higher proportion of ablation margins <5 mm (43.48% vs 20.88%, χ2 = 7.640, P = 0.006), a higher proportion of elevated CEA (45.65% vs 21.98%, χ2 = 8.190, P = 0.004), higher sTIM-3 levels (478.42±132.69 pg/mL vs 378.88±110.57 pg/mL, t = 4.610, P < 0.001), and a lower IFN-γ/IL-10 ratio (1.81±0.92 vs 2.71±1.04, t = 5.210, P < 0.001). Dynamic analysis showed that after early postoperative fluctuation, sTIM-3 continuously increased from 1 month postoperatively in the recurrence group but gradually declined in the non-recurrence group, with a significant time-by-recurrence-outcome interaction (F = 5.240, P = 0.002). At 1 month postoperatively, the IFN-γ/IL-10 ratio was significantly lower in the recurrence group than in the non-recurrence group (1.70±0.80 vs 2.80±1.00, t = 6.020, P < 0.001). Multivariate logistic regression showed that an increased maximum diameter of liver metastases (OR = 1.06, 95%CI: 1.02~1.11, P = 0.003), ablation margin <5 mm (OR = 2.21, 95%CI: 1.06~4.60, P = 0.036), elevated CEA (OR = 1.98, 95%CI: 1.00~3.92, P = 0.048), elevated sTIM-3 (OR = 1.04, 95%CI: 1.01~1.08, P = 0.009), and a decreased IFN-γ/IL-10 ratio (OR = 0.54, 95%CI: 0.34~0.85, P = 0.008) were independently associated with recurrence. Multivariate Cox analysis showed that elevated sTIM-3 (HR = 1.04, 95%CI: 1.01~1.07, P = 0.003) and an elevated IFN-γ/IL-10 ratio (HR = 0.55, 95%CI: 0.36~0.84, P = 0.007) remained independently associated with RFS. Further analysis of dynamic markers at 1 month postoperatively demonstrated that elevated sTIM-3 and a decreased IFN-γ/IL-10 ratio were associated with poorer RFS. Conclusions Persistent elevation of sTIM-3 and a decreased IFN-γ/IL-10 ratio after radiofrequency ablation indicate an immunosuppressive or exhaustion-dominant state, which are independently associated with an increased risk of postoperative recurrence and poorer RFS in patients with solitary colorectal cancer liver metastases. Multipoint immune monitoring combined with clinical factors such as tumor burden and ablation margin may be used for postoperative risk stratification and follow-up management. -
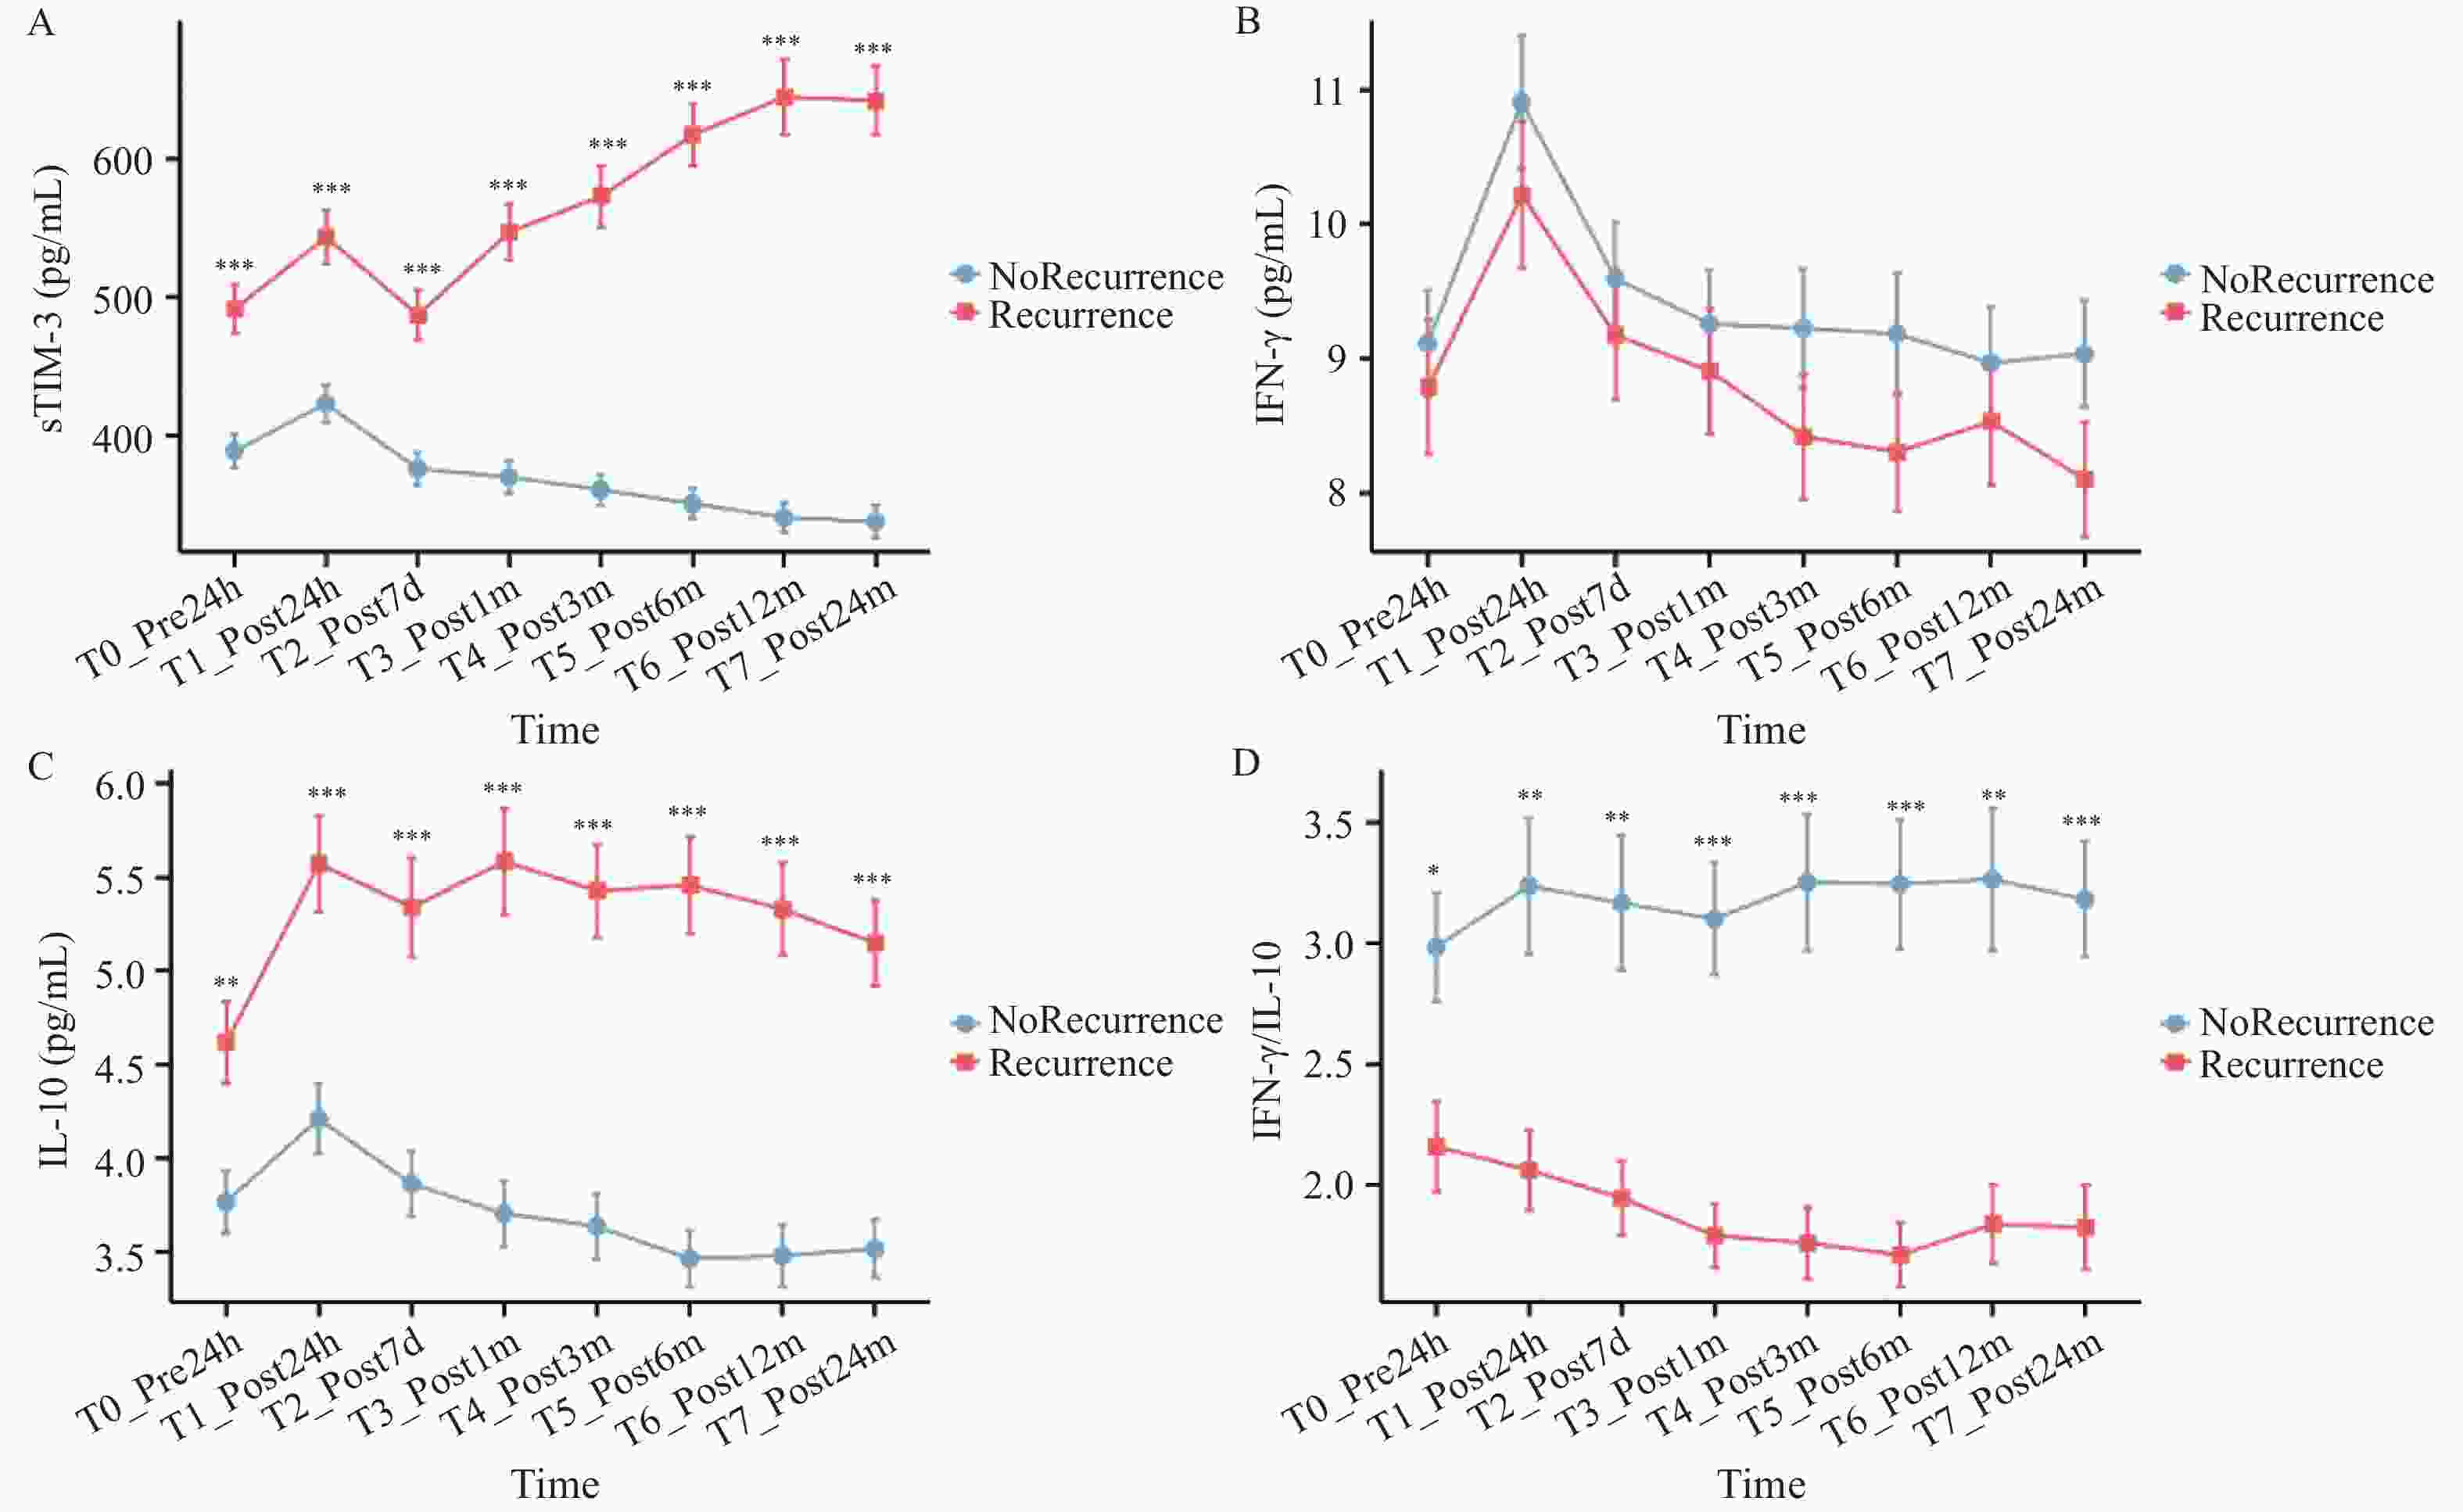
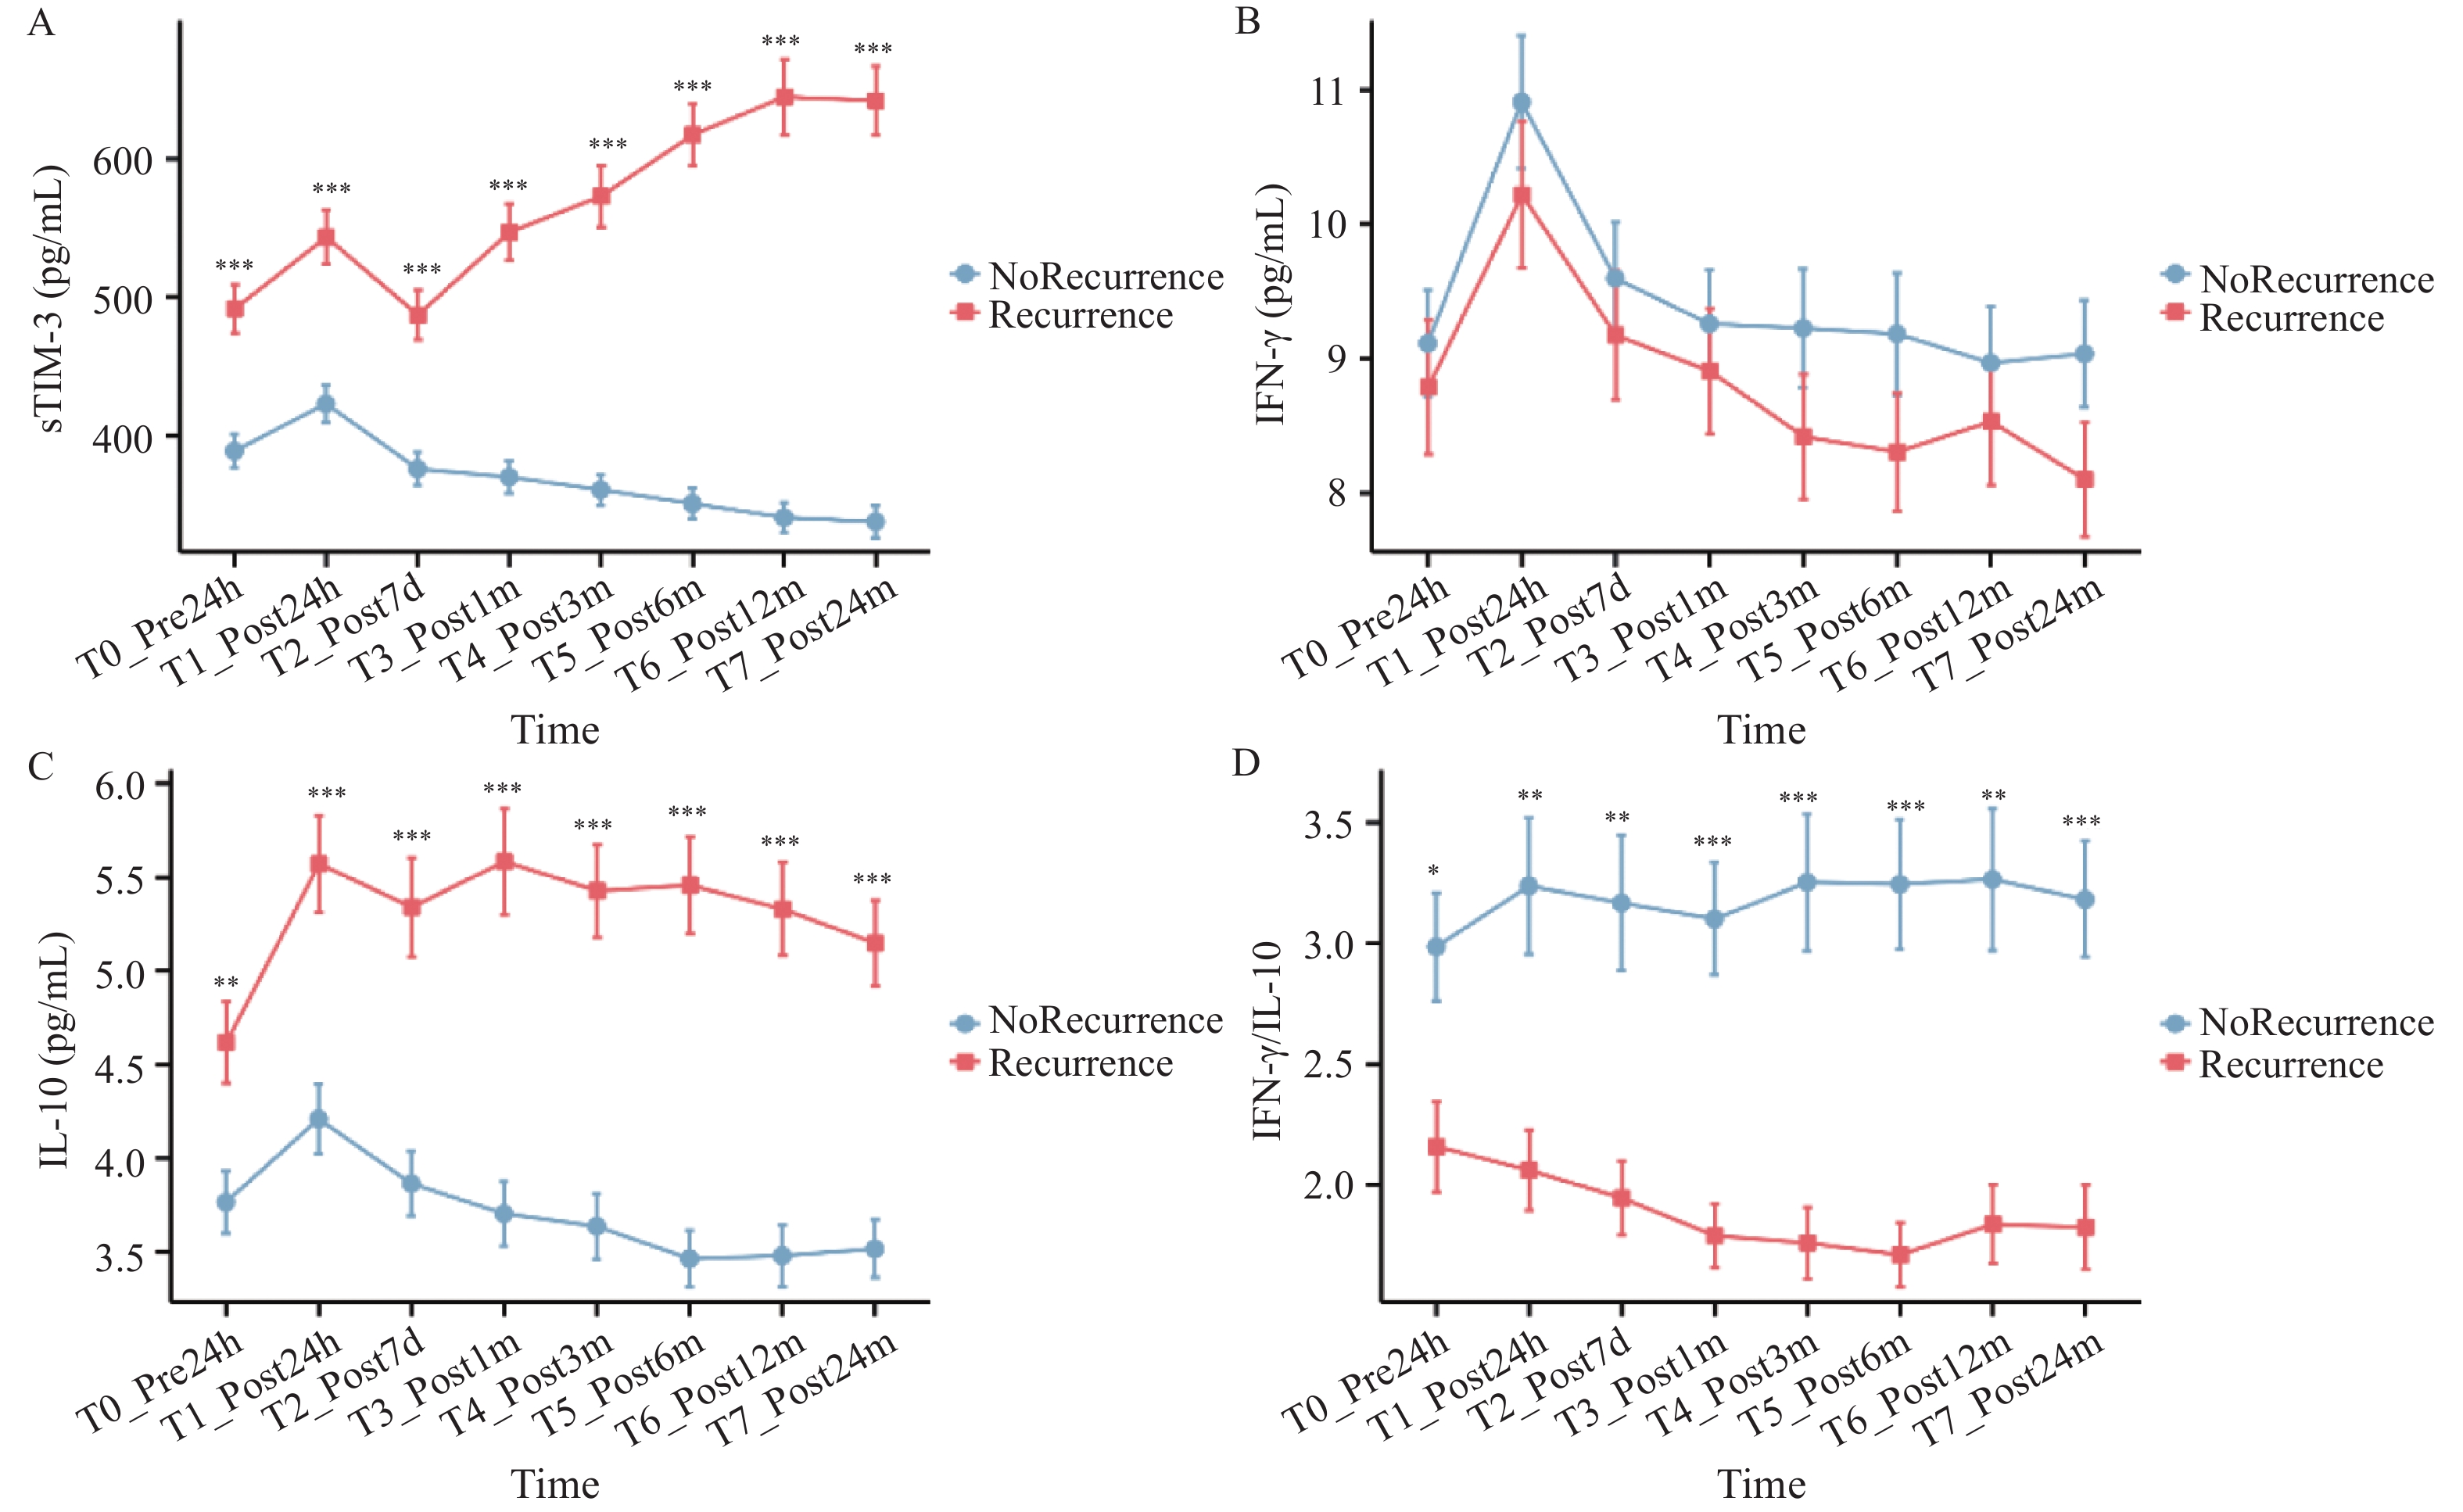
图 1 sTIM-3、IFN-γ、IL-10及IFN-γ/IL-10比值的动态变化
A:sTIM-3;B:IFN-γ;C:IL-10;D:IFN-γ/IL-10比值;误差线表示均数±标准误;各时间点组间事后比较采用线性混合效应模型估计边际均值,并经Benjamini-Hochberg法校正。*P < 0.05;**P < 0.01;***P < 0.001。
Figure 1. Dynamic changes in sTIM-3,IFN-γ,IL-10,and the IFN-γ/IL-10 ratio
表 1 基线人口学、肿瘤学与实验室特征[($\bar x \pm s $)/n(%)]
Table 1. Baseline demographic,oncologic,and laboratory characteristics [($\bar x \pm s $)/n(%)]
变量 总体(n= 137) 复发(n= 46) 未复发(n= 91) t/χ2 P 年龄(岁) 58.74 ± 10.58 60.41 ± 9.76 57.90 ± 10.93 1.360 0.176 男性 82(59.85) 29(63.04) 53(58.24) 0.280 0.597 BMI(kg/m2) 23.82 ± 3.11 23.53 ± 3.02 23.96 ± 3.15 0.738 0.462 原发部位结肠 87(63.50) 30(65.22) 57(62.64) 0.086 0.770 T3~4 105(76.64) 38(82.61) 67(73.63) 1.295 0.255 N2 39(28.47) 17(36.96) 22(24.18) 2.363 0.124 同步转移 48(35.04) 22(47.83) 26(28.57) 5.230 0.022* 肝转移灶最大径(mm) 27.48 ± 8.62 31.37 ± 9.08 25.55 ± 7.79 3.720 <0.001* 消融边界<5 mm 39(28.47) 20(43.48) 19(20.88) 7.640 0.006* 消融次数≥2 28(20.44) 12(26.09) 16(17.58) 1.370 0.242 基线CEA升高 41(29.93) 21(45.65) 20(21.98) 8.190 0.004* 基线CA19-9升高 36(26.28) 15(32.61) 21(23.08) 1.460 0.226 CRP(mg/L) 6.78 ± 3.18 8.42 ± 3.53 5.95 ± 2.77 4.130 <0.001* NLR 2.83 ± 1.12 3.23 ± 1.18 2.62 ± 1.03 3.040 0.003* PLR 148.32 ± 56.41 160.91 ± 60.20 141.96 ± 53.79 1.840 0.068 LMR 4.02 ± 1.39 3.71 ± 1.28 4.17 ± 1.43 1.820 0.071 sTIM-3(pg/mL) 412.31 ± 126.48 478.42 ± 132.69 378.88 ± 110.57 4.610 <0.001* IFN-γ(pg/mL) 8.94 ± 3.71 8.51 ± 3.66 9.16 ± 3.73 0.971 0.333 IL-10(pg/mL) 3.89 ± 1.55 4.45 ± 1.62 3.61 ± 1.44 3.010 0.003* IFN-γ/IL-10 2.41 ± 1.10 1.81 ± 0.92 2.71 ± 1.04 5.210 <0.001* *P < 0.05。BMI:体质指数;CEA:癌胚抗原;CA19-9:糖类抗原19-9;CRP:C反应蛋白;NLR:中性粒细胞/淋巴细胞比值;PLR:血小板/淋巴细胞比值;LMR:淋巴细胞/单核细胞比值;sTIM-3:可溶性T细胞免疫球蛋白和黏蛋白结构域蛋白3。  下载: 导出CSV
表 2 复发影响因素的单因素Logistic回归分析[OR(95%CI)]
Table 2. Univariate logistic regression analysis of factors influencing recurrence [OR (95%CI)]
变量 β SE OR 95%CI Wald P 年龄(每增加1岁) 0.02 0.02 1.02 0.99~1.06 1.100 0.294 男性 0.21 0.36 1.23 0.61~2.48 0.340 0.558 BMI(每增加1 kg/m2) −0.04 0.05 0.96 0.87~1.06 0.680 0.410 原发部位结肠 0.12 0.36 1.13 0.55~2.31 0.110 0.742 T3~4 0.47 0.41 1.60 0.72~3.57 1.320 0.251 N2 0.53 0.35 1.70 0.86~3.37 2.292 0.130 同步转移 0.89 0.38 2.44 1.16~5.12 5.480 0.019* 最大径(每增加1 mm) 0.08 0.02 1.08 1.04~1.12 15.630 <0.001* 消融边界<5 mm 1.01 0.39 2.75 1.28~5.90 6.640 0.010* 消融次数≥2 0.47 0.42 1.60 0.70~3.65 1.250 0.264 CEA升高 0.95 0.40 2.59 1.19~5.64 5.640 0.018* CA19-9升高 0.42 0.39 1.52 0.71~3.23 1.160 0.281 CRP(每升高1 mg/L) 0.19 0.06 1.21 1.08~1.36 9.740 0.002* NLR(每增加1) 0.42 0.16 1.52 1.12~2.06 6.890 0.009* PLR(每10单位) 0.03 0.02 1.03 0.99~1.06 2.190 0.139 LMR(每增加1) −0.18 0.12 0.84 0.67~1.05 2.250 0.134 sTIM-3(每10 pg/mL) 0.06 0.02 1.06 1.03~1.10 13.820 <0.001* IFN-γ(每1 pg/mL) −0.03 0.04 0.97 0.90~1.04 0.560 0.455 IL-10(每升高1 pg/mL) 0.36 0.12 1.43 1.13~1.81 9.210 0.002* IFN-γ/IL-10(每增加1) −0.74 0.21 0.48 0.32~0.71 12.470 <0.001* *P < 0.05。
下载: 导出CSV
表 3 复发影响因素的多因素Logistic回归分析
Table 3. Multivariable logistic regression analysis of factors influencing recurrence
变量 β SE OR 95%CI Wald P 最大径(每增加1 mm) 0.06 0.02 1.06 1.02~1.11 8.930 0.003* 消融边界<5 mm 0.79 0.38 2.21 1.06~4.60 4.380 0.036* CEA升高 0.68 0.35 1.98 1.00~3.92 3.900 0.048* sTIM-3(每升高10 pg/mL) 0.04 0.02 1.04 1.01~1.08 6.810 0.009* IFN-γ/IL-10(每增加1) −0.61 0.23 0.54 0.34~0.85 7.060 0.008* 同步转移 0.41 0.33 1.51 0.79~2.90 1.530 0.216 CRP(每升高1 mg/L) 0.06 0.05 1.06 0.96~1.16 1.510 0.219 NLR(每增加1) 0.18 0.14 1.20 0.91~1.58 1.650 0.199 IL-10(每升高1 pg/mL) 0.13 0.11 1.14 0.92~1.41 1.390 0.238 *P < 0.05。
下载: 导出CSV
表 4 RFS影响因素的单因素Cox比例风险回归分析
Table 4. Univariate Cox proportional hazards regression analysis of factors influencing with RFS
变量 β SE HR 95%CI Wald P 年龄(每增加1岁) 0.02 0.01 1.02 0.99~1.05 1.890 0.169 男性 0.18 0.31 1.20 0.65~2.20 0.340 0.559 BMI(每增加1 kg/m2) −0.03 0.04 0.97 0.89~1.06 0.520 0.471 原发部位结肠 0.09 0.31 1.09 0.59~2.00 0.090 0.770 T3~4 0.29 0.36 1.34 0.66~2.71 0.650 0.420 N2 0.41 0.31 1.51 0.83~2.75 1.760 0.184 同步转移 0.77 0.33 2.16 1.14~4.10 5.450 0.020* 最大径(每增加1 mm) 0.07 0.02 1.07 1.03~1.11 13.220 <0.001* 消融边界<5 mm 0.78 0.34 2.18 1.12~4.24 5.290 0.021* 消融次数≥2 0.28 0.33 1.32 0.69~2.52 0.720 0.396 CEA升高 0.80 0.34 2.23 1.14~4.35 5.540 0.019* CA19-9升高 0.26 0.31 1.30 0.71~2.38 0.700 0.403 CRP(每升高1 mg/L) 0.17 0.05 1.19 1.08~1.31 10.630 0.001* NLR(每增加1) 0.35 0.14 1.42 1.08~1.87 6.130 0.013* PLR(每增加10) 0.02 0.02 1.02 0.99~1.05 1.410 0.235 LMR(每增加1) −0.12 0.10 0.89 0.73~1.08 1.440 0.230 sTIM-3(每升高10 pg/mL) 0.05 0.01 1.05 1.03~1.08 14.180 <0.001* IFN-γ(每升高1 pg/mL) −0.02 0.03 0.98 0.92~1.05 0.340 0.561 IL-10(每升高1 pg/mL) 0.29 0.10 1.34 1.11~1.62 8.640 0.003* IFN-γ/IL-10(每增加1) −0.68 0.21 0.51 0.34~0.75 10.480 0.001* *P < 0.05。
下载: 导出CSV
表 5 RFS影响因素的多因素Cox比例风险回归分析
Table 5. Multivariable Cox proportional hazards regression analysis of factors influencing RFS
变量 β SE HR 95%CI Wald χ2 P 肝转移灶最大径(每增加1 mm) 0.05 0.02 1.05 1.01~1.09 7.880 0.005* 消融边界<5 mm 0.71 0.33 2.04 1.05~3.96 4.610 0.032* CEA升高 0.66 0.33 1.94 1.01~3.72 3.990 0.046* sTIM-3(每升高10 pg/mL) 0.04 0.01 1.04 1.01~1.07 8.740 0.003* IFN-γ/IL-10比值(每增加1) −0.59 0.22 0.55 0.36~0.84 7.180 0.007* *P < 0.05。
下载: 导出CSV
表 6 术后动态免疫指标与RFS关系的扩展Cox分析
Table 6. Extended Cox analysis of the association between postoperative dynamic immune indicators and RFS
动态免疫变量 调整因素 β SE HR 95%CI Wald χ2 P 术后1个月sTIM-3(每升高10 pg/mL) 最大径、消融边界<5 mm、CEA升高 0.04 0.02 1.04 1.01~1.08 6.82 0.009* 术后1个月ΔsTIM-3(每升高10 pg/mL) 最大径、消融边界<5 mm、CEA升高 0.05 0.02 1.05 1.02~1.09 8.28 0.004* 术后3个月sTIM-3(每升高10 pg/mL) 最大径、消融边界<5 mm、CEA升高 0.04 0.02 1.04 1.01~1.07 7.04 0.008* 术后3个月ΔsTIM-3(每升高10 pg/mL) 最大径、消融边界<5 mm、CEA升高 0.04 0.02 1.04 1.01~1.08 6.64 0.010* 术后1个月IFN-γ/IL-10(每1单位) 最大径、消融边界<5 mm、CEA升高 −0.65 0.23 0.52 0.33~0.83 7.55 0.006* 术后1个月ΔIFN-γ/IL-10(每1单位) 最大径、消融边界<5 mm、CEA升高 −0.58 0.24 0.56 0.35~0.90 5.81 0.016* 术后3个月IFN-γ/IL-10(每1单位) 最大径、消融边界<5 mm、CEA升高 −0.61 0.24 0.54 0.34~0.87 6.46 0.011* 术后3个月ΔIFN-γ/IL-10(每1单位) 最大径、消融边界<5 mm、CEA升高 −0.55 0.24 0.58 0.36~0.93 5.17 0.023* *P < 0.05。
下载: 导出CSV
-
[1] Valderrama-Treviño A I, Barrera-Mera B, Ceballos-Villalva J C, et al. Hepatic metastasis from colorectal cancer[J]. Eurasian J Hepato Gastroenterol, 2017, 7(2): 166-175. doi: 10.5005/jp-journals-10018-1241 [2] Martin J, Petrillo A, Smyth E C, et al. Colorectal liver metastases: Current management and future perspectives[J]. World J Clin Oncol, 2020, 11(10): 761-808. doi: 10.5306/wjco.v11.i10.761 [3] Akhan O, Akçalar S, Ünal E, et al. Radiofrequency ablation for colorectal cancer liver metastases: Outcomes and prognostic factors associated with survival[J]. Turk J Gastroenterol, 2023, 34(6): 645-651. [4] Keisari Y, Kelson I. Tumor ablation induced anti-tumor immunity: Destruction of the tumor in situ with the aim to evoke a robust anti-tumor immune response[J]. Cancer Metastasis Rev, 2023, 42(4): 1065-1068. doi: 10.1007/s10555-023-10150-x [5] Gocher A M, Workman C J, Vignali D A A. Interferon-γ: Teammate or opponent in the tumour microenvironment?[J]. Nat Rev Immunol, 2022, 22(3): 158-172. doi: 10.1038/s41577-021-00566-3 [6] Sato T, Terai M, Tamura Y, et al. Interleukin 10 in the tumor microenvironment: A target for anticancer immunotherapy[J]. Immunol Res, 2011, 51(2-3): 170-182. doi: 10.1007/s12026-011-8262-6 [7] Zhou E, Huang Q, Wang J, et al. Up-regulation of Tim-3 is associated with poor prognosis of patients with colon cancer[J]. Int J Clin Exp Pathol, 2015, 8(7): 8018-8027. [8] Chen C, Zhao F, Peng J, et al. Soluble Tim-3 serves as a tumor prognostic marker and therapeutic target for CD8+ T cell exhaustion and anti-PD-1 resistance[J]. Cell Rep Med, 2024, 5(8): 101686. doi: 10.1016/j.xcrm.2024.101686 [9] Halazun K J, Aldoori A, Malik H Z, et al. Elevated preoperative neutrophil to lymphocyte ratio predicts survival following hepatic resection for colorectal liver metastases[J]. Eur J Surg Oncol EJSO, 2008, 34(1): 55-60. doi: 10.1016/j.ejso.2007.02.014 [10] Tomita K, Matsui Y, Uka M, et al. Evidence on percutaneous radiofrequency and microwave ablation for liver metastases over the last decade[J]. Jpn J Radiol, 2022, 40(10): 1035-1045. doi: 10.1007/s11604-022-01335-5 [11] Ahmed M, Solbiati L, Brace C L, et al. Image-guided tumor ablation: Standardization of terminology and reporting criteria—a 10-year update[J]. J Vasc Interv Radiol, 2014, 25(11): 1691-1705. e4. [12] Dindo D, Demartines N, Clavien P A. Classification of surgical complications: A new proposal with evaluation in a cohort of 6336 patients and results of a survey[J]. Ann Surg, 2004, 240(2): 205-213. doi: 10.1097/01.sla.0000133083.54934.ae [13] Zheng P, Ren L, Feng Q, et al. Differences in clinical characteristics and mutational pattern between synchronous and metachronous colorectal liver metastases[J]. Cancer Manag Res, 2018, 10: 2871-2881. doi: 10.2147/CMAR.S161392 [14] Frenkel N, Poghosyan S, van Wijnbergen J W, et al. Differential cytokine and chemokine expression after ablation vs. resection in colorectal cancer liver metastasis[J]. Surg Open Sci, 2024, 18: 29-34. doi: 10.1016/j.sopen.2024.01.005 [15] Chlorogiannis D D, Sotirchos V S, Georgiades C, et al. The importance of optimal thermal ablation margins in colorectal liver metastases: A systematic review and meta-analysis of 21 studies[J]. Cancers, 2023, 15(24): 5806. doi: 10.3390/cancers15245806 [16] Chlorogiannis D D, Sotirchos V S, Sofocleous C T. Oncologic outcomes after percutaneous ablation for colorectal liver metastases: An updated comprehensive review[J]. Medicina (Kaunas), 2024, 60(9): 1536. doi: 10.3390/medicina60091536 [17] Mokhtari Z, Rezaei M, Sanei M H, et al. Tim3 and PD-1 as a therapeutic and prognostic targets in colorectal cancer: Relationship with sidedness, clinicopathological parameters, and survival[J]. Front Oncol, 2023, 13: 1069696. doi: 10.3389/fonc.2023.1069696 [18] Karami R, Fathi M, Jalali P, et al. The emerging role of TIM-3 in colorectal cancer: A promising target for immunotherapy[J]. Expert Opin Ther Targets, 2024, 28(12): 1093-1115. doi: 10.1080/14728222.2024.2442437 [19] Bailly C, Thuru X, Goossens L, et al. Soluble TIM-3 as a biomarker of progression and therapeutic response in cancers and other of human diseases[J]. Biochem Pharmacol, 2023, 209: 115445. doi: 10.1016/j.bcp.2023.115445 [20] Zhou H, Liu Z, Wang Y, et al. Colorectal liver metastasis: Molecular mechanism and interventional therapy[J]. Sig Transduct Target Ther, 2022, 7(1): 70. doi: 10.1038/s41392-022-00922-2 [21] Wang Y, Zhong X, He X, et al. Liver metastasis from colorectal cancer: Pathogenetic development, immune landscape of the tumour microenvironment and therapeutic approaches[J]. J Exp Clin Cancer Res, 2023, 42(1): 177. doi: 10.1186/s13046-023-02729-7 [22] Sullivan K M, Jiang X, Guha P, et al. Blockade of interleukin 10 potentiates antitumour immune function in human colorectal cancer liver metastases[J]. Gut, 2023, 72(2): 325-337. doi: 10.1136/gutjnl-2021-325808 [23] Qi X, Zhu Z, Tacke F, et al. Systemic immune response induced by radiofrequency ablation versus microwave ablation at varying powers in murine models of hepatocellular carcinoma[J]. Transl Cancer Res, 2025, 14(6): 3746-3757. doi: 10.21037/tcr-2025-915 [24] Li J, Pang C, Liu G, et al. Thermal ablation with and without adjuvant systemic therapy: A nationwide multicenter observational cohort study of solitary colorectal liver metastases[J]. Int J Surg, 2024, 110(7): 4240-4248. doi: 10.1097/JS9.0000000000001397 [25] 王安民, 刘忠发, 杨春辉, 等. 云南地区412例结直肠癌错配修复与微卫星状态的一致性及相关性分析[J]. 昆明医科大学学报, 2025, 46(12): 101-111. doi: 10.12259/j.issn.2095-610X.S20251212 -

 点击查看大图
计量
- 文章访问数: 1
- HTML全文浏览量: 1
- PDF下载量: 1
- 被引次数: 0
