




Clinical Evaluation Value of Nrf2-Keap1-Mediated Oxidative Stress Response in the Prognosis of Combined Periodontal-Orthodontic Treatment in Patients with Periodontitis
-
摘要:
目的 探究核因子E2相关因子2(nuclear factor erythroid 2-related factor 2,Nrf2)-Kelch样ECH相关蛋白1(Kelch-like ECH-associated protein 1,Keap1)介导的氧化应激反应与牙周炎患者牙周-正畸联合治疗预后的关系,评价相关氧化应激指标对患者预后的预测价值,为牙周炎患者预后评估提供参考依据。 方法 本研究采用病例对照设计,选取 2023 年 4 月至 2025 年 4 月于中国人民解放军南部战区总医院就诊的 148 例慢性牙周炎患者作为研究组,同期 100 例健康体检个体作为对照组。收集两组受试者空腹静脉血,采用酶联免疫吸附试验(enzyme-linked immunosorbent assay,ELISA)检测血清中 Nrf2、Keap1、谷胱甘肽(glutathione,GSH)、超氧化物歧化酶(superoxide dismutase,SOD)和丙二醛(malondialdehyde,MDA)水平,并检测牙周指标,包括龈沟出血指数(sulcus bleeding index,SBI)、菌斑指数(plaque index,PLI)、附着丧失(attachment loss,AL)及牙周探诊深度(probing depth,PD)。比较两组上述指标的差异,分析牙周炎患者血清指标与牙周指标的相关性,比较不同预后患者的血清指标水平,通过受试者工作特征(receiver operating characteristic,ROC)曲线分析各指标及联合检测对预后的预测价值。 结果 研究组血清MDA、Keap1水平及牙周指标SBI、PLI、AL、PD均高于对照组,血清GSH、SOD、Nrf2水平低于对照组(P < 0.05)。Pearson相关性分析显示,血清MDA、Keap1水平与牙周指标呈正相关,血清GSH、SOD、Nrf2水平与牙周指标呈负相关(P < 0.05)。依据治疗后12个月随访时的牙周临床指标判定预后,预后不良组治疗前PD、PLI、血清MDA、Keap1水平明显高于预后良好组,牙槽骨高度及血清GSH、SOD、Nrf2水平明显低于预后良好组(P < 0.05)。ROC曲线分析显示,血清MDA、GSH、SOD、Keap1、Nrf2联合预测预后的曲线下面积(area under the curve,AUC)为0.892,优于各指标单独预测。 结论 Nrf2-Keap1 介导的氧化应激反应与牙周炎的发生发展及治疗预后密切相关,血清 MDA、GSH、SOD、Keap1 和 Nrf2 可作为评估牙周炎患者牙周 - 正畸联合治疗预后的有效生物标志物,联合检测能提高预测准确性,为临床治疗提供参考。 -
关键词:
- 牙周炎 /
- Nrf2-Keap1 信号通路 /
- 氧化应激 /
- 预后 /
- 生物标志物
Abstract:Objective To investigate the relationship between oxidative stress response mediated by nuclear factor erythroid 2-related factor 2 (Nrf2)–Kelch-like ECH-associated protein 1 (Keap1) and the prognosis of combined periodontal–orthodontic treatment in patients with periodontitis, to evaluate the predictive value of relevant oxidative stress indicators for patient prognosis, and to provide a reference basis for prognostic assessment in patients with periodontitis. Methods This study adopted a case–control design. A total of 148 patients with chronic periodontitis who attended the General Hospital of Southern Theater Command of the Chinese People's Liberation Army between April 2023 and April 2025 were enrolled as the study group, and 100 healthy individuals undergoing physical examinations during the same period served as the control group. Fasting venous blood was collected from subjects in both groups. Enzyme-linked immunosorbent assay (ELISA) was used to detect serum levels of Nrf2, Keap1, glutathione (GSH), superoxide dismutase (SOD), and malondialdehyde (MDA). Periodontal parameters were also measured, including sulcus bleeding index (SBI), plaque index (PLI), attachment loss (AL), and probing depth (PD). Differences in the above indices between the two groups were compared; the correlation between serum indicators and periodontal parameters in patients with periodontitis were analyzed, serum indicator levels were compared among patients with different prognoses; and receiver operating characteristic (ROC) curve analysis was performed to evaluate the predictive value of each indicator and their combined detection for prognosis. Results Serum MDA and Keap1 levels, as well as the periodontal parameters SBI, PLI, AL, and PD were significantly higher in the study group than in the control group, whereas serum GSH, SOD, and Nrf2 levels were significantly lower (P < 0.05). Pearson correlation analysis showed that serum MDA and Keap1 levels were positively correlated with periodontal parameters, while serum GSH, SOD, and Nrf2 levels were negatively correlated with periodontal parameters (P < 0.05). Prognosis was determined based on periodontal clinical parameters at the 12-month post-treatment follow-up. Compared with the good prognosis group, the poor prognosis group had significantly higher pre-treatment PD, PLI, serum MDA, and Keap1 levels, as well as significantly lower alveolar bone height and serum GSH, SOD, and Nrf2 levels (P < 0.05). ROC curve analysis showed that the AUC for the combined prediction of prognosis using serum MDA, GSH, SOD, Keap1, and Nrf2 was 0.892, which was superior to the predictive value of each indicator alone. Conclusion The Nrf2-Keap1- mediated oxidative stress response is closely related to the occurrence, progression, and treatment prognosis of periodontitis. Serum MDA, GSH, SOD, Keap1, and Nrf2 may serve as effective biomarkers for evaluating the prognosis of combined periodontal–orthodontic treatment in patients with periodontitis. Combined detection can improve predictive accuracy and provide a reference for clinical treatment. -
Key words:
- Periodontitis /
- Nrf2-Keap1 signaling pathway /
- Oxidative stress /
- Prognosis /
- Biomarkers
-
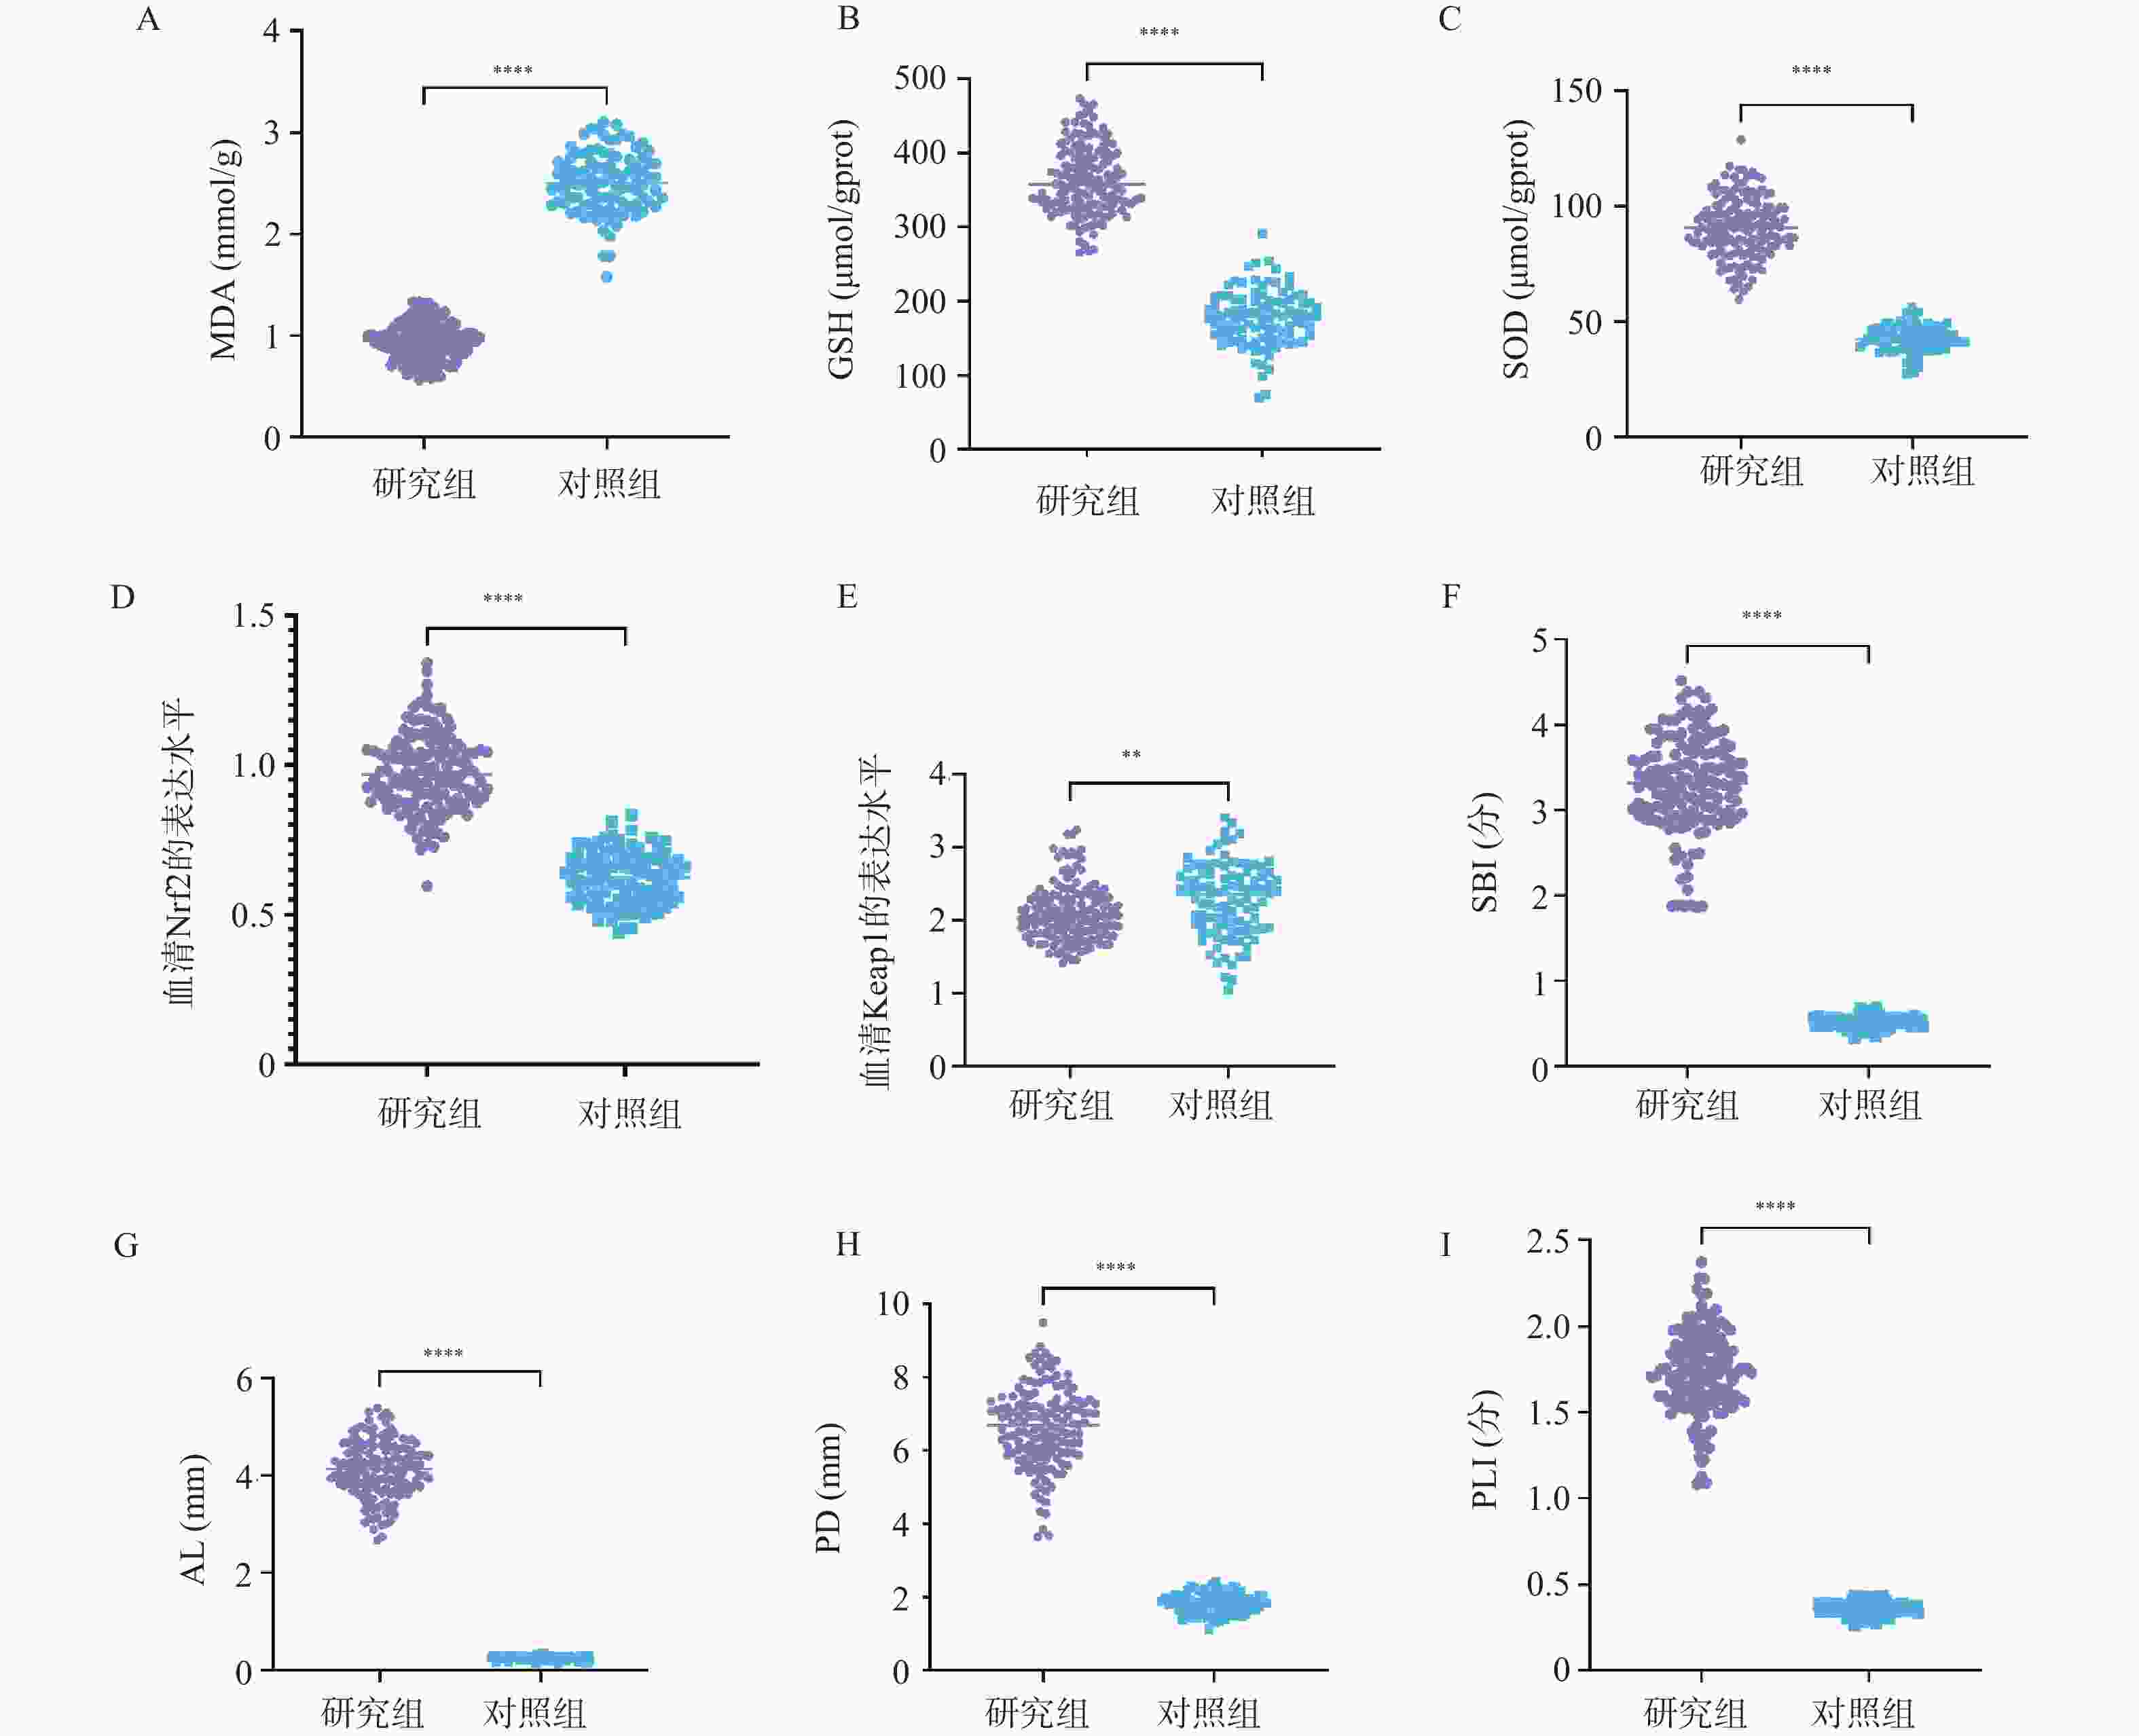
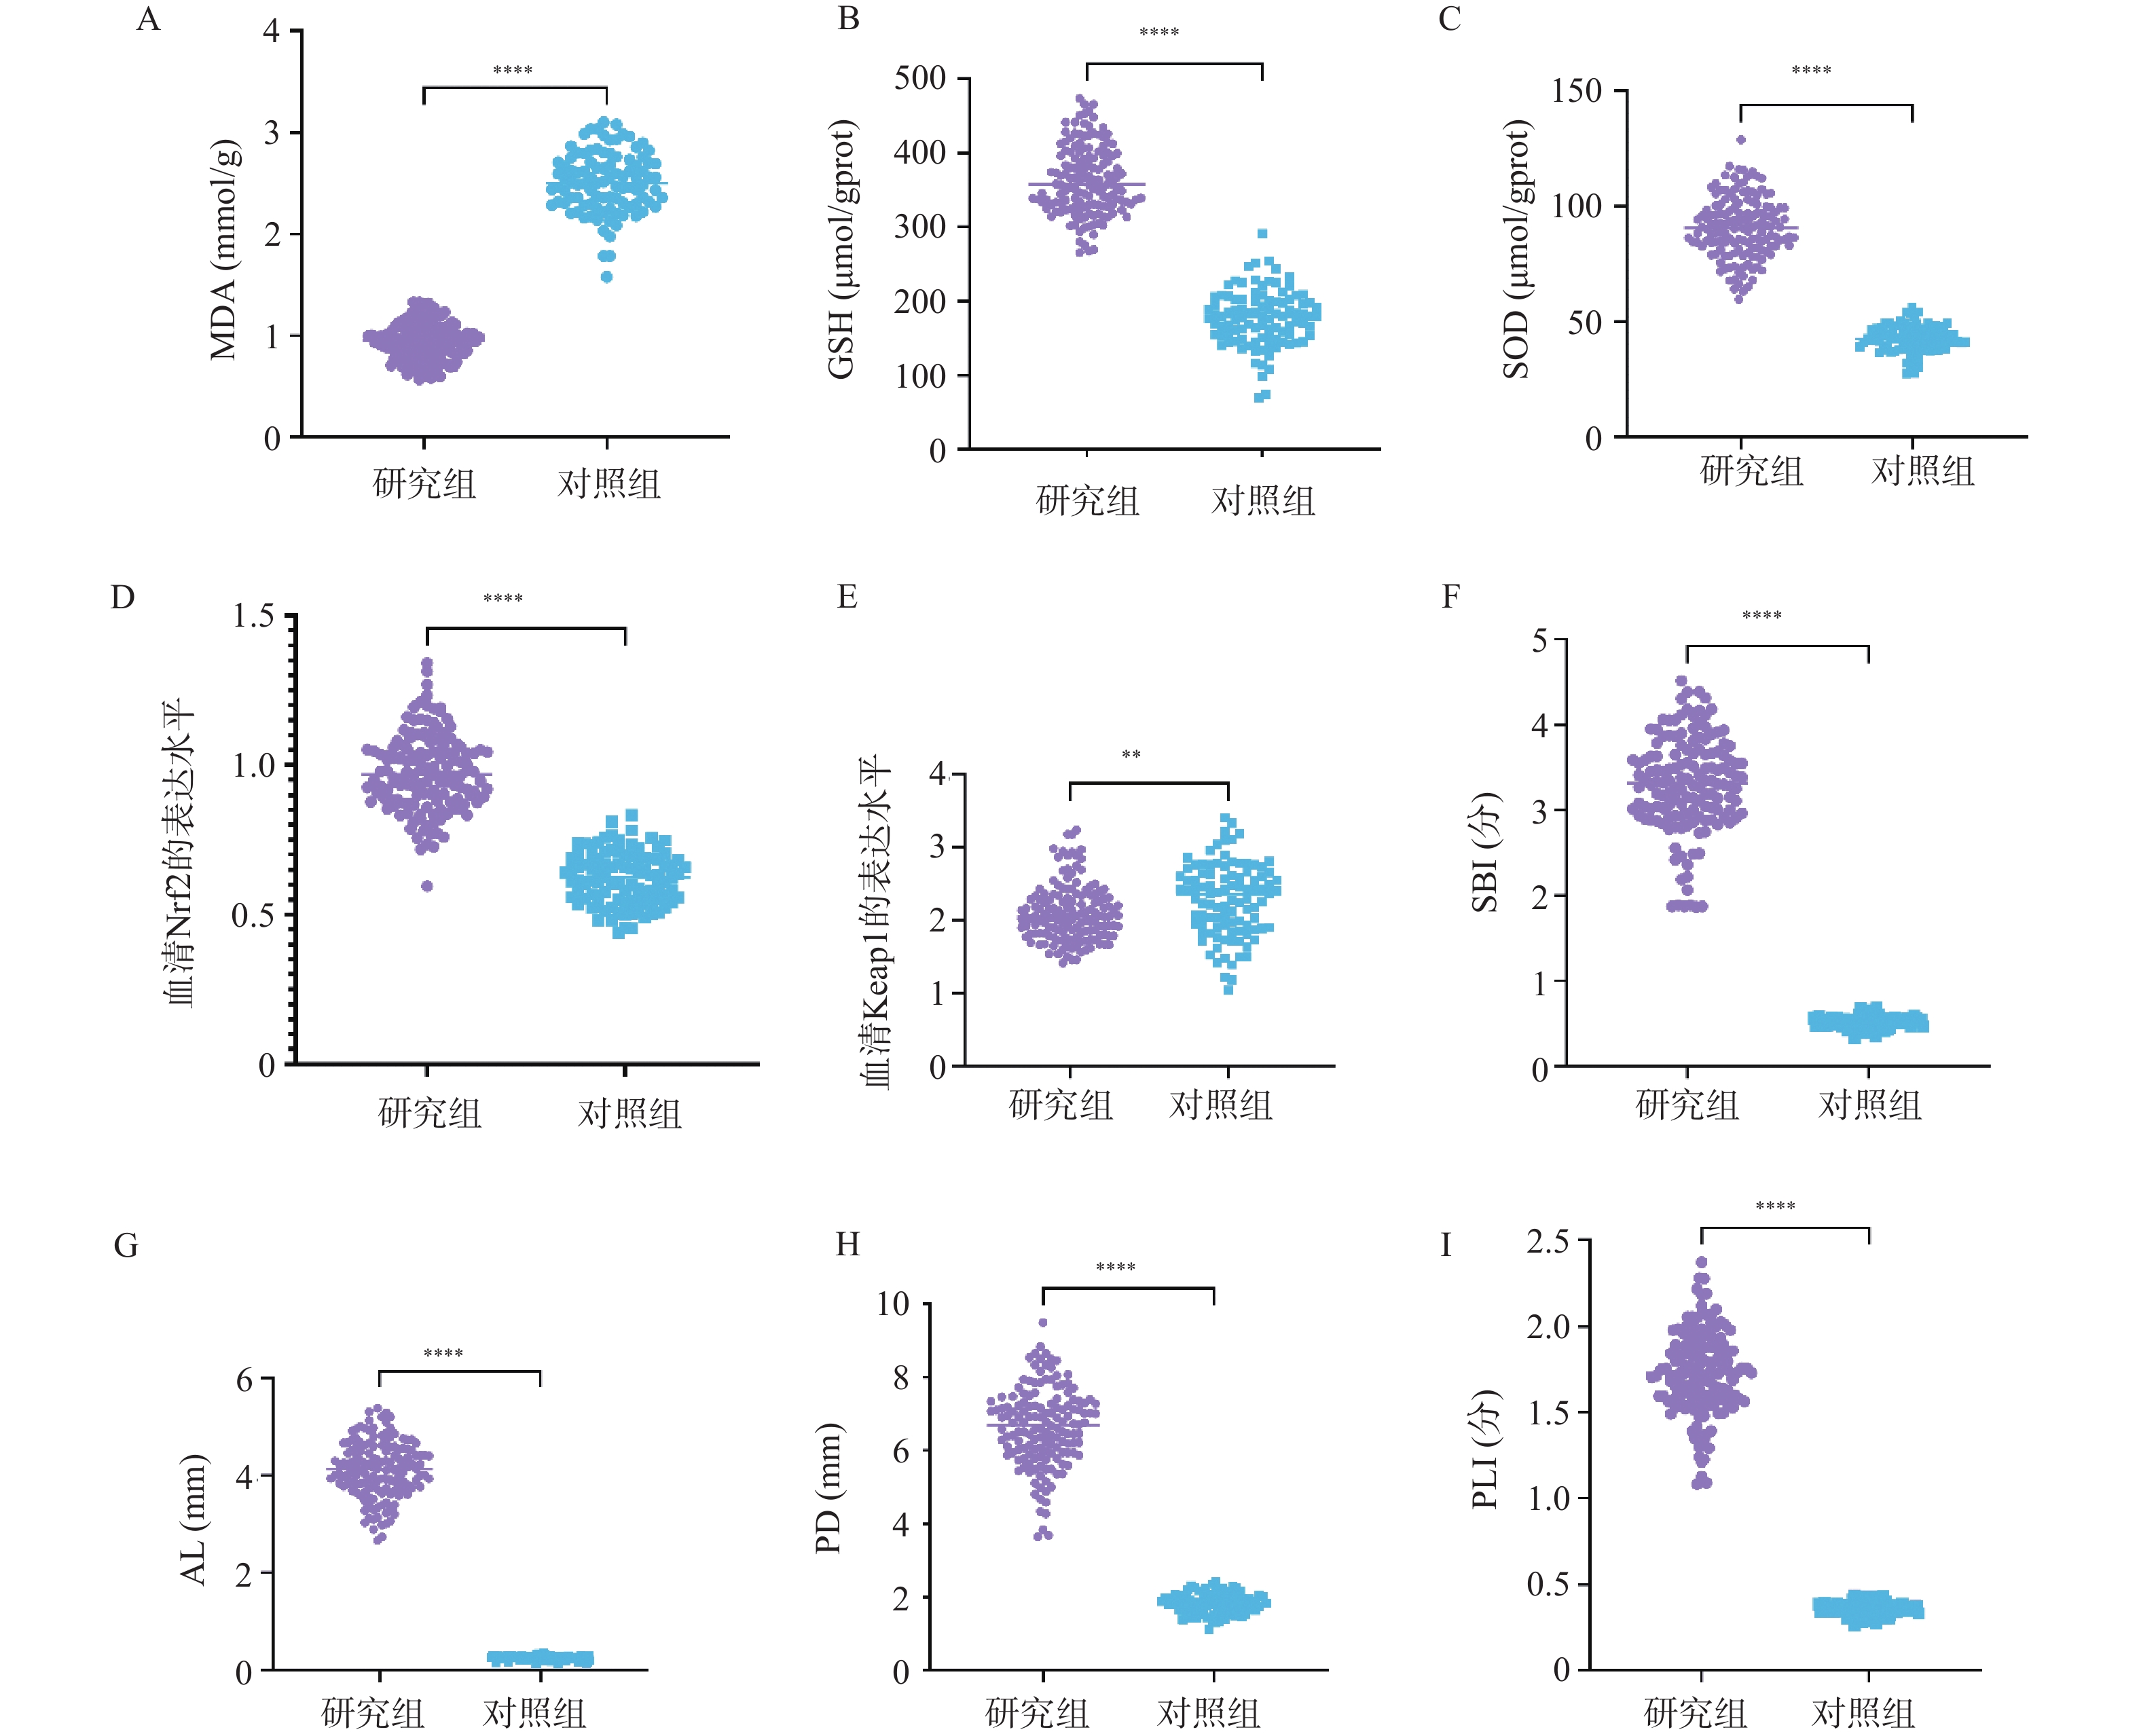
图 1 血清Keap1、Nrf2、氧化应激指标MDA、GSH、SOD水平及牙周指标比较
A:血清MDA水平;B:血清GSH水平;C:血清SOD水平;D:血清Keap1水平;E;血清Nrf2水平;F:SBI水平;G:AL水平;H;PD水平;I:菌斑指数(PLI)水平;与对照组比较,**P < 0.01;****P < 0.0001。
Figure 1. Comparison of serum Keap1 and Nrf2 levels,oxidative stress markers,and periodontal clinical parameters between the two groups
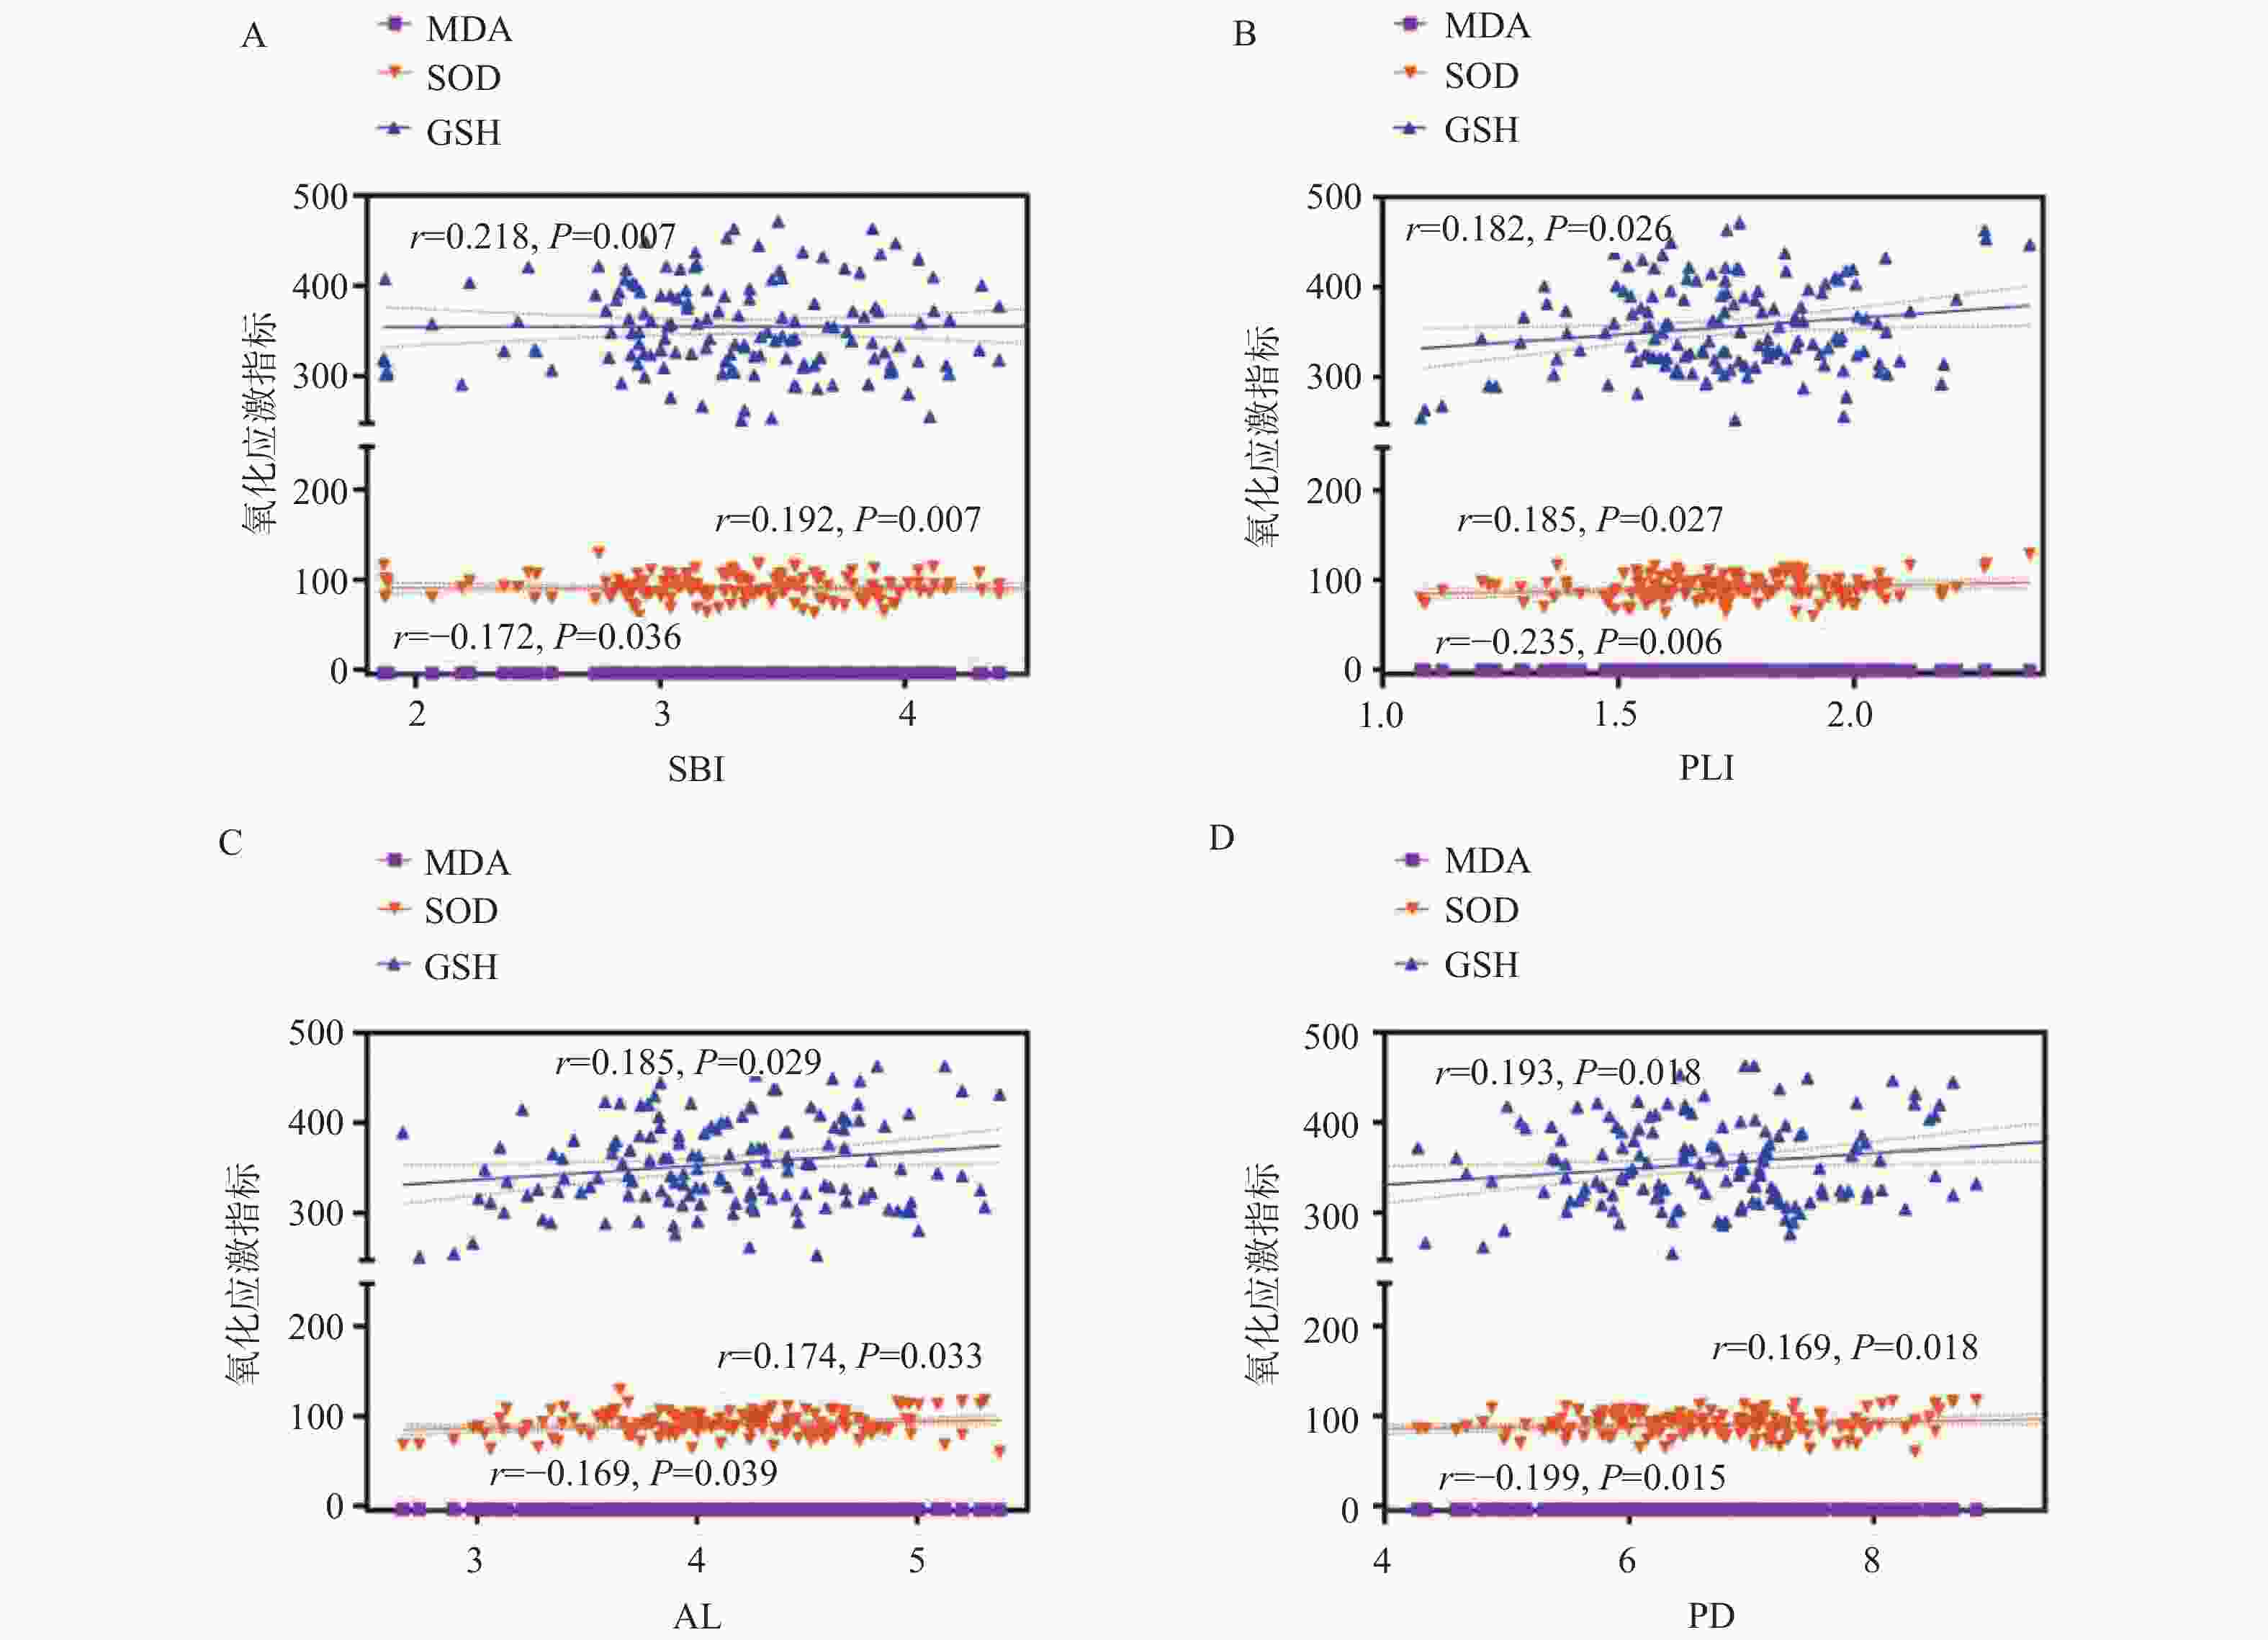
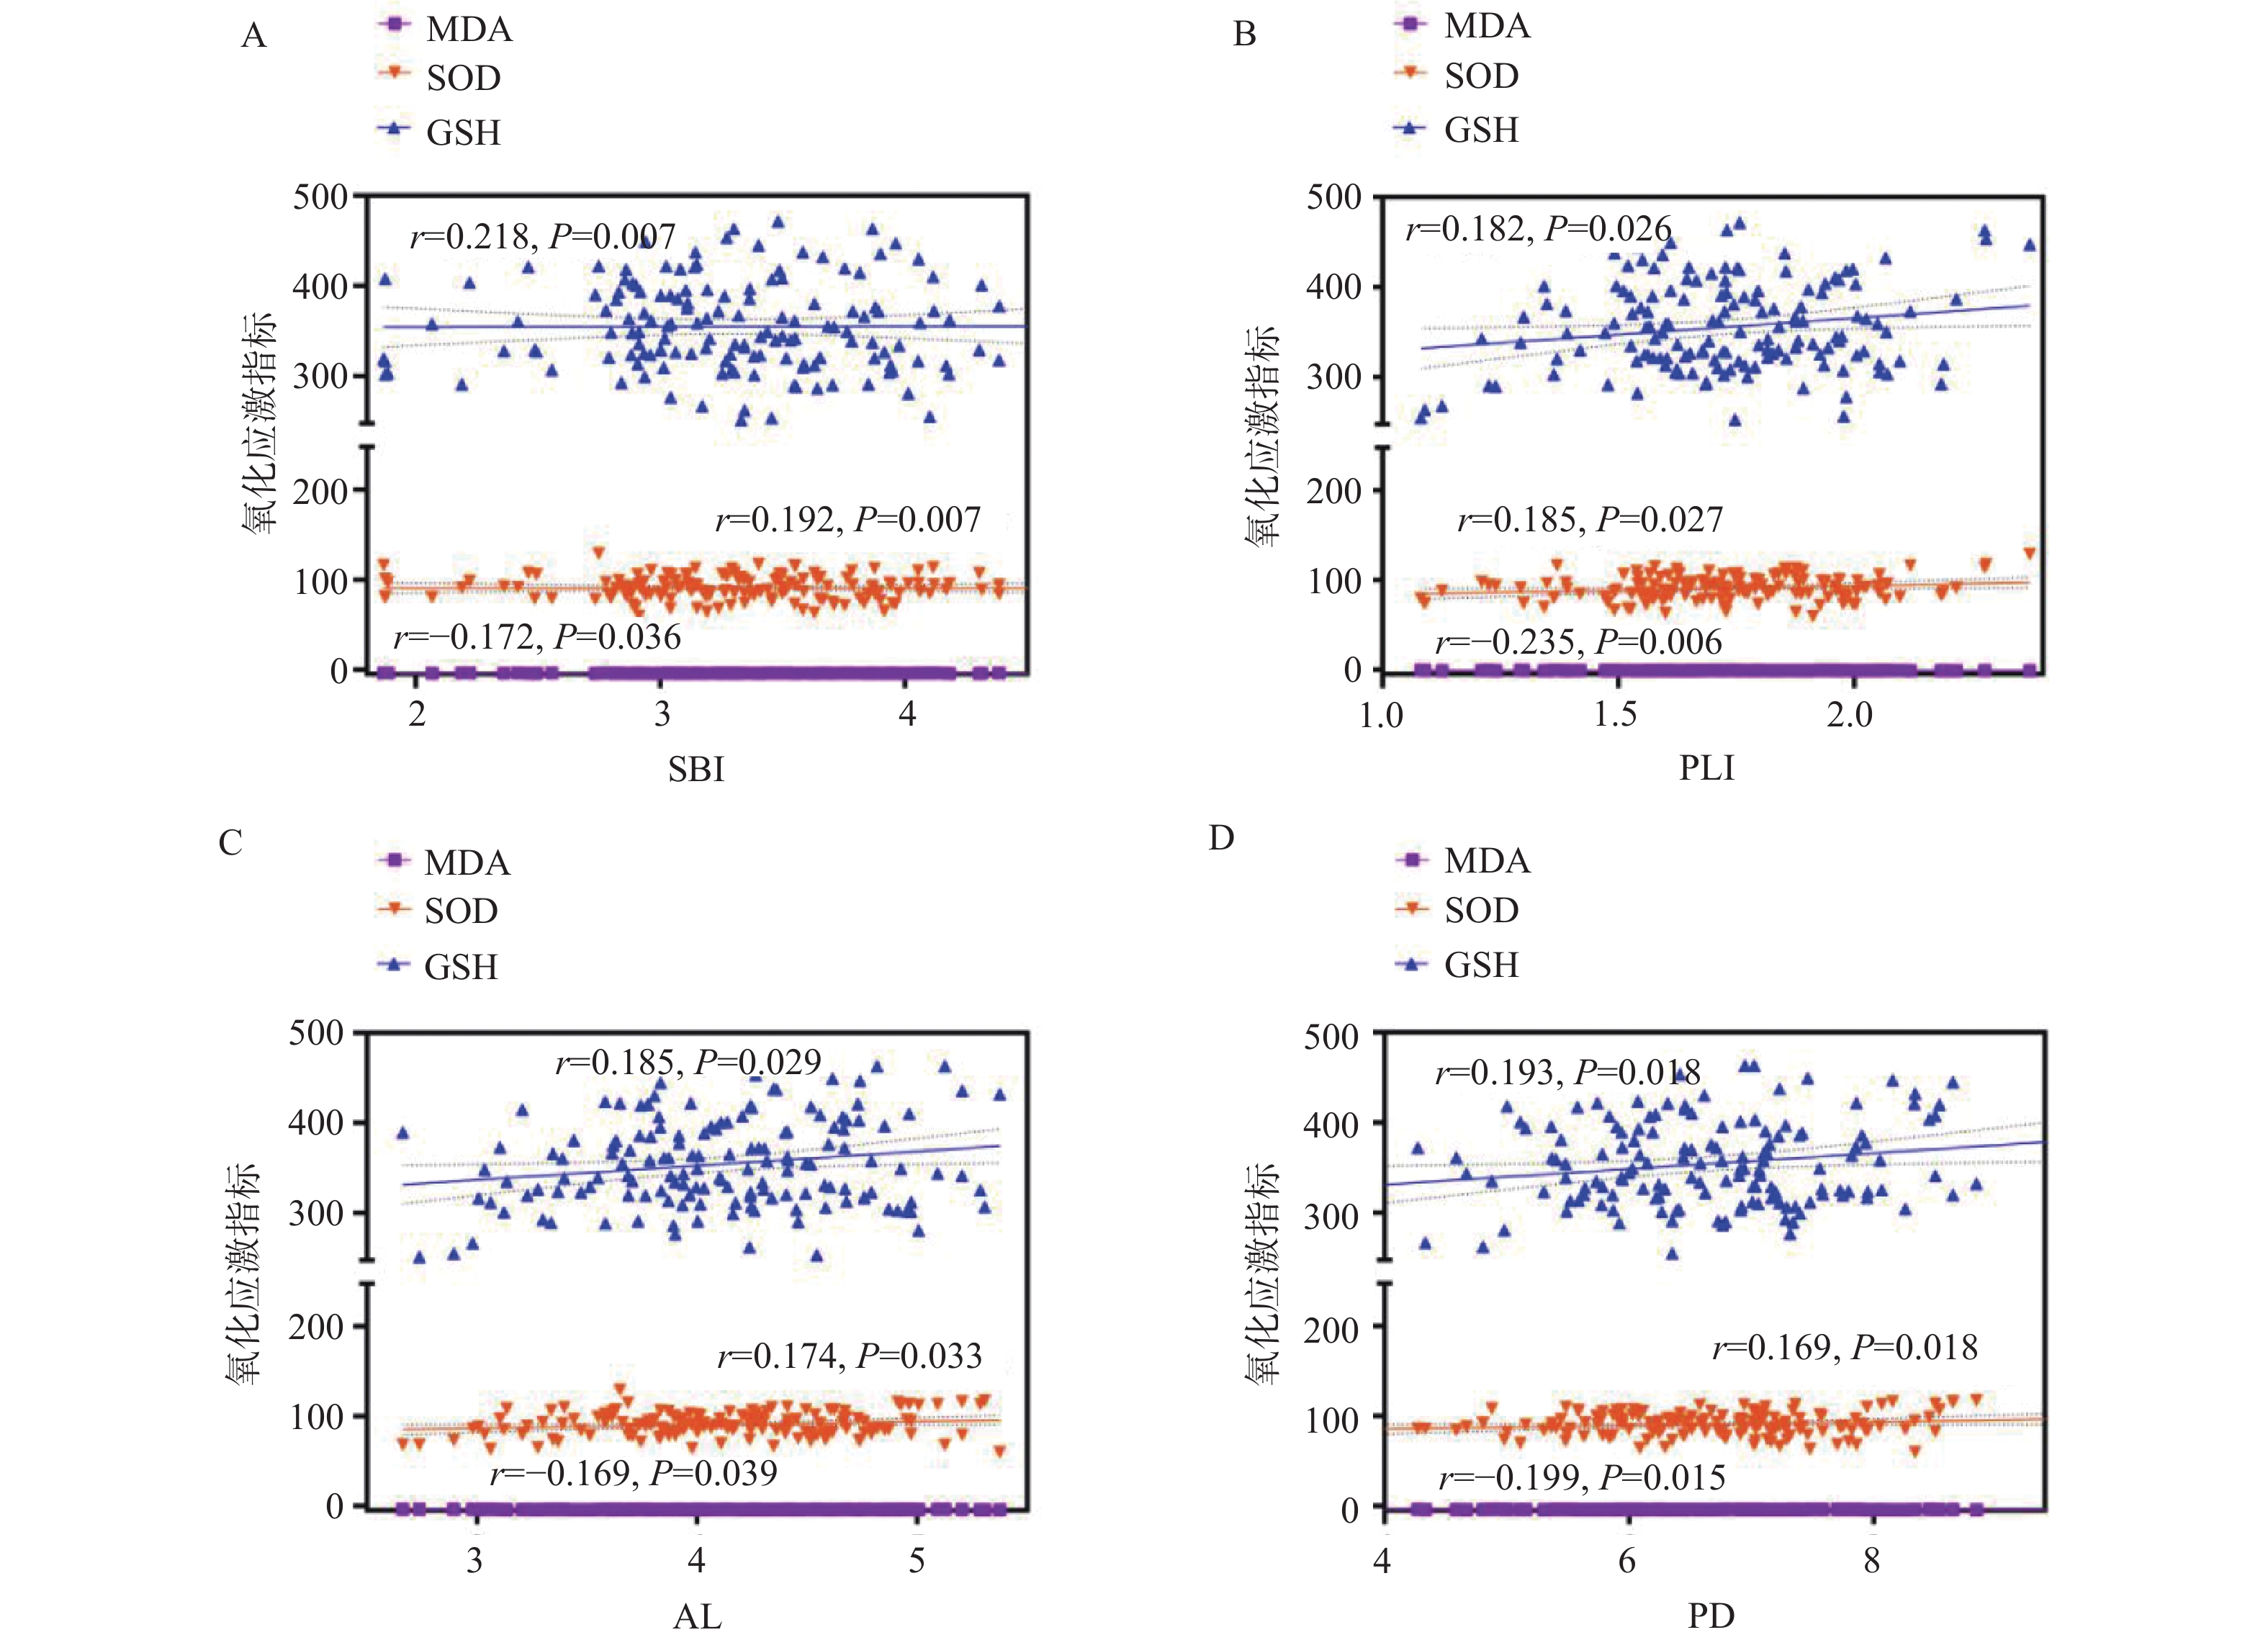
图 2 氧化应激指标MDA、GSH、SOD与牙周指标的相关性分析
A:氧化应激指标MDA、GSH、SOD与牙周指标SBI的相关性分析;B:氧化应激指标MDA、GSH、SOD与牙周指标PLI的相关性分析;C:氧化应激指标MDA、GSH、SOD与牙周指标AL的相关性分析;D:氧化应激指标MDA、GSH、SOD与牙周指标PD的相关性分析。
Figure 2. Correlation analysis of oxidative stress markers (MDA,GSH,and SOD) with periodontal clinical parameters
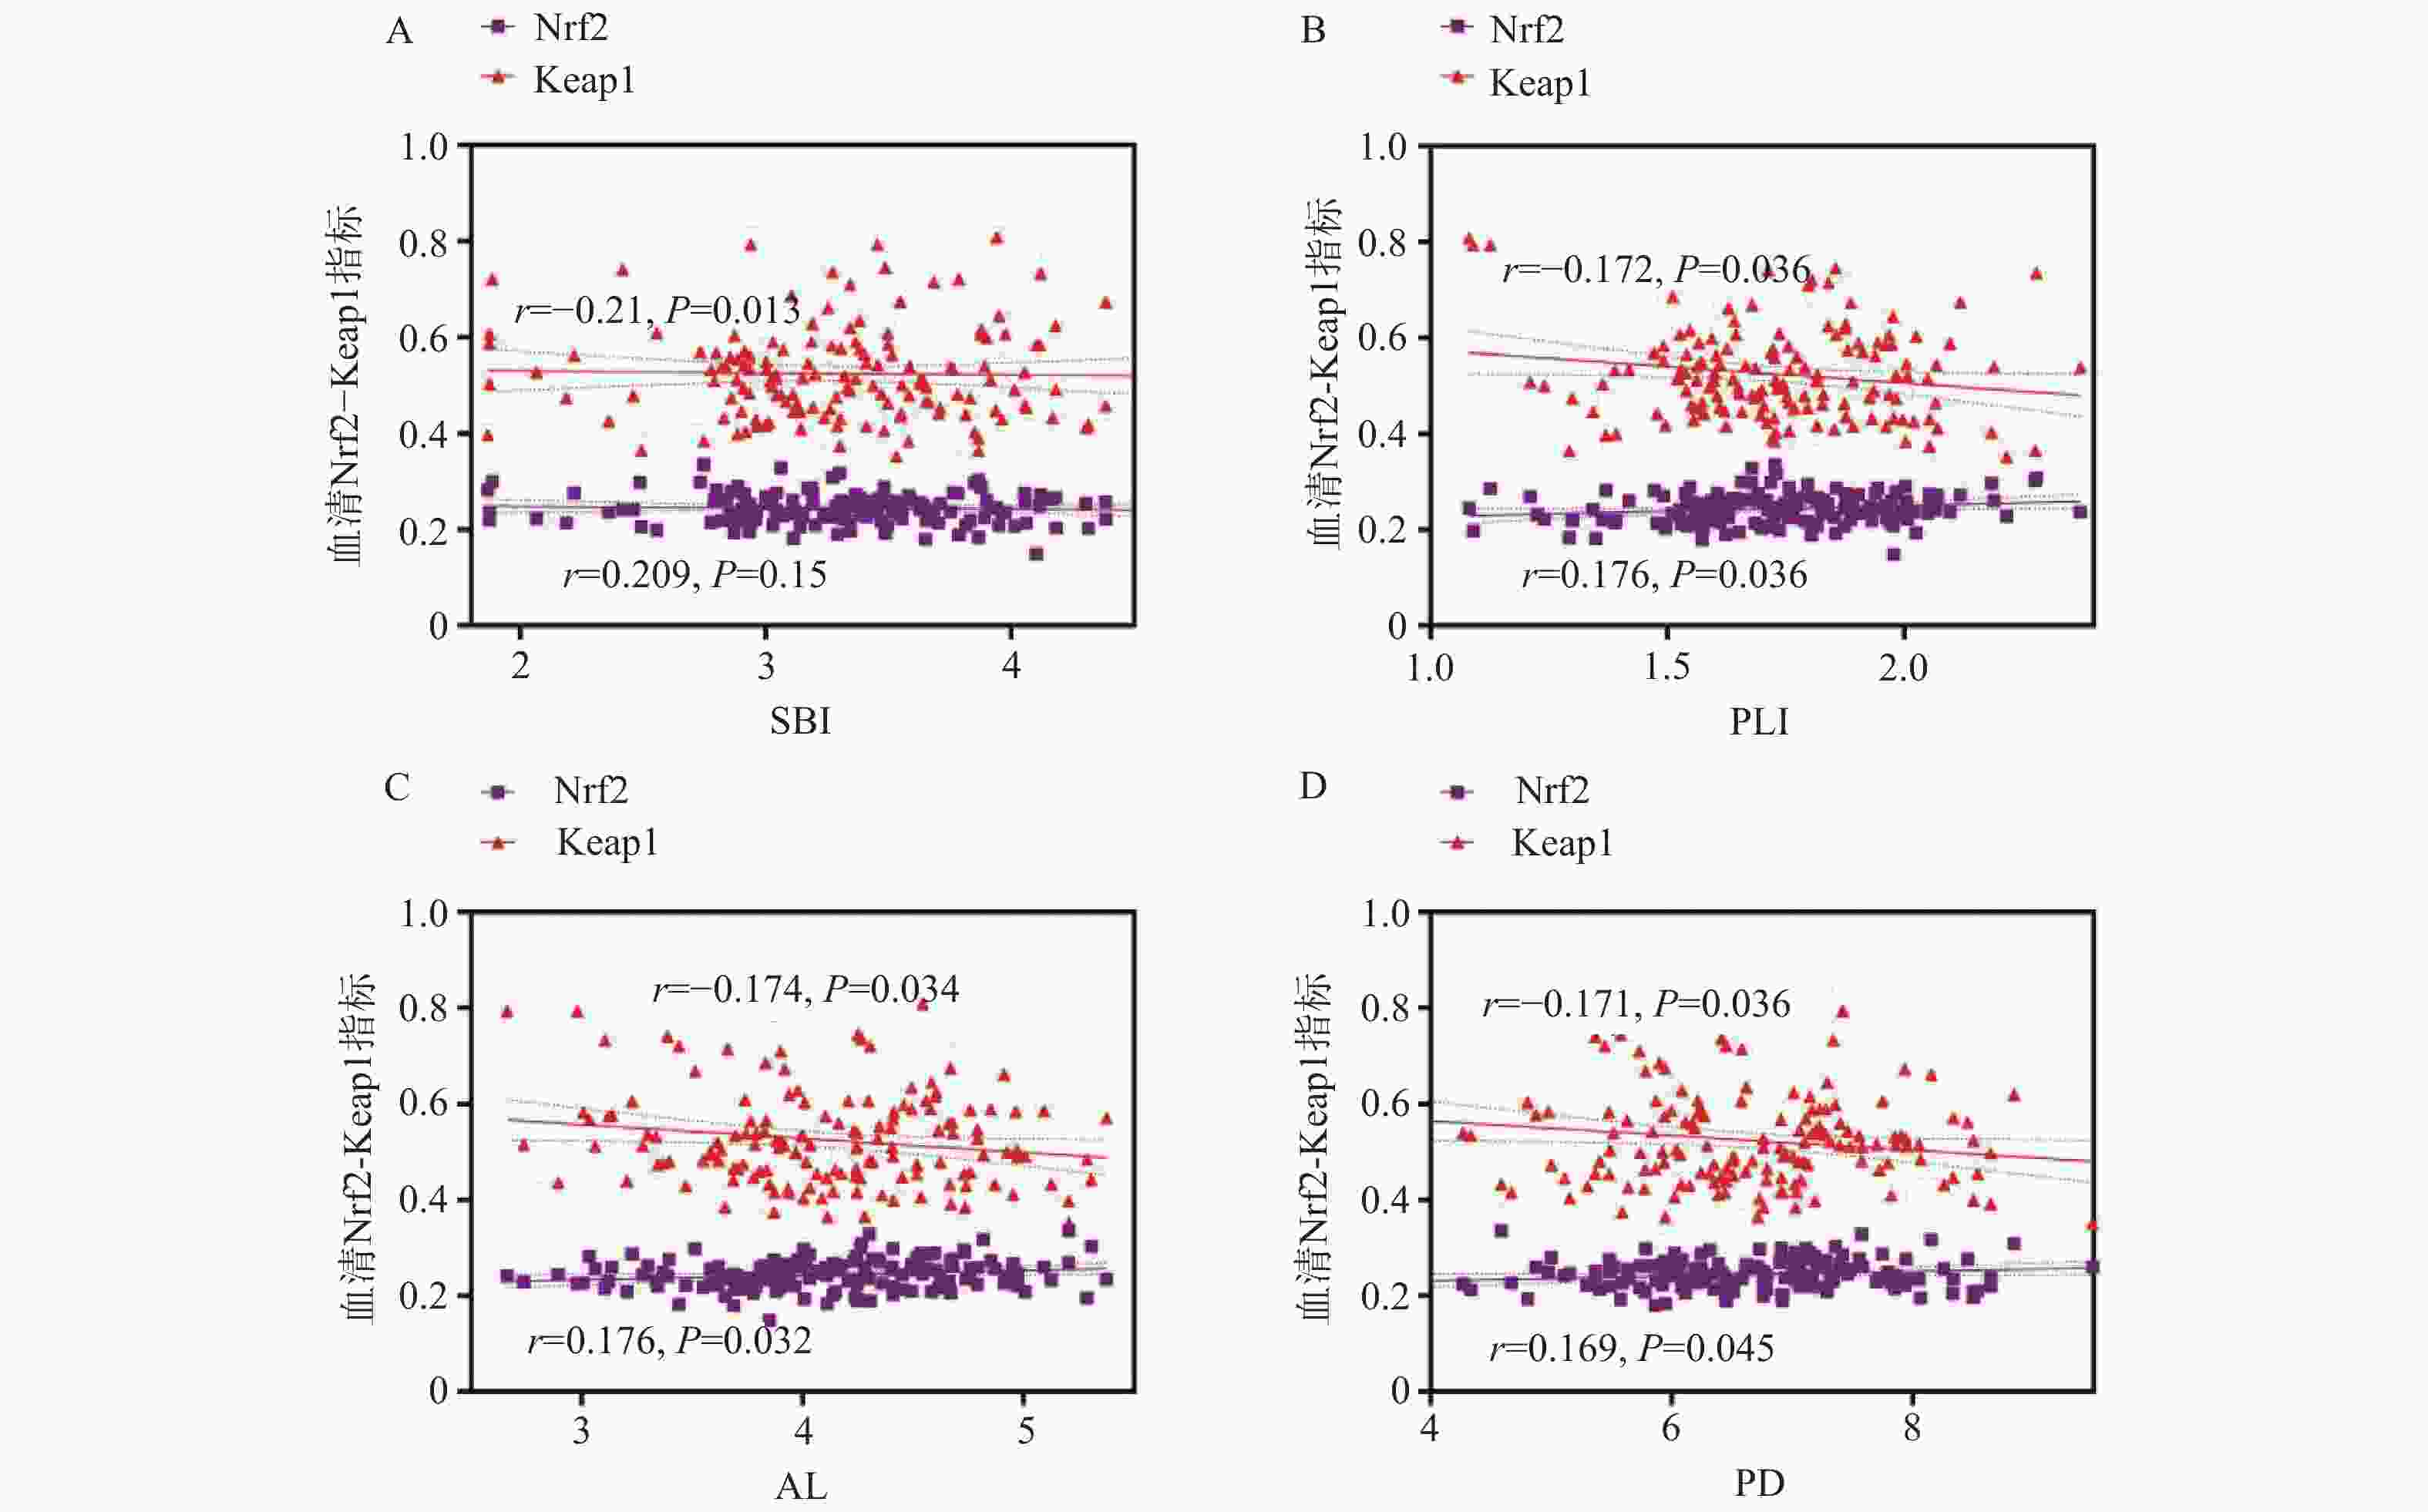
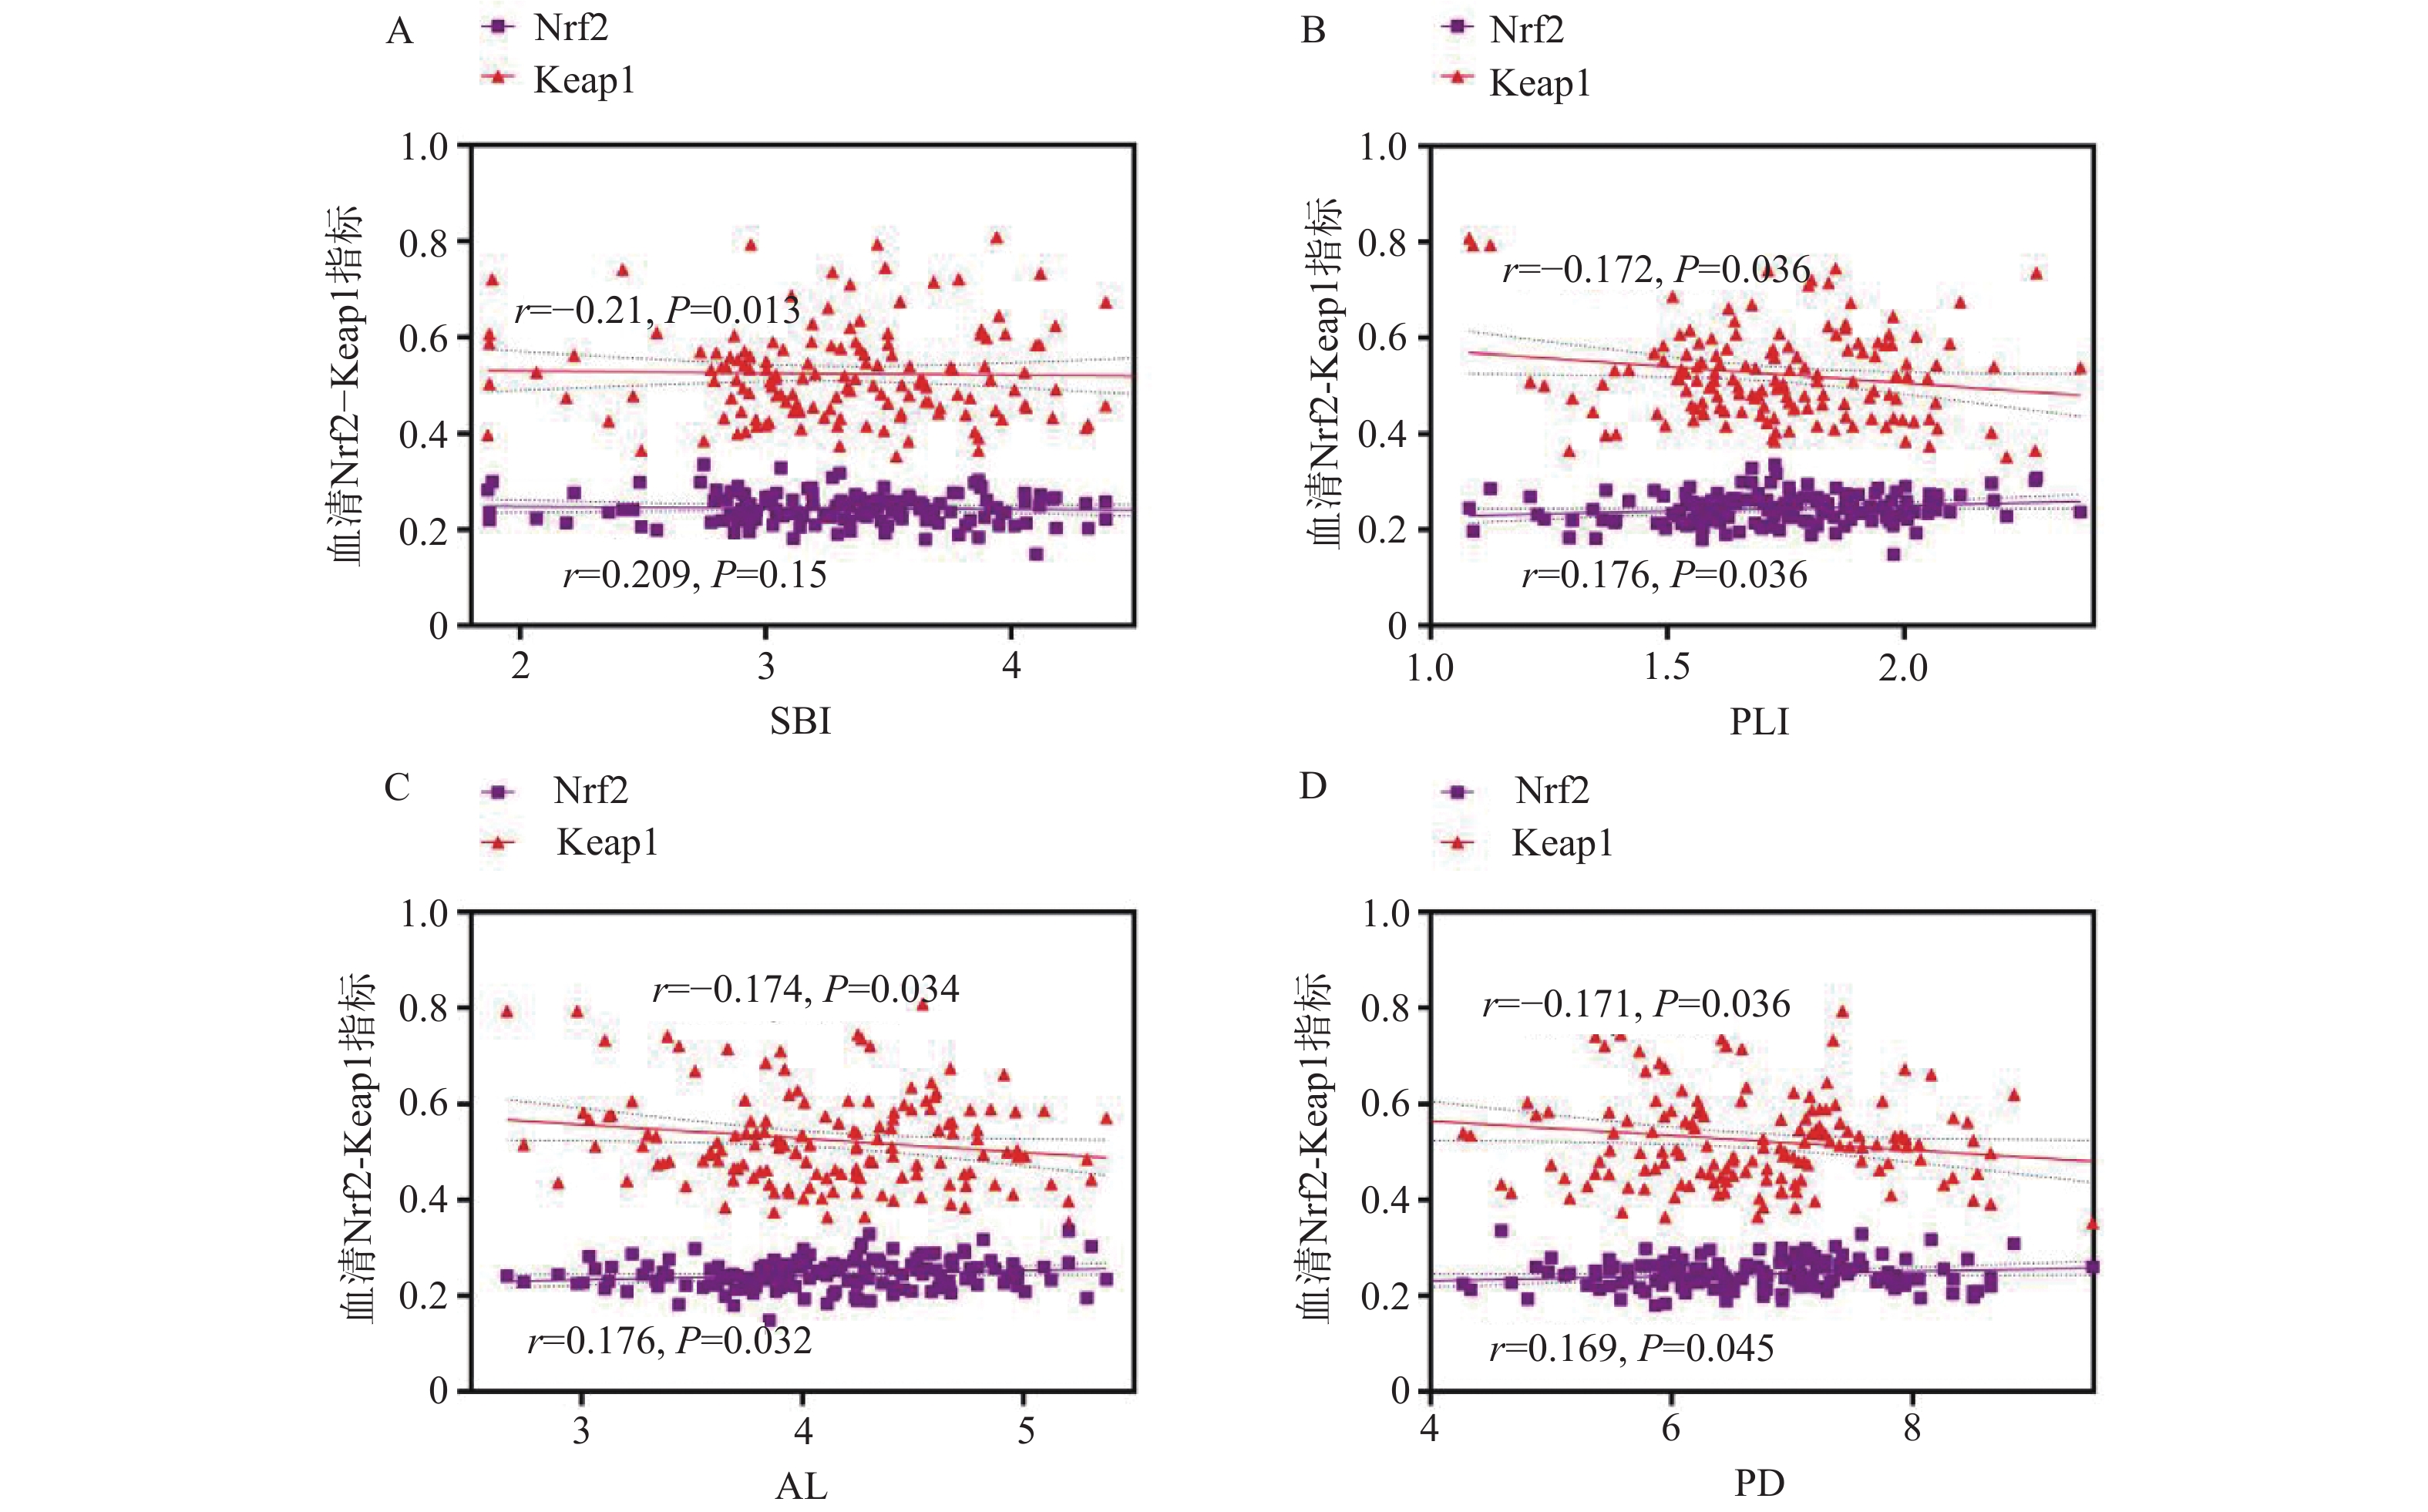
图 3 血清Keap1、Nrf2水平与牙周指标的相关性分析
A:血清Keap1、Nrf2与牙周指标SBI的相关性分析;B:血清Keap1、Nrf2与牙周指标PLI的相关性分析;C:血清Keap1、Nrf2与牙周指标AL的相关性分析;D:血清Keap1、Nrf2与牙周指标PD的相关性分析。
Figure 3. Correlation analysis of serum Keap1 and Nrf2 levels with periodontal clinical parameters

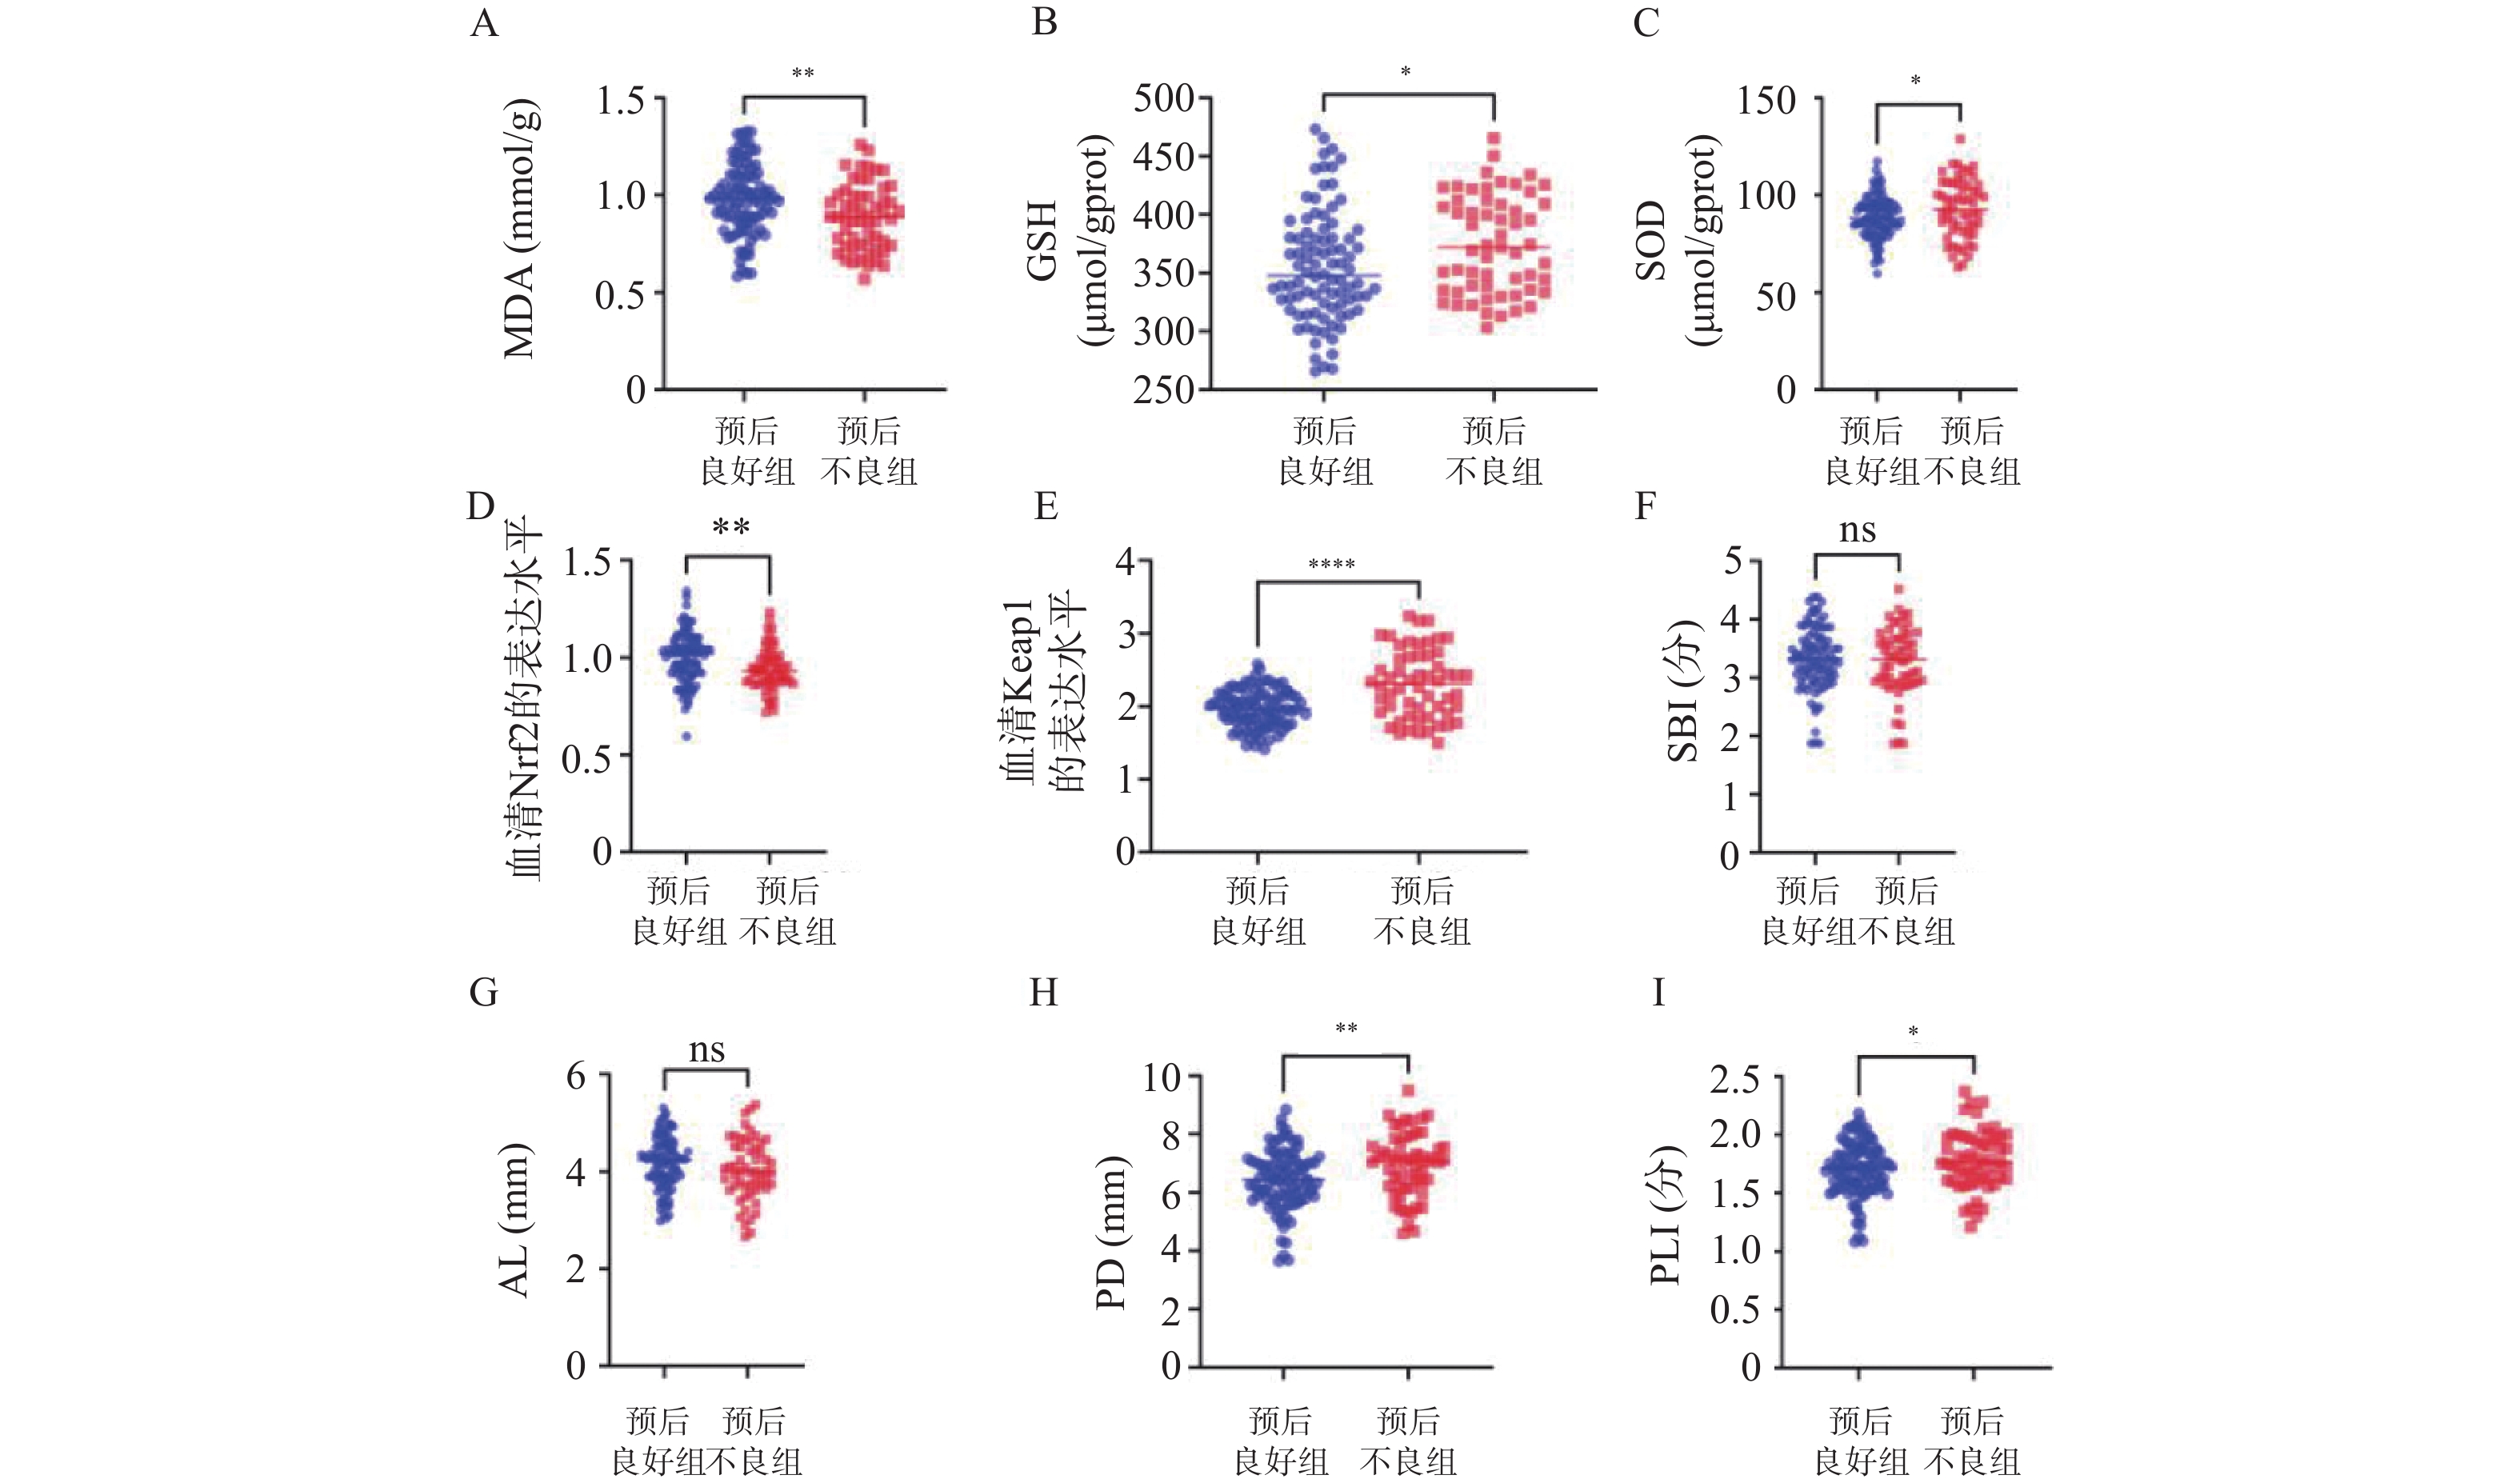
图 4 不同预后患者血清指标及牙周指标比较
A:血清MDA水平;B. 血清GSH水平;C. 血清SOD水平;D. 血清Nrf2水平;E. 血清Keap1水平;F. SBI水平;G. AL水平;H. PD水平;I. 菌斑指数(PLI)水平;与预后良好组比较,*P < 0.05;**P < 0.01; ****P < 0.0001。
Figure 4. Comparison of serum markers and periodontal indicators among patients with different prognoses
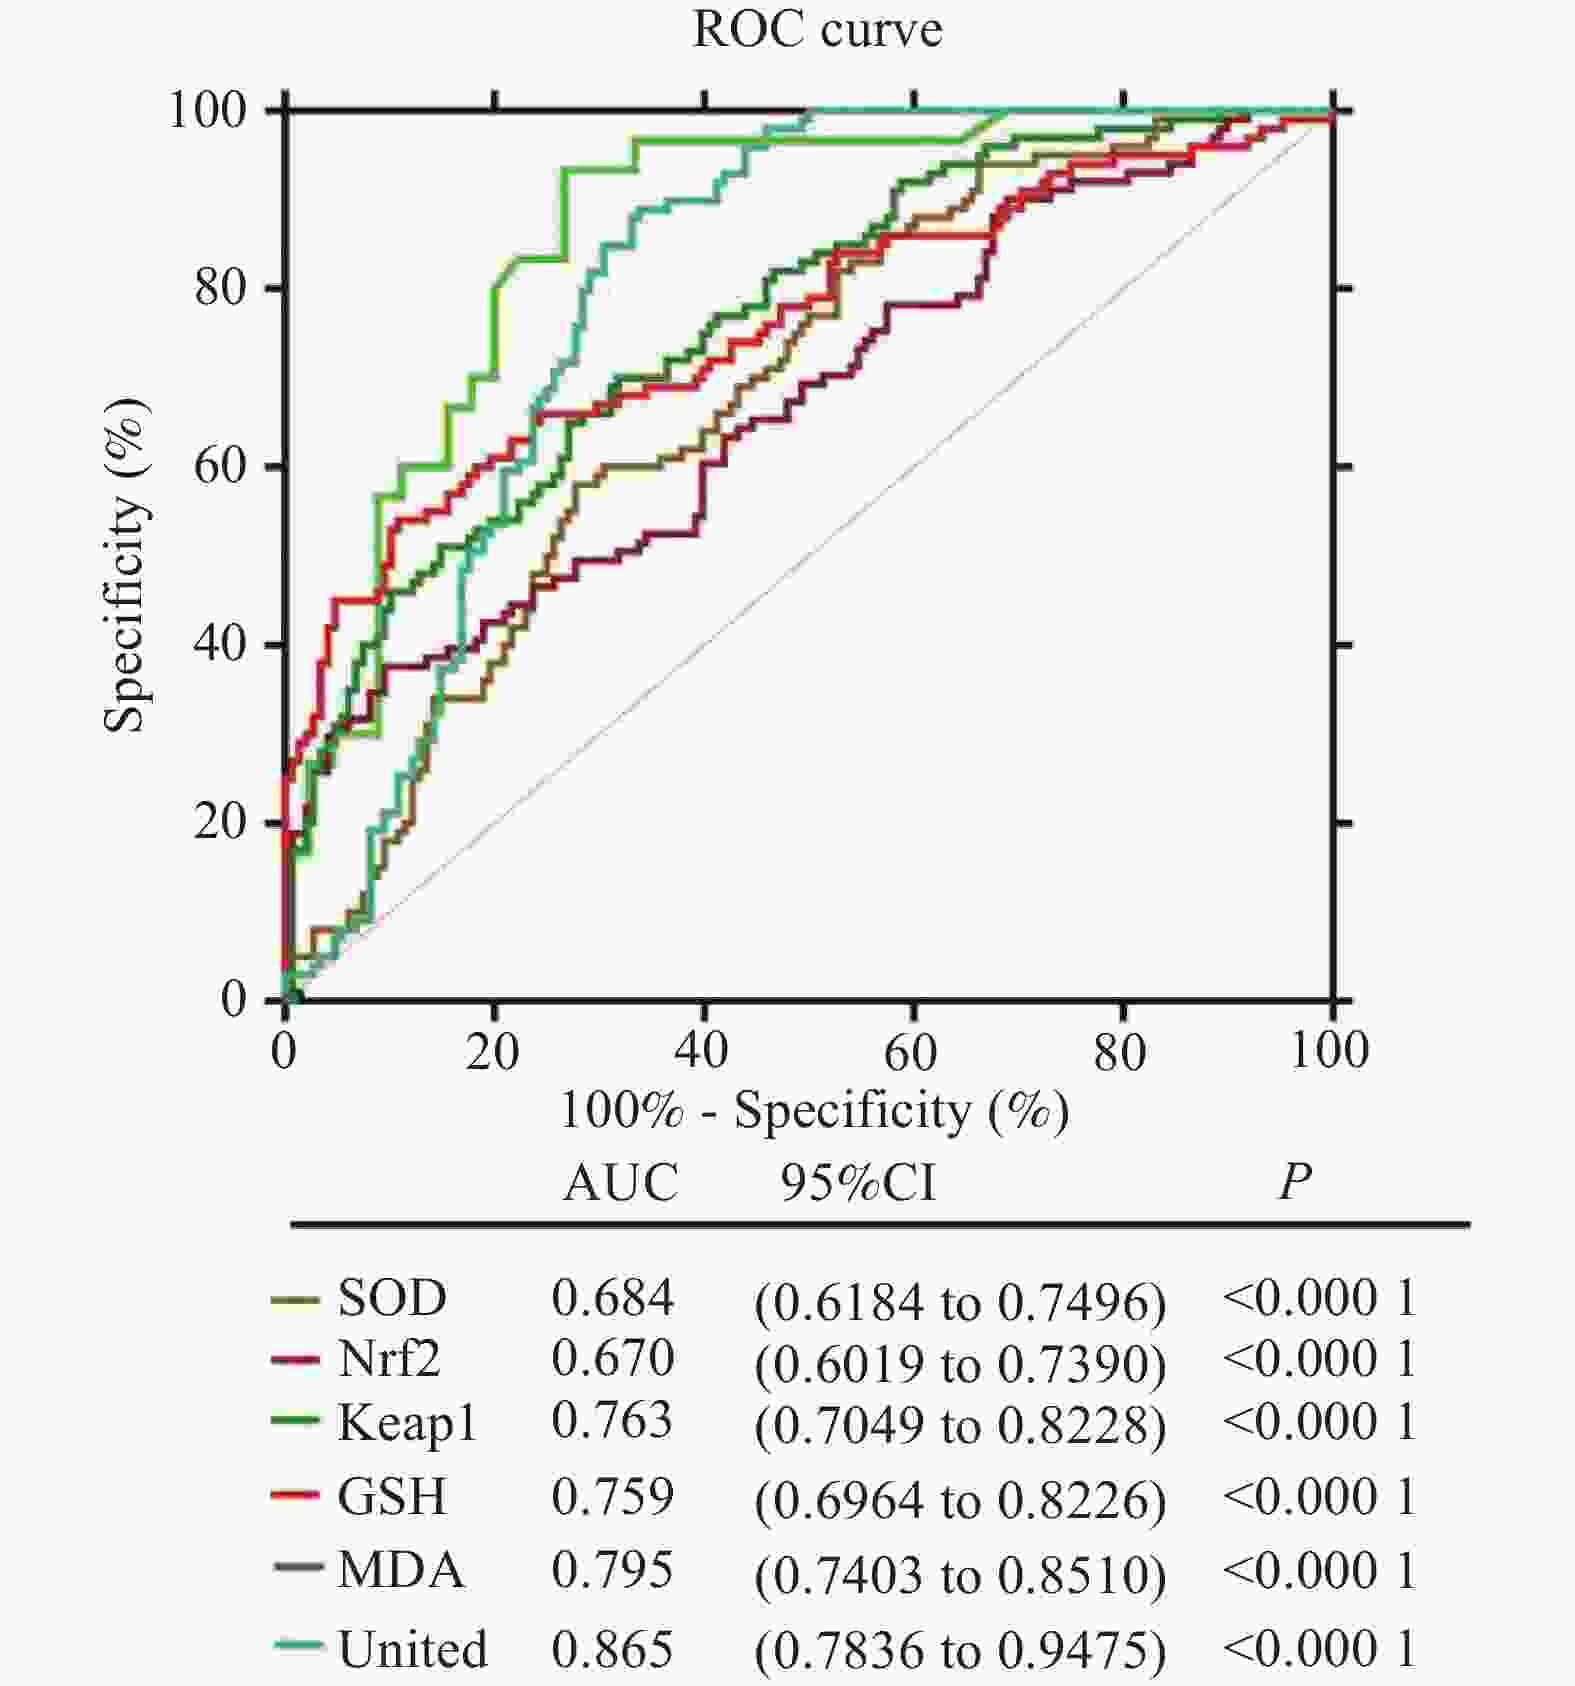
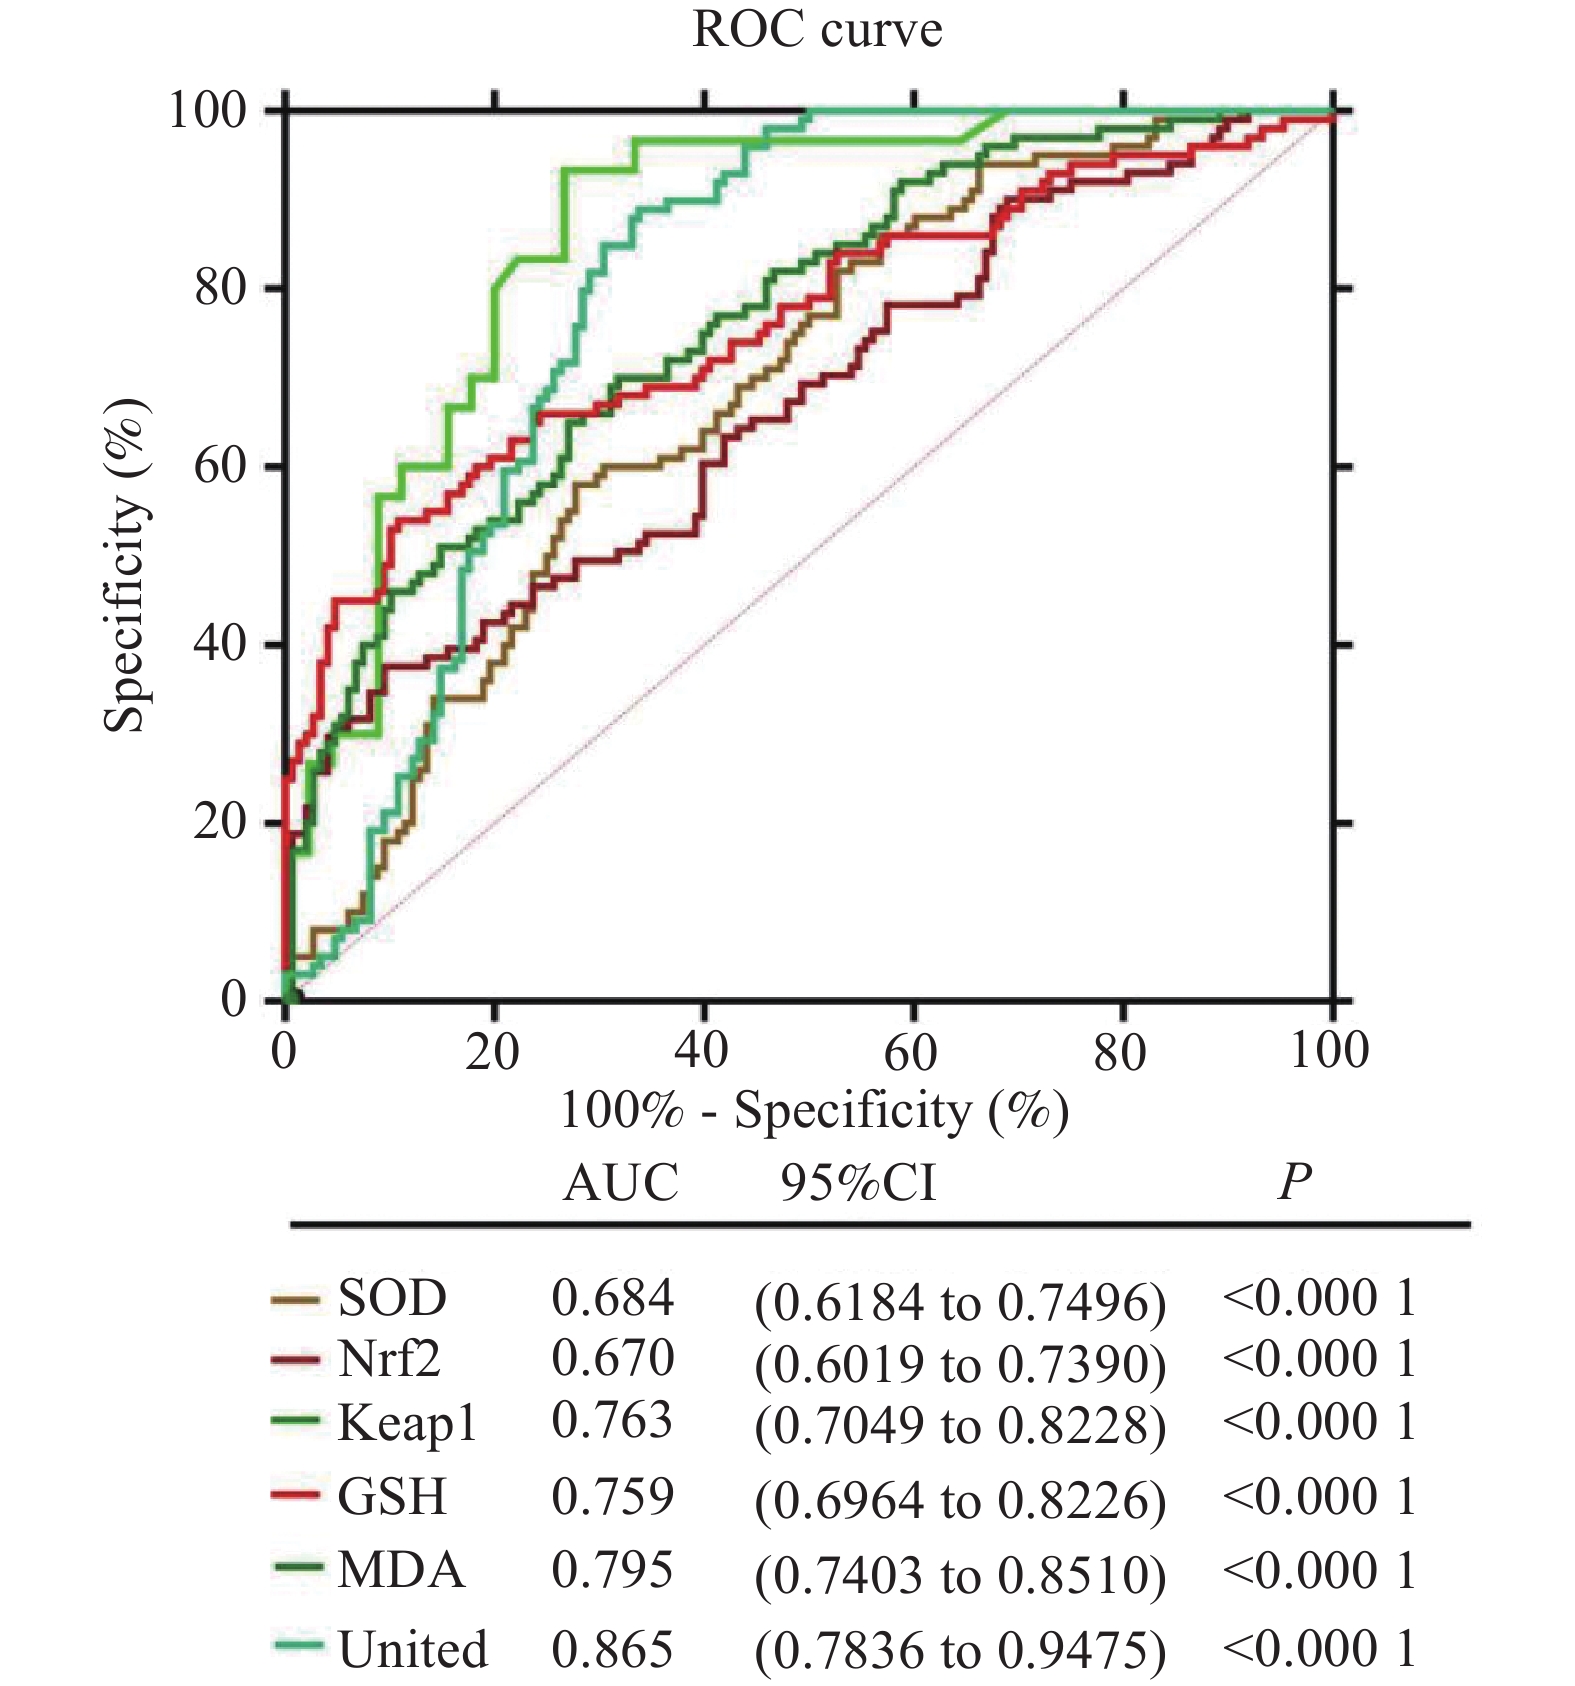
图 5 血清MDA、GSH、SOD、Keap1、Nrf2水平对牙周炎患者治疗后预后的预测价值
Figure 5. Predictive value of serum MDA,GSH,SOD,Keap1,and Nrf2 levels for post-treatment prognosis in patients with periodontitis
表 1 两组受试者一般资料比较[($\bar x \pm s $)/n (%)]
Table 1. Comparison of baseline characteristics between the two groups[($\bar x \pm s $)/n (%)]
项目 研究组 (n = 148) 对照组 (n = 100) t/χ2 P 年龄(岁) 30.25 ± 3.16 30.47 ± 3.25 0.432 0.665 性别 0.012 0.913 男性 78 (52.70) 52 (52.00) − − 女性 70 (47.30) 48 (48.00) − −  下载: 导出CSV
表 2 不同预后患者各指标水平比较[n(%)/($\bar x \pm s $)]
Table 2. Comparison of indicator levels among patients with different prognoses[n(%)/($\bar x \pm s $)]
指标 预后良好组(n = 93) 预后不良组(n = 55) t/χ2 P 年龄(岁) 30.84±4.52 31.35±4.27 3.333 0.079 <60 41(44.08) 29(52.73) ≥60 52(55.92) 26(47.27) 性别 1.589 0.854 女 28(30.11) 18(32.73) 男 65(69.89) 37(67.27) 吸烟史 26(27.96) 17(30.90) 0.183 0.713 患牙部位 2.837 0.095 上颌 52(55.91) 21(38.18) 下颌 41(44.09) 34(61.82) 咬合创伤 0.362 0.547 有 28(30.11) 20(36.36) 无 65(69.89) 25(63.64)
下载: 导出CSV
表 3 多变量Logistic回归分析及多重共线性诊断结果
Table 3. Results of multivariable logistic regression analysis and multicollinearity diagnostics
指标 β SE OR 95%CI P VIF MDA 5.0795 1.5928 160.6987 7.0833 ~3645.7789 0.0014 **1.3230 GSH − 0.0023 0.0036 0.9977 0.9907 ~1.0049 0.5346 1.2120 SOD − 0.0064 0.0136 0.9937 0.9675 ~1.0206 0.6412 1.3120 Keap1 2.2039 1.6964 9.0600 0.3260 ~251.8212 0.1939 1.3650 Nrf2 − 1.7417 0.6278 0.1752 0.0512 ~0.5997 0.0055 **1.2470 注:以治疗后12个月预后结局为因变量(预后良好=0,预后不良=1)。OR为优势比,CI为置信区间,VIF为方差膨胀因子;**P < 0.01。
下载: 导出CSV
表 4 血清MDA、GSH、SOD、Keap1、Nrf2及联合模型对牙周炎患者治疗后不良预后的预测效能
Table 4. Predictive efficacy of serum MDA,GSH,SOD,Keap1,Nrf2,and the combined model for adverse prognosis in patients with periodontitis after treatment
指标 截断值 灵敏度(%) 特异度(%) Youden J MDA 0.8490 61.8182 78.4946 0.4031 GSH 322.4600 47.2727 80.6452 0.2792 SOD 88.0800 54.5455 75.2688 0.2981 Keap1 0.7380 54.5455 73.1183 0.2766 Nrf2 2.1000 78.1818 59.1398 0.3732 Combined 0.3306 80.0000 70.9677 0.5097 注:最佳截断值根据最大约登指数确定。联合模型截断值为Logistic回归预测概率。
下载: 导出CSV
表 5 五项联合预测模型与各单项血清指标ROC曲线下面积的比较
Table 5. Comparison of the areas under the ROC curve between the five-item combined prediction model and each individual serum marker
AUC比较 ΔAUC Z 原始P Holm校正P Combined vs MDA 0.181 2.4986 0.0125 *0.0125 #Combined vs GSH 0.195 3.6456 0.0003 ***0.0013 ##Combined vs SOD 0.102 3.3437 0.0008 ***0.0033 ##Combined vs Keap1 0.106 3.2254 0.0013 **0.0038 ##Combined vs Nrf2 0.07 2.7737 0.0055 **0.0111 #注:采用配对DeLong检验比较AUC,使用Holm法校正多重比较P值。 *P < 0.05;**P < 0.01; ***P < 0.001;#P < 0.05;##P < 0.01。
下载: 导出CSV
-
[1] Agnese C C D, Schöffer C, Kantorski K Z, et al. Periodontitis and oral health-related quality of life: A systematic review and meta-analysis[J]. J Clin Periodontol, 2025, 52(3): 408-420. doi: 10.1111/jcpe.14074 [2] Chapple I L C, Hirschfeld J, Cockwell P, et al. Interplay between periodontitis and chronic kidney disease[J]. Nat Rev Nephrol, 2025, 21(4): 226-240. doi: 10.1038/s41581-024-00910-5 [3] Saleh O, Abdulmunim A, Aboushakra I, et al. Periodontitis: Grade modifiers revisited[J]. Oral Dis, 2025, 31(6): 1637-1646. doi: 10.1111/odi.15297 [4] Oršolić N, Jembrek M J. Targeting oxidative stress for disease[J]. Int J Mol Sci, 2025, 26(6): 2692. doi: 10.3390/ijms26062692 [5] Abou Sulaiman A E, Shehadeh R M H. Assessment of total antioxidant capacity and the use of vitamin C in the treatment of non-smokers with chronic periodontitis[J]. J Periodontol, 2010, 81(11): 1547-1554. doi: 10.1902/jop.2010.100173 [6] Canakçi C F, Ciçek Y, Canakçi V. Reactive oxygen species and human inflammatory periodontal diseases[J]. Biochemistry, 2005, 70(6): 619-628. [7] Tonetti M S, Greenwell H, Kornman K S. Staging and grading of periodontitis: Framework and proposal of a new classification and case definition[J]. J Clin Periodontol, 2018, 45 Suppl 20: S149-S161. [8] Bardaweel S K, Gul M, Alzweiri M, et al. Reactive oxygen species: The dual role in physiological and pathological conditions of the human body[J]. Eurasian J Med, 2018, 50(3): 193-201. doi: 10.5152/eurasianjmed.2018.17397 [9] Sczepanik F S C, Grossi M L, Casati M, et al. Periodontitis is an inflammatory disease of oxidative stress: We should treat it that way[J]. Periodontol 2000, 2020, 84(1): 45-68. [10] Mohideen K, Chandrasekaran K, Veeraraghavan H, et al. Meta-analysis of assessment of total oxidative stress and total antioxidant capacity in patients with periodontitis[J]. Dis Markers, 2023, 2023(1): 9949047. doi: 10.1155/2023/9949047 [11] Saha S, Sachivkina N, Lenchenko E, et al. Activation of the Nrf2 signaling pathway as a therapeutic strategy against periodontal disease: A narrative review[J]. Dent J, 2025, 13(7): 314. doi: 10.3390/dj13070314 [12] Zhang J, Hu H, Zhu Y, et al. Bushen Jianpi Tiaoxue Decoction (BJTD) ameliorates oxidative stress and apoptosis induced by uterus ageing through activation of the SIRT1/NRF2 pathway[J]. Phytomedicine, 2025, 136: 156288. doi: 10.1016/j.phymed.2024.156288 [13] Magdaleno F, Blajszczak C C, Charles-Niño C L, et al. Aminoguanidine reduces diabetes-associated cardiac fibrosis[J]. Exp Ther Med, 2019, 18(4): 3125-3138. [14] Nascimento G G, Tay J R H, Ng E, et al. Periodontitis and quality of life: A systematic review and meta-analyses[J]. J Periodontal Res, 2026. [15] Liu Y, Yang H, Wen Y, et al. Nrf2 inhibits periodontal ligament stem cell apoptosis under excessive oxidative stress[J]. Int J Mol Sci, 2017, 18(5): 1076. doi: 10.3390/ijms18051076 [16] Premkumar S, Appukuttan D, Kumar J R, et al. Comparative evaluation of ferroptosis markers NCOA4, ACSL4, and Nrf2 in periodontitis with and without type 2 diabetes mellitus: A case-control study[J]. Clin Oral Investig, 2025, 29(12): 591. doi: 10.1007/s00784-025-06647-0 [17] Papapanou P N, Sanz M, Buduneli N, et al. Periodontitis: Consensus report of workgroup 2 of the 2017 world workshop on the classification of periodontal and peri-implant diseases and conditions[J]. J Clin Periodontol, 2018, 45 Suppl 20: S162-S170. [18] Beck J D, Papapanou P N, Philips K H, et al. Periodontal medicine: 100 years of progress[J]. J Dent Res, 2019, 98(10): 1053-1062. doi: 10.1177/0022034519846113 [19] Kwon T, Lamster I B, Levin L. Current concepts in the management of periodontitis[J]. Int Dent J, 2021, 71(6): 462-476. doi: 10.1111/idj.12630 [20] Lushchak V I. Free radicals, reactive oxygen species, oxidative stress and its classification[J]. Chem Biol Interact, 2014, 224: 164-175. doi: 10.1016/j.cbi.2014.10.016 [21] Chen M, Cai W, Zhao S, et al. Oxidative stress-related biomarkers in saliva and gingival crevicular fluid associated with chronic periodontitis: A systematic review and meta-analysis[J]. J Clin Periodontol, 2019, 46(6): 608-622. doi: 10.1111/jcpe.13112 [22] Yamaguchi T, Yamamoto Y, Egashira K, et al. Oxidative stress inhibits endotoxin tolerance and may affect periodontitis[J]. J Dent Res, 2023, 102(3): 331-339. doi: 10.1177/00220345221138523 [23] 王浩宇, 王宇琪, 王冰倩, 等. 美沙拉嗪对RAW264.7细胞中促炎因子和过氧化物的抑制作用及其对牙周炎模型大鼠的治疗作用[J]. 吉林大学学报(医学版), 2024, 50(5): 1250-1258. doi: 10.13481/j.1671-587X.20240508 [24] Ying J, Zhang K, Huang Y, et al. Molecular hydrogen: Mechanism against oxidative stress and application in periodontitis: A review[J]. Medicine, 2025, 104(10): e41800. doi: 10.1097/MD.0000000000041800 [25] Ulasov A V, Rosenkranz A A, Georgiev G P, et al. Nrf2/Keap1/ARE signaling: Towards specific regulation[J]. Life Sci, 2022, 291: 120111. doi: 10.1016/j.lfs.2021.120111 [26] Ma F, Luo S, Lu C, et al. The role of Nrf2 in periodontal disease by regulating lipid peroxidation, inflammation and apoptosis[J]. Front Endocrinol, 2022, 13: 963451. doi: 10.3389/fendo.2022.963451 [27] Costa V B, de Godoi M A, Camilli A C, et al. Pharmacological modulation of Nrf2 signaling regulates oxidative stress, inflammation, and alveolar bone loss in experimental periodontitis[J]. J Periodontal Res, 2026. doi:10.1111/jre.70158. [28] Yin Y, Ma Z, Shi P. Nootkatone mitigates periodontal inflammation and reduces alveolar bone loss via Nrf2/HO-1 and NF-κB pathways in rat model of periodontitis[J]. Folia Histochem Cytobiol, 2024, 62(3): 145-153. doi: 10.5603/fhc.101862 [29] Wada S, Nakano H, Sawai Y, et al. Mechanistic and therapeutic insights into Nrf2-mediated redox regulation in periodontitis[J]. Antioxidants, 2026, 15(1): 72. doi: 10.3390/antiox15010072 [30] 王平. 巨噬细胞通过Mst1/2-Keap1-Nrf2信号维持胞内氧化还原稳态和抵抗细胞衰老[D]. 厦门: 厦门大学, 2019. [31] 孙小春, 谢琛, 谢芬, 等. 牙周感染对T2DM患者外周血炎症因子、氧化应激指标、MMP-2/TIMP-2比值的影响[J]. 中国实验诊断学, 2024, 28(7): 775-778. doi: 10.3969/j.issn.1007-4287.2024.07.005 -

 点击查看大图
计量
- 文章访问数: 5
- HTML全文浏览量: 4
- PDF下载量: 0
- 被引次数: 0
