




Expression Levels of Serum OPN,β-catenin,and BMP2 in Patients with Type 2 Diabetes Mellitus Complicated by Hypertension and Their Relationship with Carotid Atherosclerosis
-
摘要:
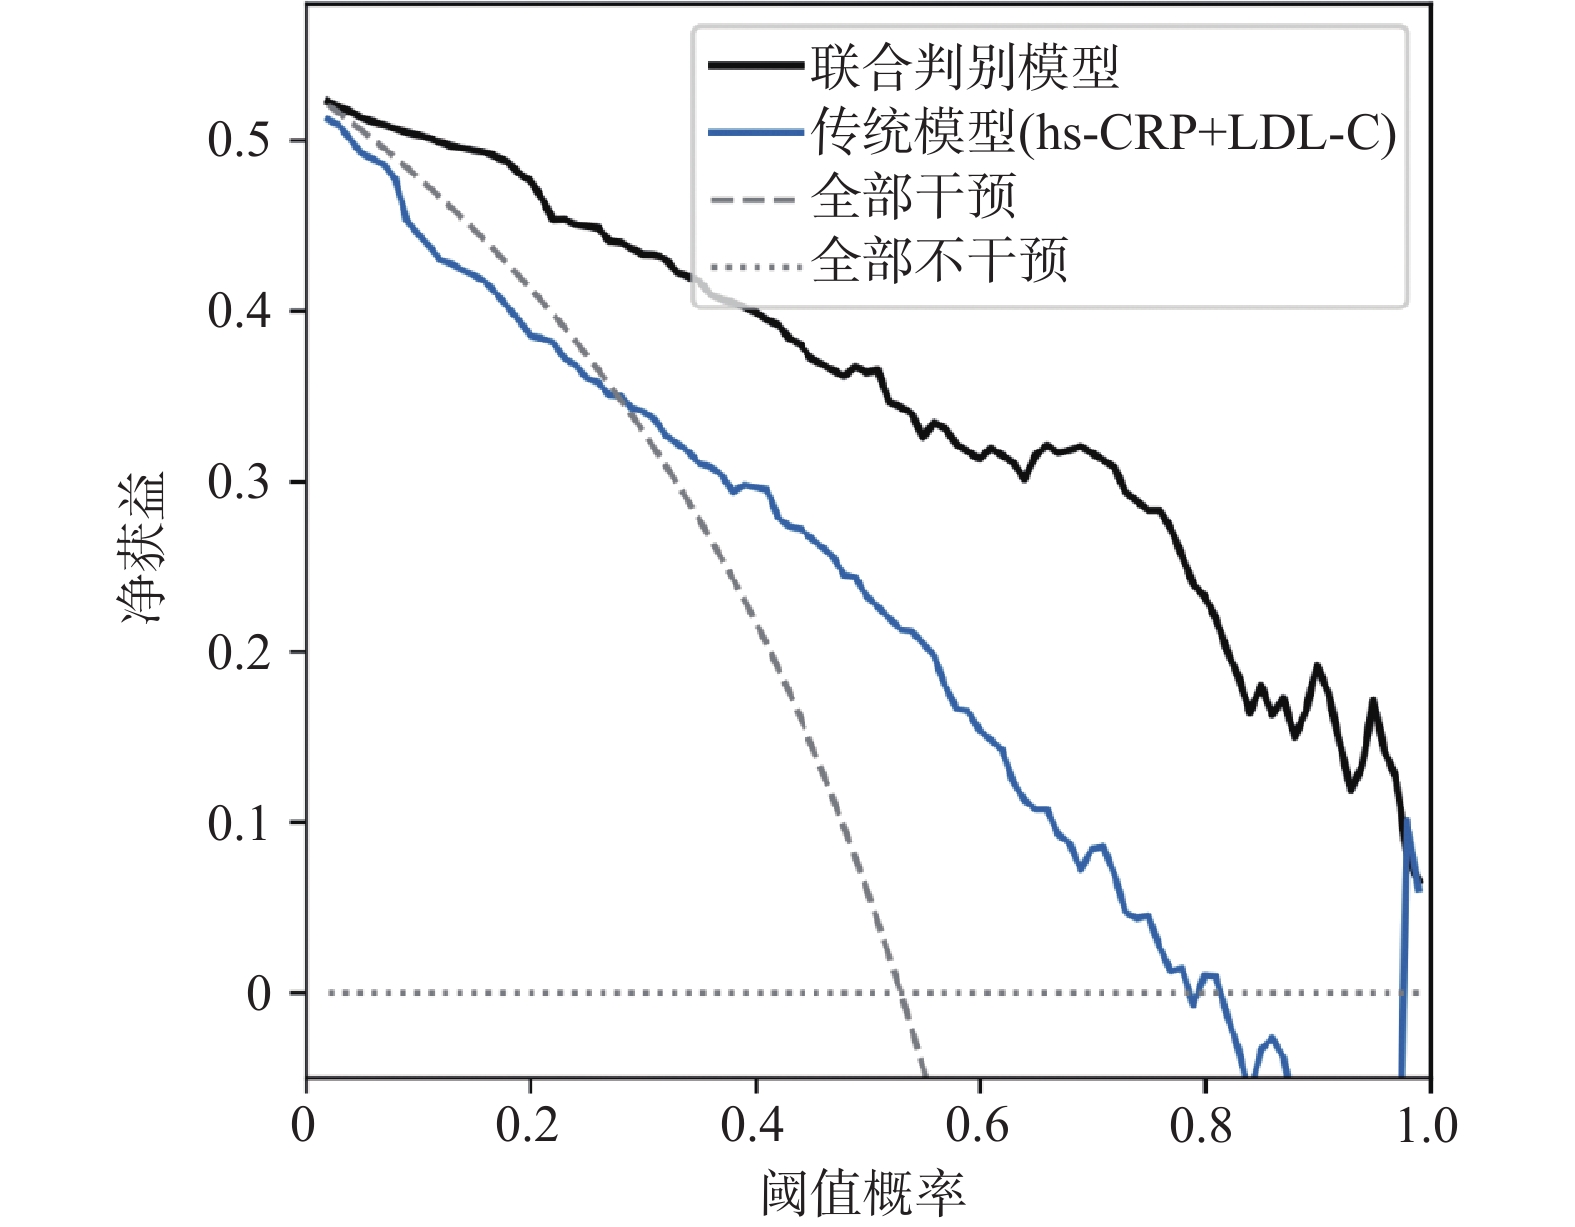
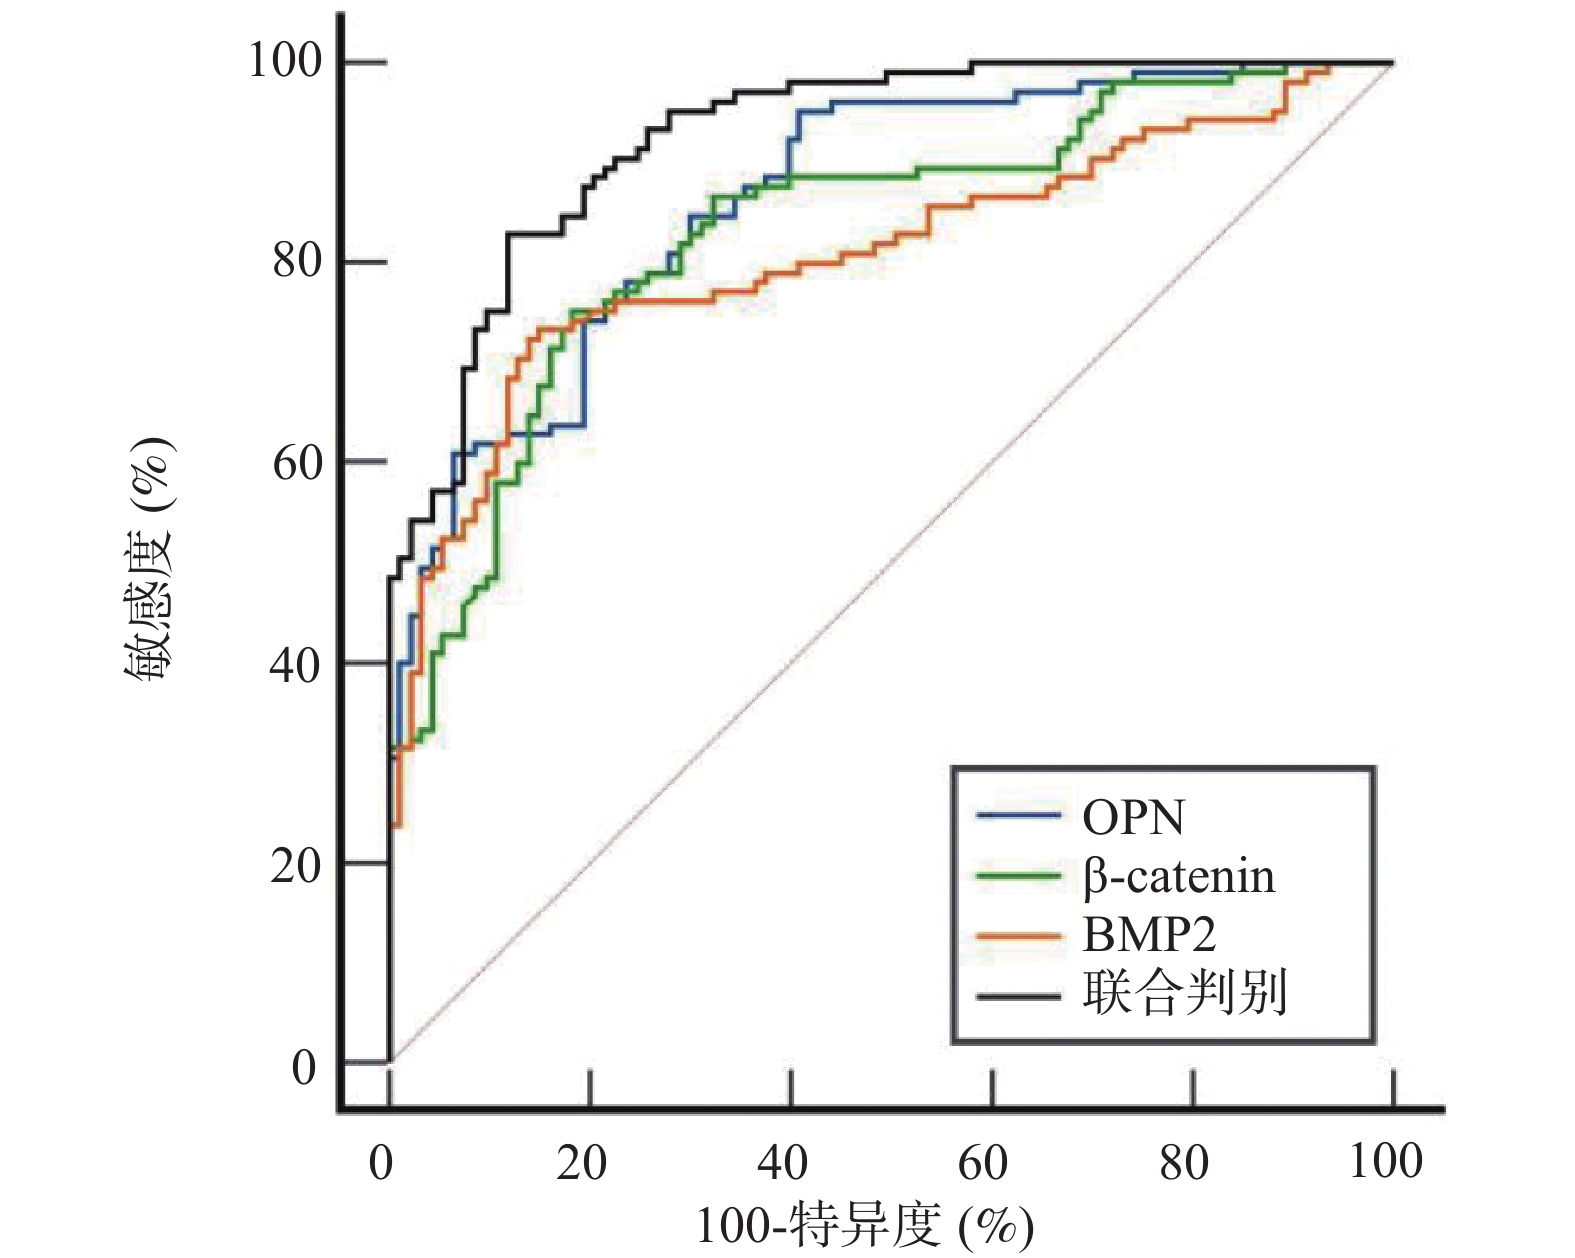
目的 检测血清骨桥蛋白(osteopontin,OPN)、β-连环蛋白(beta-catenin,β-catenin)、骨形态发生蛋白2(bone morphogenetic protein 2,BMP2)在2型糖尿病(type 2 diabetes mellitus,T2DM)合并高血压患者中的表达,并分析血清OPN、β-catenin、BMP2与T2DM合并高血压患者颈动脉粥样硬化(carotid atherosclerosis,CAS)的相关性。 方法 选取监利市人民医院2022年8月~2024年7月收治的198例T2DM合并高血压患者为研究组,根据是否合并CAS分为CAS组(n = 105)和非CAS组(n = 93)。另选取同期132例健康体检者为对照组。Spearman法、单因素及多因素Logistic回归分析OPN、β-catenin、BMP2与T2DM合并高血压患者CAS的关系;受试者工作特征(receiver operating characteristic,ROC)曲线分析血清OPN、β-catenin、BMP2对T2DM合并高血压患者CAS的判别价值。Bootstrap法绘制校准曲线进行内部验证。同时计算净重分类改善指数(net reclassification improvement,NRI)和综合判别改善指数(integrated discrimination improvement,IDI),评估三联标志物的增量价值。 结果 与对照组相比,研究组血清OPN、β-catenin、BMP2水平均显著较高(t = 21.764、15.409、18.228,均P < 0.001)。与非CAS组相比,CAS组血清OPN、β-catenin、BMP2水平均较高(t = 12.674、9.344、10.984,均P < 0.001)。Spearman分析结果显示,血清OPN、β-catenin、BMP2与T2DM合并高血压患者CAS呈显著正相关(rs = 0.659、0.573、0.635,均P < 0.001)。血清OPN、β-catenin、BMP2均为T2DM合并高血压患者CAS的相关因素[OR(95%CI)=1.805(1.239~2.630)、1.735(1.288~2.337)、1.982(1.350~2.910),均P < 0.05]。血清OPN、β-catenin、BMP2联合判别T2DM合并高血压患者CAS的曲线下面积(area under the curve,AUC)为0.926(95%CI 0.881~0.959),高于OPN、β-catenin、BMP2单独判别(Z = 2.695、3.339、3.808,均P < 0.05)。经Bootstrap 1000 次重抽样内部验证,校准曲线与理想曲线总体接近。在传统模型(hs-CRP+LDL-C)基础上加入血清OPN、β-catenin、BMP2后,NRI为0.538(95%CI 0.401~0.675),IDI为0.204(95%CI 0.152~0.256),均P < 0.001,具有增量判别价值。结论 T2DM合并高血压患者血清OPN、β-catenin、BMP2与CAS具有相关性,三者联合检测对CAS具有较高判别价值。 -
关键词:
- 2型糖尿病合并高血压 /
- 颈动脉粥样硬化 /
- 骨桥蛋白 /
- β-连环蛋白 /
- 骨形态发生蛋白2
Abstract:Objective To detect the expression of serum osteopontin (OPN), beta-catenin (β-catenin), and bone morphogenetic protein 2 (BMP2) in patients with type 2 diabetes mellitus (T2DM) complicated by hypertension, and to analyze the correlations of serum OPN, β-catenin, and BMP2 with carotid atherosclerosis (CAS) in these patients. Methods A total of 198 patients with T2DM complicated by hypertension admitted to Jianli Municipal People's Hospital from August 2022 to July 2024 were selected as the study group, and were divided into CAS group (n = 105) and non-CAS group (n = 93) according to the presence of CAS. In addition, 132 healthy individuals undergoing physical examination during the same period were selected as the control group. Spearman correlation analysis, univariate and multivariate Logistic regression were performed to examine the relationships of OPN, β-catenin, BMP2 and CAS in T2DM patients with hypertension. Receiver operating characteristic (ROC) curves were used to evaluate the discriminatory value of serum OPN, β-catenin, and BMP2 for CAS in these patients. Calibration curves were plotted using the Bootstrap method for internal validation. Meanwhile, the net reclassification improvement (NRI) and integrated discrimination improvement (IDI) were calculated to assess the incremental value of the triple-marker panel. Results Serum levels of OPN, β-catenin, and BMP2 in the study group were significantly higher than those in the control group (t = 21.764, 15.409, and 18.228, all P < 0.001). Compared with the non-CAS group, serum OPN, β-catenin, and BMP2 levels in the CAS group were higher (t = 12.674, 9.344, and 10.984, all P < 0.001). Spearman analysis showed that serum OPN, β-catenin, and BMP2 were significantly positively correlated with CAS in patients with T2DM complicated by hypertension (rs = 0.659, 0.573, and 0.635, all P < 0.001). Serum OPN, β-catenin, and BMP2 were all associated factors for CAS in these patients [OR (95%CI)=1.805 (1.239~2.630), 1.735 (1.288~2.337), and 1.982 (1.350~2.910), all P < 0.05]. The area under the curve (AUC) of the combined detection of serum OPN, β-catenin, and BMP2 for discriminating CAS in patients with T2DM complicated by hypertension was 0.926 (95%CI 0.881~0.959), which was higher than that of OPN, β-catenin, or BMP2 alone (Z = 2.695, 3.339, and 3.808, all P < 0.05). Internal validation with 1000 Bootstrap resamples showed that the calibration curve was overall close to the ideal curve. After adding serum OPN, β-catenin, and BMP2 to the traditional model (hs-CRP+LDL-C), the NRI was 0.538 (95%CI 0.401~0.675) and the IDI was 0.204 (95%CI 0.152~0.256), both P < 0.001, indicating incremental discriminatory value.Conclusion Serum OPN, β-catenin, and BMP2 are correlated with CAS in patients with T2DM complicated by hypertension, and their combined detection has high discriminatory value for CAS. -
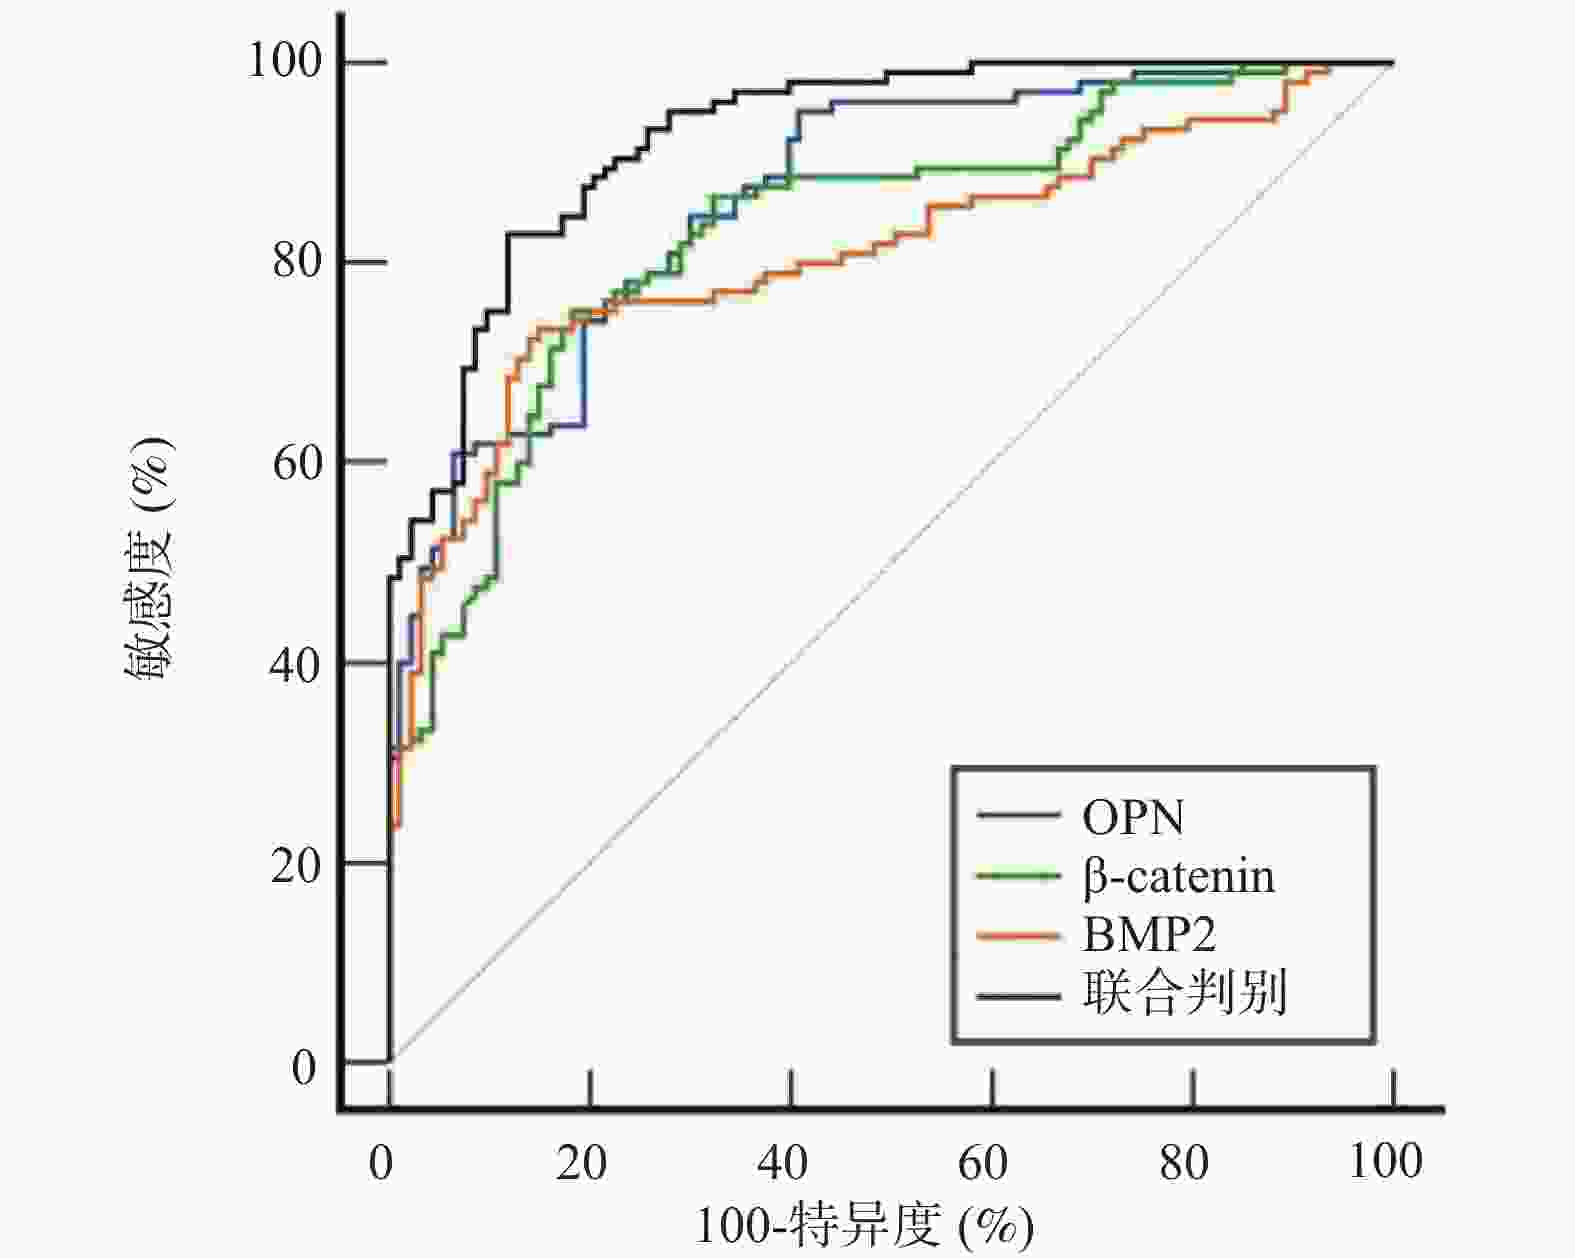
图 1 血清OPN、β-catenin、BMP2判别T2DM合并高血压患者CAS的ROC曲线
注:OPN、β-catenin、BMP2单独判别及三者联合判别的AUC(95%CI)分别为0.866(0.810~0.910)、0.834(0.774~0.883)、0.809(0.747~0.861)、0.926(0.881~0.959)。
Figure 1. ROC curves of serum OPN,β-catenin,and BMP2 for discriminating CAS in T2DM patients complicated with hypertension
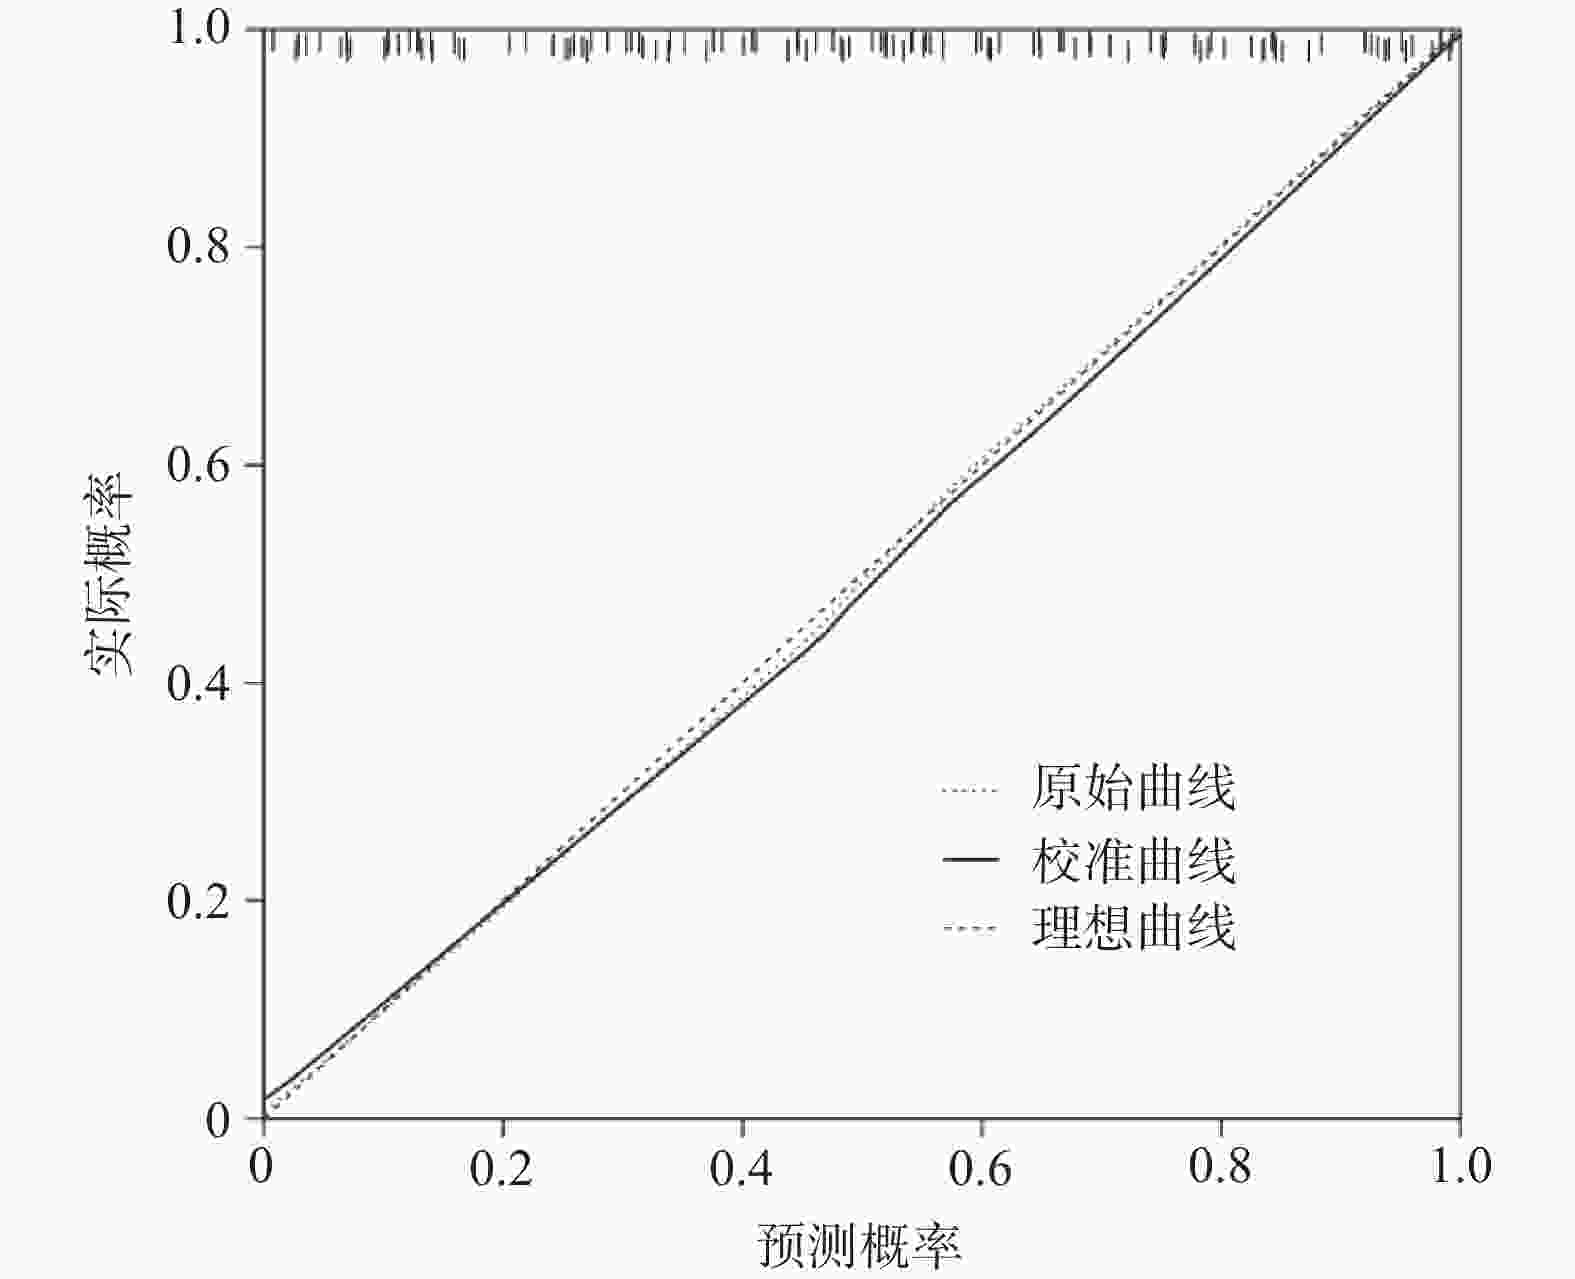
图 2 校准曲线
注:校准曲线基于Bootstrap有放回重复抽样1000次绘制,按预测概率十分位数分为10组;联合判别模型的AUC为0.926(95%CI 0.881~0.959),敏感度82.86%,特异度88.17%,约登指数0.710。
Figure 2. Calibration curve
表 1 对照组、研究组一般资料比较[($ \bar x \pm s $)/n(%)]
Table 1. Comparison of general data between the control group and study group [($ \bar x \pm s $)/n(%)]
指标 合计 对照组(n = 132) 研究组(n = 198) t/χ2 P 年龄(岁) - 64.95 ± 6.32 65.70 ± 6.43 1.045 0.297 性别 0.809 0.368 男 170 64(48.48) 106(53.54) 女 160 68(51.52) 92(46.46) 体质量指数(kg/m2) - 23.17 ± 2.09 23.56 ± 1.88 1.765 0.079 吸烟史 127 47(35.61) 80(40.40) 0.770 0.380 饮酒史 133 46(34.85) 87(43.94) 2.721 0.099 高脂血症 93 31(23.48) 62(31.31) 2.398 0.121  下载: 导出CSV
表 2 对照组、研究组血清OPN、β-catenin、BMP2水平比较($ \bar x \pm s $)
Table 2. Comparison of serum OPN,β-catenin,and BMP2 levels between the control group and study group($ \bar x \pm s $)
组别 n OPN(ng/mL) β-catenin(pg/mL) BMP2(pg/mL) 对照组 132 170.24 ± 26.39 65.43 ± 9.97 43.17 ± 6.54 研究组 198 251.56 ± 37.12 84.98 ± 12.09 58.79 ± 8.27 t - 21.764 15.409 18.228 P - <0.001* <0.001* <0.001* *P < 0.05。
下载: 导出CSV
表 3 CAS组、非CAS组临床资料比较[($ \bar x \pm s $)/n(%)]
Table 3. Comparison of clinical data between the CAS group and non-CAS group[($ \bar x \pm s $)/n(%)]
指标 合计 CAS组(n = 105) 非CAS组(n = 93) t/χ2 P 年龄(岁) - 66.53 ± 6.46 64.77 ± 6.39 1.923 0.056 性别 0.634 0.426 男 106 59(56.19) 47(50.54) 女 92 46(43.81) 46(49.46) 体质量指数(kg/m2) - 23.61 ± 1.85 23.50 ± 1.91 0.411 0.681 FBG(mmol/L) - 9.17 ± 1.08 8.43 ± 0.97 5.111 <0.001* HbA1c(%) - 8.73 ± 0.92 8.06 ± 0.85 5.300 <0.001* BUN(mmol/L) - 6.12 ± 1.54 5.89 ± 1.48 1.083 0.280 Scr(μmol/L) - 72.45 ± 15.62 69.83 ± 14.97 1.198 0.232 hs-CRP(mg/L) - 16.88 ± 5.31 11.56 ± 5.52 6.906 <0.001* LDL-C(mmol/L) - 3.64 ± 1.11 2.31 ± 0.45 10.766 <0.001* T2DM病程(年) - 8.62 ± 2.16 7.25 ± 1.93 4.681 <0.001* 高血压病程(年) - 7.96 ± 2.04 7.48 ± 1.81 1.742 0.083 高血压分级 4.141 0.126 1级 51 24(22.86) 27(29.03) 2级 105 53(50.48) 52(55.91) 3级 42 28(26.67) 14(15.05) 吸烟史 80 45(42.86) 35(37.63) 0.559 0.455 饮酒史 87 49(46.67) 38(40.86) 0.675 0.411 高脂血症 62 42(40.00) 20(21.51) 7.843 0.005* *P < 0.05。
下载: 导出CSV
表 4 CAS组、非CAS组血清OPN、β-catenin、BMP2水平比较($ \bar x \pm s $)
Table 4. Comparison of serum OPN,β-catenin,and BMP2 levels between the CAS group and non-CAS group($ \bar x \pm s $)
组别 n OPN(ng/mL) β-catenin(pg/mL) BMP2(pg/mL) CAS组 105 283.28 ± 41.59 92.56 ± 12.93 64.91 ± 9.15 非CAS组 93 215.74 ± 32.07 76.43 ± 11.14 51.89 ± 7.28 t - 12.674 9.344 10.984 P - <0.001* <0.001* <0.001* 注:三个指标的Cohen‘s d值分别为1.80、1.33、1.57;*P < 0.05。
下载: 导出CSV
表 5 变量赋值表
Table 5. Variable assignment table
变量 赋值说明 年龄 连续变量,单位:岁 性别 男=1,女=2 体质量指数 连续变量,单位:kg/m2 FBG 连续变量,单位:mmol/L HbA1c 连续变量,单位:% BUN 连续变量,单位:mmol/L Scr 连续变量,单位:μmol/L hs-CRP 连续变量,单位:mg/L LDL-C 连续变量,单位:mmol/L T2DM病程 连续变量,单位:年 高血压病程 连续变量,单位:年 高血压分级 1级=1,2级=2,3级=3 吸烟史 无=0,有=1 饮酒史 无=0,有=1 高脂血症 无=0,有=1 OPN 连续变量,单位:ng/mL β-catenin 连续变量,单位:pg/mL BMP2 连续变量,单位:pg/mL CAS(因变量) 未合并=0,合并=1
下载: 导出CSV
表 6 T2DM合并高血压患者CAS的单因素Logistic回归分析
Table 6. Univariate logistic regression analysis of CAS in T2DM patients with hypertension
变量 β SE Waldχ2 P OR 95%CI下限 95%CI上限 年龄(岁) 0.059 0.128 0.214 0.644 1.061 0.826 1.364 性别 0.227 0.286 0.631 0.427 1.255 0.716 2.198 体质量指数(kg/m2) 0.020 0.049 0.163 0.686 1.020 0.927 1.123 FBG(mmol/L) 0.683 0.141 23.471 <0.001* 1.980 1.502 2.610 HbA1c(%) 0.765 0.151 25.667 <0.001* 2.149 1.598 2.889 BUN(mmol/L) 0.077 0.071 1.175 0.278 1.080 0.940 1.241 Scr(μmol/L) 0.015 0.013 1.312 0.252 1.015 0.989 1.041 hs-CRP(mg/L) 0.114 0.018 40.267 <0.001* 1.121 1.082 1.161 LDL-C(mmol/L) 1.229 0.191 41.388 <0.001* 3.417 2.350 4.969 T2DM病程(年) 0.300 0.066 20.676 <0.001* 1.350 1.186 1.536 高血压病程(年) 0.105 0.151 0.486 0.486 1.111 0.826 1.494 高血压分级 0.055 0.296 0.035 0.851 1.057 0.592 1.888 吸烟史 0.215 0.288 0.558 0.455 1.240 0.705 2.181 饮酒史 0.235 0.290 0.657 0.418 1.265 0.717 2.233 高脂血症 0.888 0.319 7.754 0.005* 2.431 1.301 4.543 OPN(ng/mL) 0.674 0.306 4.858 0.028* 1.963 1.078 3.576 β-catenin(pg/mL) 0.711 0.252 7.960 0.005* 2.036 1.242 3.336 BMP2(pg/mL) 0.750 0.302 6.175 0.013* 2.118 1.172 3.828 *P < 0.05。
下载: 导出CSV
表 7 T2DM合并高血压患者CAS的多因素Logistic回归分析
Table 7. Multivariate Logistic regression analysis of CAS in T2DM patients with hypertension
变量 VIF β SE Wald χ2 P OR 95%CI下限 95%CI上限 hs-CRP(mg/L) 1.405 0.484 0.215 5.074 0.024* 1.623 1.065 2.474 T2DM病程(年) 1.422 0.445 0.163 7.464 0.006* 1.561 1.134 2.149 年龄(岁) 1.532 0.054 0.062 0.746 0.388 1.055 0.934 1.191 高血压病程(年) 1.700 0.277 0.215 1.658 0.198 1.319 0.865 2.010 高血压分级 1.263 0.047 0.174 0.073 0.788 1.048 0.745 1.474 OPN(ng/mL) 2.152 0.591 0.192 9.461 0.002* 1.805 1.239 2.630 β-catenin(pg/mL) 1.996 0.551 0.152 13.141 <0.001* 1.735 1.288 2.337 BMP2(pg/mL) 2.008 0.684 0.196 12.182 <0.001* 1.982 1.350 2.910 注:以高血压1级为参照设置哑变量(2级、3级)重设多因素模型行敏感性分析:hs-CRP、T2DM病程、血清OPN、β-catenin、BMP2的OR值与主模型偏差均<1%,且P < 0.05;高血压2级、3级均P > 0.05,与主模型结论一致,提示结果稳健;*P < 0.05。
下载: 导出CSV
表 8 血清OPN、β-catenin、BMP2对T2DM合并高血压患者CAS的判别价值
Table 8. Discriminative value of serum OPN,β-catenin,and BMP2 for CAS in patients with T2DM complicated with hypertension
变量 AUC 截断值 95%CI 敏感度(%) 特异度(%) 约登指数 OPN 0.866 254.20 ng/mL 0.810~0.910 74.29 80.65 0.549 β-catenin 0.834 83.85 pg/mL 0.774~0.883 75.24 81.72 0.570 BMP2 0.809 58.85 pg/mL 0.747~0.861 72.38 86.02 0.584 联合判别 0.926 - 0.881~0.959 82.86 88.17 0.710
下载: 导出CSV
表 9 血清OPN、β-catenin、BMP2的增量价值分析
Table 9. Incremental value analysis of serum OPN,β-catenin,and BMP2
变量 AUC 95%CI NRI P IDI P hs-CRP 0.778 0.714~0.842 - - - - LDL-C 0.744 0.676~0.812 - - - - 传统模型(hs-CRP+LDL-C) VS
传统模型+OPN、β-catenin、BMP2- - 0.538(0.401~0.675) <0.001* 0.204(0.152~0.256) <0.001* *P < 0.05。
下载: 导出CSV
-
[1] Yan Y, Wu T, Zhang M, et al. Prevalence, awareness and control of type 2 diabetes mellitus and risk factors in Chinese elderly population[J]. BMC Public Health, 2022, 22(1): 1382. doi: 10.1186/s12889-022-13759-9 [2] Mu L, Yu P, Xu H, et al. Effect of sodium reduction based on the DASH diet on blood pressure in hypertensive patients with type 2 diabetes[J]. Nutr Hosp, 2022, 39(3): 537-546. doi: 10.20960/nh.04039 [3] Fan H, Han J, Chen L, et al. Association between plasma growth arrest-specific protein 6 and carotid atherosclerosis in type 2 diabetes mellitus[J]. Nutr Metab Cardiovasc Dis, 2022, 32(8): 1917-1923. doi: 10.1016/j.numecd.2022.05.007 [4] Behairy M A, Shawky S, Hamed R, et al. Is serum Osteopontin a predictor of carotid atherosclerosis severity among prevalent hemodialysis patients?[J]. Clínica E Investig En Arterioscler, 2022, 34(2): 75-85. doi: 10.1016/j.arteri.2021.11.004 [5] Yang L, Dai R, Wu H, et al. Unspliced XBP1 counteracts β-catenin to inhibit vascular calcification[J]. Circ Res, 2022, 130(2): 213-229. doi: 10.1161/CIRCRESAHA.121.319745 [6] Lu Y, Meng L, Ren R, et al. Paraspeckle protein NONO attenuates vascular calcification by inhibiting bone morphogenetic protein 2 transcription[J]. Kidney Int, 2024, 105(6): 1221-1238. doi: 10.1016/j.kint.2024.01.039 [7] 中华医学会糖尿病学分会. 中国2型糖尿病防治指南(2020年版)[J]. 中华糖尿病杂志, 2021, 13(4): 315-409. doi: 10.3760/cma.j.cn115791-20210221-00095 [8] 《中国高血压防治指南》修订委员会. 中国高血压防治指南2018年修订版[J]. 心脑血管病防治, 2019, 19(1): 1-44. doi: 10.3969/j.issn.1009-816x.2019.01.001 [9] 王小庆, 应喜红, 黄丽. 血清Hcy、Lp(a)及25(OH)D3水平与2型糖尿病合并高血压患者发生颈动脉粥样硬化的关系[J]. 标记免疫分析与临床, 2024, 31(5): 891-896. doi: 10.11748/bjmy.issn.1006-1703.2024.05.022 [10] 中华医学会神经病学分会, 中华医学会神经病学分会脑血管病学组, 周华东, 等. 中国头颈部动脉粥样硬化诊治共识[J]. 中华神经科杂志, 2017, 50(8): 572-578. doi: 10.3760/cma.j.issn.1006-7876.2017.08.003 [11] 中国医师协会超声医师分会. 血管超声检查指南[J]. 中华超声影像学杂志, 2009, 18(10): 911-920. doi: 10.3760/cma.j.issn.1004-4477.2009.10.037 [12] Benson J C, Saba L, Bathla G, et al. MR imaging of carotid artery atherosclerosis: Updated evidence on high-risk plaque features and emerging trends[J]. AJNR Am J Neuroradiol, 2023, 44(8): 880-888. doi: 10.3174/ajnr.A7921 [13] Huang X, Zhang Y, Zhang W, et al. Osteopontin-targeted and PPARδ-agonist-loaded nanoparticles efficiently reduce atherosclerosis in apolipoprotein E (-/-) mice[J]. ACS Omega, 2022, 7(33): 28767-28778. doi: 10.1021/acsomega.2c00575 [14] Lin E Y, Xi W, Aggarwal N, et al. Osteopontin (OPN)/SPP1: From its biochemistry to biological functions in the innate immune system and the central nervous system (CNS)[J]. Int Immunol, 2023, 35(4): 171-180. doi: 10.1093/intimm/dxac060 [15] 陈宇, 王德琴, 缪娴静, 等. 维持性血液透析患者血清骨桥蛋白、成纤维细胞生长因子23与血管钙化的关系[J]. 检验医学, 2024, 39(7): 656-660. doi: 10.3969/j.issn.1673-8640.2024.07.007 [16] 吴丹, 辛慧, 关硕, 等. 促甲状腺激素和OPN检测在甲减合并动脉粥样硬化患者中的临床意义[J]. 热带医学杂志, 2021, 21(9): 1158-1162. doi: 10.3969/j.issn.1672-3619.2021.09.016 [17] Nie H, Liu G, Lu W H, et al. Intracellular osteopontin of macrophages promotes carotid plaques formation by inducing foam cells and releasing proinflammatory cytokines[J]. J Am Heart Assoc, 2026, 15(6): e041336. doi: 10.1161/JAHA.125.041336 [18] Maddaloni E, Nguyen M, Shah S H, et al. Osteoprotegerin, osteopontin, and osteocalcin are associated with cardiovascular events in type 2 diabetes: Insights from EXSCEL[J]. Diabetes Care, 2025, 48(2): 235-242. doi: 10.2337/dc24-1455 [19] Lin W, Hou L, Tang J, et al. miR-195-5p targets Smad7 regulation of the Wnt/β-catenin pathway to promote osteogenic differentiation of vascular smooth muscle cells[J]. BMC Cardiovasc Disord, 2024, 24(1): 221. doi: 10.1186/s12872-024-03891-2 [20] Liu D, Cui X, Lu R, et al. CTRP3 is a coronary artery calcification biomarker and protects against vascular calcification by inhibiting β-catenin nuclear translocation to prevent vascular smooth muscle cell osteogenic differentiation[J]. J Cardiol, 2022, 79(4): 551-558. doi: 10.1016/j.jjcc.2021.10.018 [21] 石磊, 陈娟, 许慧敏. 血清β-连环蛋白、E-钙黏蛋白水平与老年冠心病患者冠状动脉狭窄的关系[J]. 中国分子心脏病学杂志, 2024, 24(2): 6010-6014. doi: 10.16563/j.cnki.1671-6272.2024.04.010 [22] Chen Z, Lin B, Yao X, et al. Endothelial β-catenin upregulation and Y142 phosphorylation drive diabetic angiogenesis via upregulating KDR/HDAC9[J]. Cell Commun Signal, 2024, 22(1): 182. doi: 10.1186/s12964-024-01566-1 [23] Azhdari M, zur Hausen A. Wnt/β-catenin and Notch signaling pathways in cardiovascular disease: Mechanisms and therapeutics approaches[J]. Pharmacol Res, 2025, 211: 107565. doi: 10.1016/j.phrs.2024.107565 [24] Wadey K S, Somos A, Leyden G, et al. Pro-inflammatory role of Wnt/β-catenin signaling in endothelial dysfunction[J]. Front Cardiovasc Med, 2023, 9: 1059124. doi: 10.3389/fcvm.2022.1059124 [25] 高剑, 梁铮, 赵飞, 等. 血清β-catenin、E-cadherin水平与糖尿病肾病患者钙磷代谢、颈动脉钙化的关系[J]. 国际检验医学杂志, 2024, 45(12): 1469-1473. doi: 10.3969/j.issn.1673-4130.2024.12.012 [26] Shi X, Zhang S, Li J, et al. Fibronectin/α5 integrin contribute to hypertension-associated arterial ageing and calcification through affecting BMP2/MGP imbalance and enhancing vascular smooth muscle cell phenotypic transformation[J]. Gerontology, 2024, 70(8): 858-875. doi: 10.1159/000539399 [27] Zhu X X, Meng X Y, Chen G, et al. Nesfatin-1 enhances vascular smooth muscle calcification through facilitating BMP-2 osteogenic signaling[J]. Cell Commun Signal, 2024, 22(1): 488. doi: 10.1186/s12964-024-01873-7 [28] 徐建男, 王淑明, 张建新, 等. 维持性血液透析患者血清GRP78、BMP2水平及其与血管钙化的相关性[J]. 中国血液净化, 2023, 22(4): 254-258. doi: 10.3969/j.issn.1671-4091.2023.04.002 [29] 王洪刚. BMP2调节SMAD与microRNA介导慢性肾衰竭血管钙化的机制研究[D]. 济南: 山东大学, 2022. [30] Ortega M A, De Leon-Oliva D, Gimeno-Longas M J, et al. Vascular calcification: Molecular networking, pathological implications and translational opportunities[J]. Biomolecules, 2024, 14(3): 275. doi: 10.3390/biom14030275 -

 点击查看大图
计量
- 文章访问数: 3
- HTML全文浏览量: 2
- PDF下载量: 0
- 被引次数: 0
